An anion gap calculator is a useful diagnostic tool used to help clinicians and patients calculate anion gap values and support kidney assessment when an acid-base disorder is suspected. It is especially useful when reviewing lab values from an electrolyte panel or a basic metabolic panel, because the result can indicate metabolic acidosis, a common metabolic derangement seen with impaired kidney function.
In kidney disease, especially chronic kidney disease and acute kidney injury, the body may struggle to remove acids effectively. That can alter serum electrolytes and shift the balance between sodium, chloride, and bicarbonate. A properly read anion gap result can help clarify the likely cause of acidosis and inform further laboratory testing.
How the Anion Gap Assesses
The anion gap indicates the gap between tested positively charged and negatively charged electrolytes in the circulation. It is usually computed using sodium, chloride, and bicarbonate, and in some cases includes potassium depending on the calculation formula used.
Even though the body contains many ions, standard blood tests do not measure every charged particle directly. The anion gap is used to estimate the amount of unmeasured anions, which is important for assessing acid-base balance. In practice, this gives clinicians a simple way to identify hidden acids that may be accumulating in the bloodstream.
For kidney disease evaluation, this matters because the kidneys serve a central role in acid excretion and bicarbonate regulation. When renal clearance declines, the pattern of serum electrolytes can show important clues about underlying renal impairment.
The key components are:
- Sodium, the main measured cation Chloride, the main measured anion Bicarbonate, which helps buffer acid in the blood Potassium, which may or may not be included in the formula
Because this is a calculation based on routine lab values, the anion gap is often one of the first tools used to evaluate an unexplained acid-base disorder.
How the Anion Gap Calculator Functions
An anion gap calculator follows a simple formula based on values from a blood chemistry test. Most commonly, the calculation is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions of the formula also include potassium, but numerous clinical settings omit it because the contribution is relatively small. For this reason different calculators may produce slightly different results. The most important step is to use the same method consistently convert AG mEq to mmol when you interpret anion gap trends over time.
The calculator is especially helpful when values come from a recent basic metabolic panel or broader serum electrolytes test. A clinician may use the result to identify whether the patient has a high anion gap metabolic acidosis, a normal anion gap metabolic acidosis, or a low gap pattern that suggests another issue.
In clinical interpretation, the number itself is only part of the picture. The context matters: symptoms, kidney function, serum bicarbonate, and other markers such as serum creatinine and blood urea nitrogen help determine what the calculation really means.
Using an anion gap calculator can be especially helpful when reviewing:
- Unexpected low bicarbonate Possible acid retention in kidney disease Changes in electrolytes during illness Suspected causes of metabolic acidosis
Why the Anion Gap Matters in Kidney Disease
In chronic kidney disease, the kidneys gradually decrease their ability to remove acid and restore bicarbonate. This can result in metabolic acidosis, which may present as a elevated or abnormal anion gap. As kidney function worsens, acid retention becomes more common, making the anion gap a useful marker of altered metabolic status.
In acute kidney injury, the problem may progress rapidly. A sudden decline in filtration can cause rapid changes in serum electrolytes and acid handling. That makes the anion gap calculator a valuable way to assess whether the patient’s acidosis is likely related to kidney failure or another acidosis causes category.
In advanced renal dysfunction, renal impairment may worsen uremia, which can elevate unmeasured acids in the blood. This is why an elevated gap is often reviewed alongside blood urea nitrogen and serum creatinine. Together, these lab results can suggest worsening kidney function and a broader metabolic derangement.
The anion gap does not diagnose kidney disease by itself. Instead, it supports the overall clinical interpretation of the acid-base picture. When paired with the patient’s history, symptoms, and other laboratory testing, it helps identify whether the pattern is consistent with kidney-related acidosis or another disorder.
How to Interpret Elevated, Normal, and Reduced Anion Gap Results
Reading the anion gap requires recognizing the balance of acid-base balance. A result may be elevated, normal, or low, and each pattern suggests different possibilities.
A high anion gap often indicates there are extra additional acids in the blood. This pattern is commonly found in high anion gap metabolic acidosis, which may occur with kidney disease, lactic acidosis, ketoacidosis, or toxic ingestions.
A normal anion gap does not rule out acidosis. Indeed, normal anion gap metabolic acidosis can happen when bicarbonate is lost and chloride rises to maintain balance. This can be seen in certain renal tubular disorders or other conditions that affect acid handling without causing a large increase in unmeasured acids.
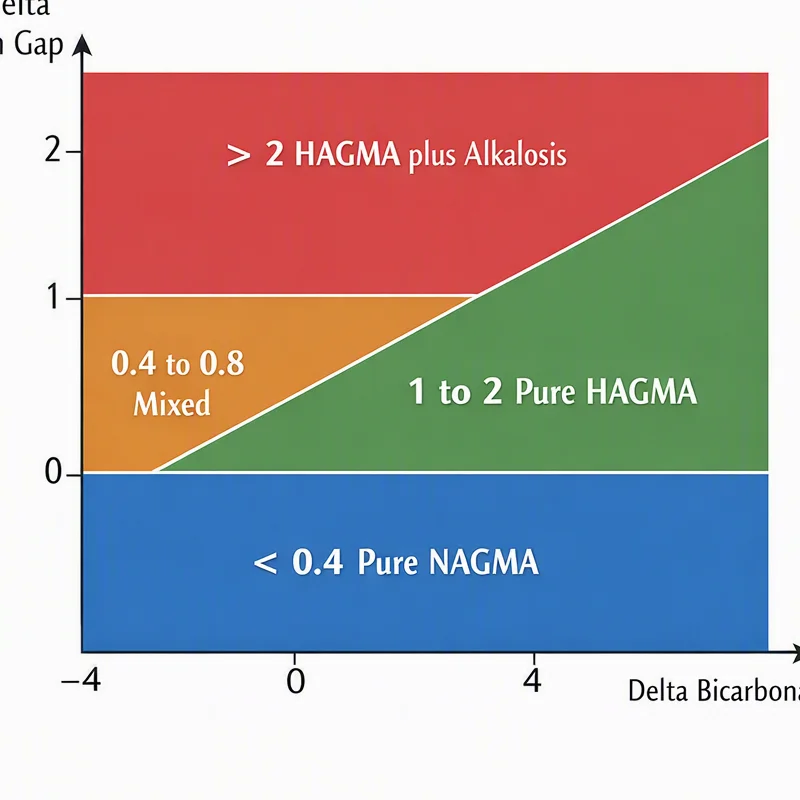
A low anion gap is uncommon, but it can point to low albumin, lab artifact, or other unusual conditions. Because the gap is influenced by many factors, it should always be reviewed in combination with the full electrolyte pattern and the patient’s clinical picture.
Practical interpretation includes:
- High anion gap: look for added acids or reduced acid clearance Normal anion gap: consider bicarbonate loss or chloride retention Low anion gap: consider protein changes, analytical issues, or uncommon causes
No matter the pattern, the goal is to understand the underlying acid-base disorder and whether the abnormality is driven by kidney-related changes, another metabolic condition, or a testing issue.
Frequent Causes of Increased Anion Gap in Renal Conditions
Various conditions can elevate the anion gap in patients with kidney disease. The main cause is uremia, which occurs when the kidneys cannot adequately remove acid waste products. As acid accumulates, the gap rises and the patient may develop worsening metabolic acidosis.
Lactic acidosis is another important cause. It can occur when tissues do not receive enough oxygen or when there is serious illness, infection, or poor perfusion. In a patient with renal dysfunction, lactic acid may be cleared more slowly, making the acid-base disturbance more severe.
Ketoacidosis is also a frequent reason for a high gap. This may happen in uncontrolled diabetes, prolonged fasting, or other states of increased fat breakdown. Even when the primary problem is not the kidneys, reduced renal reserve can increase the acid load.
Toxic ingestions are important to consider as well. Some substances create acids or interfere with metabolism, leading to an elevated gap. In these cases, the anion gap calculator helps uncover a potentially fatal cause of acidosis that may otherwise be missed.
Other points to keep in mind:
- Declining kidney function can reduce acid clearance Blood urea nitrogen and serum creatinine may rise with renal decline A high gap may reflect multiple processes at the same time
A close review of the clinical story is essential, because a high gap in a patient with renal impairment can signal either kidney-related acid retention or another serious diagnosis occurring alongside it.
What May Reduce the Anion Gap
A low anion gap is less common than a high one, but it still deserves attention. One of the main causes is hypoalbuminemia, since albumin is a negatively charged protein that adds significantly to the normal gap.
When serum albumin is low, the measured gap may appear artificially reduced even if the patient has a real acid-base problem. This is why the result may need albumin adjustment before interpretation. In clinical practice, hypoalbuminemia can occur in chronic illness, poor nutrition, inflammation, or protein-losing conditions.
Multiple myeloma can also lower the gap because abnormal proteins may shift the pattern of measured ions. This is less frequent than hypoalbuminemia, but it is an important consideration when the lab pattern does not fit the clinical picture.
Lab error should always be considered. Sample handling problems, instrument issues, or transcription mistakes can all distort the result. If the value seems unexpected, repeating testing is often appropriate before drawing conclusions.
Possible causes of a low gap include:
- Hypoalbuminemia Changes in albumin concentration Multiple myeloma Lab error
Because a low gap can hide a true acid-base disorder, it should not be ignored, especially in patients with kidney-related illness.
Modified Anion Gap and Albumin Correction
Because serum albumin strongly influences the anion gap, many clinicians use a corrected anion gap when albumin is abnormal. This albumin correction helps determine what the gap would be if the albumin were in the expected range.
The concept is simple: low albumin lowers the measured gap, so adjustment helps avoid missing a true high anion gap. This matters particularly in patients with kidney disease, where malnutrition, inflammation, or chronic illness may lower albumin levels.
An albumin-adjusted interpretation is often more precise than the raw number alone. However, the exact correction may differ by institution or calculator. Because of that, it is important to know the reference range used by the lab and the method used by the calculator.
Using a corrected value can improve clinical interpretation when the picture is unclear. For example, a patient with low albumin may have a seemingly normal gap even though acid retention is present. After adjustment, the result may better reflect the underlying metabolic state.
Key points about correction:
- Low albumin can obscure a true elevation Corrected anion gap can improve diagnostic accuracy The chosen reference range should align with the lab method
In short, albumin adjustment is not always required, but it is often helpful when evaluating metabolic acidosis in patients with abnormal protein levels.
Associated Lab Tests to Review with the Anion Gap
The anion gap calculator is most useful when viewed alongside other tests. A basic metabolic panel provides the core values needed for the calculation and often includes clues about kidney-related acid-base problems. In many cases, a clinician will also review an arterial blood gas to better understand pH and respiratory compensation.
Serum creatinine and blood urea nitrogen are vital for assessing kidney function. If both are increased, the result may suggest declining renal impairment or an acute kidney injury process. They help determine whether the abnormal gap is likely tied to impaired filtration.
Other relevant values include:
- Bicarbonate for assessing buffering capacity Sodium and chloride for the calculation itself Potassium for overall electrolyte assessment Serum albumin for needed correction
The arterial blood gas provides important detail about oxygenation, pH, and compensation, which can help separate respiratory from metabolic processes. Together, these tests give a more complete view of acid-base balance and overall metabolic status.
For a patient with abnormal results, the combination of laboratory testing can clarify whether the issue is uremia, lactic acid buildup, ketosis, or another acid-base disturbance.
When to Seek Medical Evaluation
Anyone with abnormal lab values and concerning symptoms should seek prompt medical evaluation. This is especially relevant when there may be acute kidney injury, severe dehydration, or worsening metabolic acidosis.
Warning signs can include nausea, vomiting, confusion, rapid breathing, weakness, or reduced urine output. These symptoms do not prove kidney failure, but they can signal a significant acid-base disorder that needs prompt attention.
If the anion gap is elevated and the patient also has high serum creatinine or blood urea nitrogen, kidney-related acid retention becomes more likely. On the other hand, a standard or low gap does not exclude a problem if symptoms are progressing.
Obtain medical attention without delay if:
- Signs indicate potential severe acidosis There is concern for acute kidney injury Dehydration may be worsening renal function Findings are unusual or rapidly changing
Since acid-base problems can progress rapidly, it is best not to rely on a single number. The anion gap calculator is a useful guide, but the final decision should come from a full clinical assessment.
Common Questions
Why use an anion gap calculator for kidney disease assessment?
An anion gap calculator is used to aid in assessing acid-base balance in people with kidney disease. It can reveal whether there is a high anion gap pattern that suggests metabolic acidosis, acid retention from reduced kidney function, or another metabolic cause that needs evaluation.
What is the formula for calculating the anion gap from a basic metabolic panel?
You typically use the values for sodium, chloride, and bicarbonate from the basic metabolic panel. The common formula is sodium minus the sum of chloride and bicarbonate. Some methods also include potassium, so the exact reference range can vary by calculator and lab.
What is the significance of a high anion gap in chronic kidney disease?
In chronic kidney disease, a high anion gap may indicate accumulation of acids because the kidneys are not clearing them well. This can be part of high anion gap metabolic acidosis and may reflect uremia or another added acid burden such as lactic acidosis or ketoacidosis.
Should the anion gap be corrected for albumin?
Yes, it often should be considered when serum albumin is low. Hypoalbuminemia can make the measured gap appear falsely normal or low. A corrected anion gap with albumin correction may give a more accurate picture of the underlying acid-base problem.
What other lab tests should be checked with an unusual anion gap?
Helpful tests include a metabolic panel, ABG, creatinine level, and urea nitrogen. Reviewing potassium, HCO3, and serum albumin can also strengthen medical interpretation and aid in identifying the cause of the unusual result.