What the Anion Gap Indicates
The anion gap is a practical way to estimate the difference between routinely measured electrolytes in the blood and the not directly measured charged particles that help maintain acid-base balance. In clinical practice, it is most often used to help evaluate metabolic acidosis and other acid-base disorders.
An anion gap calculator uses typical laboratory values such as sodium, chloride, and bicarbonate to assist in detecting whether there are additional unmeasured anions in the plasma. In usual practice, this is a helpful part of clinical interpretation because it can indicate a specific metabolic derangement even before the full picture is known.
The underlying idea is simple: sodium represents most of the measured positive charge, while chloride and bicarbonate represent primary measured negative charges. The gap illustrates the relationship between these laboratory values and the unseen ions that are not directly reported on a standard electrolyte panel.
Although the number itself is only one piece of the puzzle, it is a valuable screening tool for identifying an abnormal acid-base state and guiding a more focused diagnostic algorithm. In settings such as critical care, the anion gap can help identify whether a patient likely has an acid-base disturbance that needs prompt workup.
How to Work with an Anion Gap Calculator
To use an anion gap calculator, begin by starting with a serum chemistry panel and enter the input values for sodium, chloride, and bicarbonate. Most calculators also support entry of serum albumin, which is essential when you want an albumin-corrected anion gap.
The calculator uses the anion gap formula and gives a value that can be compared with the expected reference range. A result above the expected range may point to excess acids or other unmeasured anions, while a normal value does not fully exclude an acid-base disorder.
For clinical use, the process should be methodical:
- Check the basic electrolyte values on the serum chemistry panel. Determine whether serum albumin is available. Enter the input values carefully to avoid transcription mistakes. Assess the calculated anion gap in the context of the patient’s symptoms and other laboratory values. Assess whether an albumin correction is needed before interpreting the result.
The calculator is best used as a supportive aid, not as a standalone diagnosis. A single number does not replace bedside assessment, medication review, or more advanced acid-base analysis. Instead, it helps clinicians spot patterns that warrant a closer look.
Anion Gap Formula and Calculation Methods
The classic anion gap formula is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Several laboratories and references include potassium in the formula:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Each version are used in clinical practice, but the sodium-only version is more common because potassium contributes relatively little to the total. Still, it matters to know which method your calculator uses so you can check the result with the correct reference range.
The corrected anion gap is especially important when serum albumin is low. Because albumin is a major unmeasured anion, low levels can make the uncorrected gap appear falsely normal. In that setting, albumin correction helps reveal hidden acid accumulation that might otherwise be missed.
For practical use, the calculator should explicitly show which method is being applied. That prevents confusion when the result is reviewed alongside other electrolytes and supports more reliable diagnostic support in real-time care.
Typical Anion Gap Range and Meaning
The anticipated reference range for this measurement depends on the testing method, instrument platform, and whether potassium is included. As a result, there is not one fixed normal number. Rather, clinicians should interpret the result using the site-specific range reported with the patient’s laboratory values.
A normal anion gap generally suggests that the balance between measured cations and anions is in the normal range, but it does not rule out disease. A patient may still have normal anion gap metabolic acidosis, especially if there is a compensatory rise in chloride.
A high anion gap indicates accumulation of acids or other unmeasured substances. That finding is especially relevant when evaluating possible metabolic acidosis. However, the degree of elevation may be reduced by hypoalbuminemia or affected by lab variation.
Clinical review should always consider the full clinical picture:
- Does the patient show acidemia on blood gas testing? Is there evidence of shock, hypoperfusion, or toxin exposure? Do the electrolytes show concurrent hyperchloremia? Is the bicarbonate reduced in a way that matches the expected pattern?
These considerations turn a raw value into meaningful clinical interpretation.
Origins of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis develops when acids build up more quickly than the body can clear them or buffer them. This results in a elevation in unmeasured acid anions and a fall in serum bicarbonate.
Frequent causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, poor oxygen delivery or mitochondrial dysfunction causes lactate accumulation. In ketoacidosis, ketone bodies build up in states such as diabetic decompensation, starvation, or alcohol-related metabolic stress. In renal failure, the kidneys cannot eliminate acid effectively, so retained organic acids increase the anion gap.
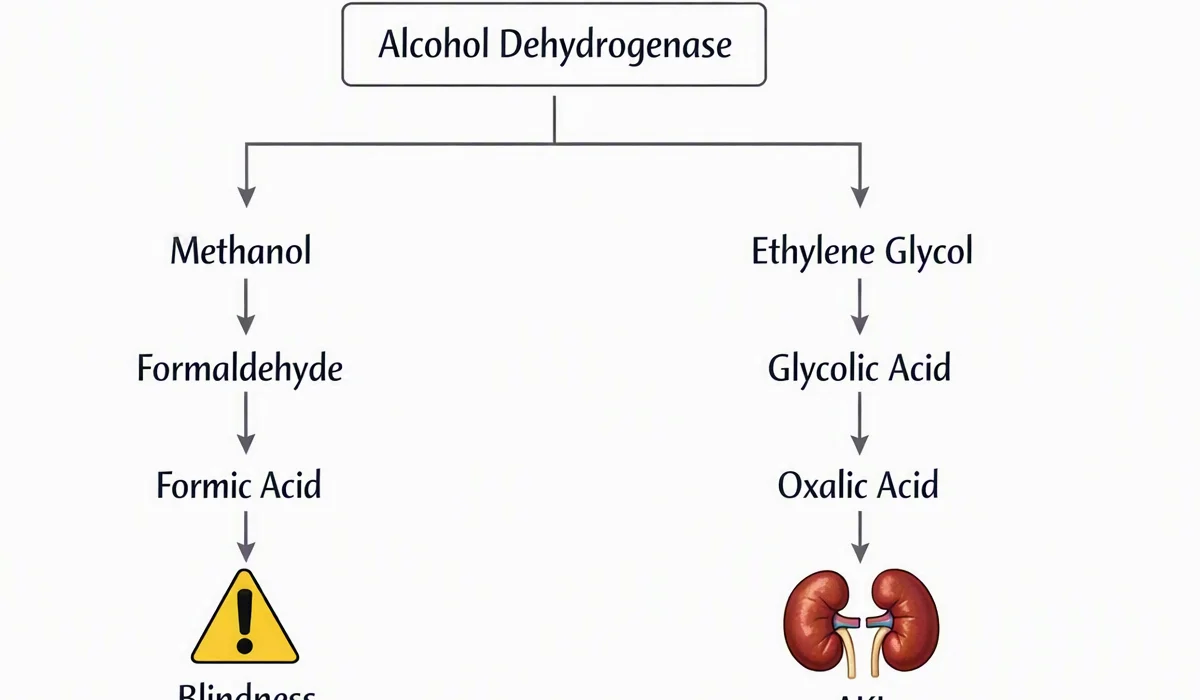
Alternative causes can include toxic ingestions, but the most clinically common scenarios are those above. The practical value of the calculator is that it notifies clinicians to a pattern that suggests a metabolic derangement even before all confirmatory testing is complete.
In daily assessment, a high result should prompt a search for the underlying driver rather than a focus on the number alone. The next step is to identify whether the elevation is due to hypoperfusion, insulin deficiency, kidney dysfunction, or another process affecting acid-base balance.
Sources of Normal Anion Gap Metabolic Acidosis
normal anion gap metabolic acidosis can also be called hyperchloremic acidosis. In this setting, bicarbonate is lost or consumed, and chloride rises to preserve electroneutrality. As a result, there is a decreased serum bicarbonate with a relatively unchanged gap.
A classic cause is diarrhea, which leads to immediate gastrointestinal bicarbonate loss. A further major cause is renal tubular acidosis, where the kidneys fail to appropriately acidify urine or reclaim bicarbonate, leading to persistent acid-base disorder.
Because chloride increases as bicarbonate declines, the measured chloride may appear markedly high. That pattern helps differentiate this disorder from a raised-gap process. Still, overlapping disorders may occur, so the calculator should be viewed as a single part of a broader diagnostic algorithm.
In practice, recognizing hyperchloremia alongside low bicarbonate can assist in narrowing down the cause of metabolic acidosis and prevent overlooking a normal-gap pattern that requires a different workup than lactic acidosis or ketoacidosis.
How Albumin Affects the Anion Gap
Serum albumin is a key source to the body’s unmeasured negative anion load. Because of that, hypoalbuminemia can lower the measured anion gap even when acid build-up is present. This is why albumin-corrected anion gap values are so helpful in patient assessment.
The connection is grounded in protein charge: albumin carries overall negative charge at physiologic pH, so when albumin drops, the measured gap may also fall. In patients with critical illness, low albumin is common, which makes uncorrected results less reliable.
Albumin correction helps clinicians prevent a false sense of confidence. A patient with sepsis, shock, or organ failure may have a “normal” raw value but still harbor a clinically significant high anion gap metabolic acidosis once the correction is applied.
For this reason, many clinicians choose using a calculator that includes plasma albumin or serum albumin as an input. That approach improves the usefulness of the anion gap calculation as a practical screening tool and supports better recognition of unmeasured acid excess.
Clinical Mistakes and Common Calculation Errors
A number of pitfalls can make an otherwise useful result inaccurate. One common issue is laboratory error, including contaminated specimens, delayed processing, or an analyzer problem. If the result does not fit the patient’s condition, verification is essential.
One other mistake is failing to recognize mixed acid-base disorders. A patient may have both an elevated gap and a concurrent metabolic process that hides the expected bicarbonate change. This is especially relevant in sicker inpatients.
Potassium omission is another source of confusion. If a calculator includes potassium and the clinician expects a sodium-only formula, the numbers will not match. Always know which anion gap formula is being used.
Unit mismatch can also distort the calculation. Input values must be in the correct units, and the calculator should not be fed values from different reporting systems without confirmation. Even small entry errors can create a false impression of a major electrolyte disturbance.
Good clinical practice is to treat the calculator as one part of an acid-base analysis, not the final answer. If the result is unexpected, recheck the raw electrolytes, review the chart, and compare the trend with prior laboratory values.
When to Reassess Labs or Request Further Testing
Additional testing is appropriate when the anion gap does not match the clinical picture, when the patient appears unstable, or when the result suggests a serious metabolic derangement. A repeat panel can help confirm whether the abnormality is ongoing or due to transient variation.
An arterial blood gas is useful when you need a more complete view of acid-base status, including pH and respiratory compensation. This is especially helpful if the bicarbonate value and clinical findings do not align.
Other focused checks may include serum lactate when lactic acidosis is considered, or ketones when ketoacidosis is possible. If the history suggests intake of a harmful substance or an atypical osmotically active compound, an osmolar gap may offer helpful clues.
Rechecking is also appropriate if there is concern about laboratory error, sample handling issues, or a changing clinical condition such as evolving renal failure. The goal is to use the calculator as a prompt for directed workup, not as an endpoint.
When interpreted correctly, the tool can inform timely decisions, enhance recognition of metabolic acidosis, and support a more systematic response to acid-base abnormalities.
FAQ About the Anion Gap
What is an anion gap calculator used for?
An anion gap calculator is used to determine the difference between measured cations and anions on a serum chemistry panel. In practice, it helps assess acid-base balance, identify possible unmeasured anions, and support evaluation of metabolic acidosis. It is especially useful as a screening tool and part of broader clinical interpretation.
What is a normal anion gap range?
The normal range depends on the laboratory method and whether the calculation includes potassium. Because of lab variation, the best comparison is the lab-specific reference range that accompanies the patient’s results. A normal number does not exclude all acid-base disorders, especially normal anion gap metabolic acidosis.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate. Some methods include potassium. The key is to use the same method as the calculator or laboratory report and check the units before interpreting the result.
Why do you correct the anion gap for albumin?
You account for for albumin because serum albumin is a major normal AG mEq/L range unmeasured anion. With hypoalbuminemia, the raw gap may seem falsely normal. An albumin-corrected anion gap helps uncover hidden acid build-up and strengthens the detection of high anion gap metabolic acidosis, especially in critical illness.
What conditions cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. Other causes can occur, but these are among the most frequent and medically relevant. When the gap is high, clinicians should evaluate the underlying source of acid production or impaired acid clearance and consider additional testing if needed.