An anion gap calculator is a helpful medical calculator created to support interpret an electrolyte panel and identify important patterns in serum chemistry. By comparing serum sodium, serum chloride, and serum bicarbonate, it can reveal clues about metabolic acidosis, electrolyte imbalance, and other forms of acid-base disorder. Although the calculation is simple, the clinical meaning depends on the overall blood chemistry, the patient’s symptoms, and key modifiers such as albumin.
In the right context, the anion gap is more than a number. It is a screening tool that supports clinical interpretation, highlights unmeasured anions, and helps narrow the diagnostic workflow. It also helps clinicians understand when a result may reflect lab variability, a corrected value problem, or a true clue to serious disease.
What Is the Anion Gap?
The anion gap is a computed value derived from an electrolyte panel that approximates the discrepancy between routinely measured cations and anions in the blood. It is not directly measured; rather, it reflects the equilibrium between positively charged and negatively charged substances in the serum electrolytes. In everyday practice, it is mainly used to help diagnose metabolic acidosis and inform acid-base interpretation.
Because routine testing does not measure every charged particle in the blood, the anion gap serves as a clue to the presence of unmeasured anions. These may include lactate, ketones, toxins, or other acids. A raised result often points toward high anion gap metabolic acidosis, while a normal or low value may suggest normal anion gap metabolic acidosis, a measurement issue, or another process affecting the serum balance.
In basic terms, the anion gap helps answer a clinical question: is there an anion deficit or too much of unmeasured acids in the bloodstream? That makes it a helpful starting point for reviewing the patient’s lab results and deciding what to investigate next.
How to Calculate the Anion Gap
The calculation relies on three values from the electrolyte panel: sodium, chloride, and bicarbonate. The usual anion gap formula uses these measured concentrations to estimate the gap between positive and negative ions. Because the values are part of routine serum chemistry, the calculation can be performed rapidly at the bedside or within an anion gap calculator.
It helps to understand the formula because the result depends clinical interpretation of AG on the concentration of each component. Slight variations in serum sodium, serum chloride, or serum bicarbonate can change the number and alter the clinical interpretation. A calculator helps with speed, but the user still needs to understand the underlying pathophysiology.
Standard Anion Gap Formula
The classic calculation is:
Na minus Cl minus HCO3in which Na represents sodium, Cl is chloride, and HCO3 is bicarbonate. The calculation steps are straightforward:
- Take the measured serum sodium. Then subtract the measured serum chloride. Finally subtract the measured serum bicarbonate.
This value is then compared with a reference range, which can vary depending on the laboratory method and analyzer. In many settings, the reference interval is roughly in the single digits to low teens, but always rely on the laboratory-specific reference range rather than a fixed universal number.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. This can fall inside the expected range, but interpretation depends on whether the patient also has metabolic acidosis, altered albumin, or another abnormality.
Corrected Anion Gap for Albumin
Albumin is a major unmeasured anion, so low albumin can make the gap appear deceptively normal or low. This is especially important in hypoalbuminemia, where the apparent result may underestimate the true burden of acids. In those cases, the corrected anion gap is more useful than the raw value.
The adjustment accounts for the effect of reduced protein binding and less negatively charged molecules in the serum. If albumin is low, the body has fewer baseline unmeasured anions, which can mask a clinically important acid load. That is why the albumin-adjusted result is often a better corrected value for clinical interpretation.
In real-world terms, a patient with hypoalbuminemia may have a “normal” anion gap that still conceals high anion gap metabolic acidosis. A calculator that applies albumin correction can improve the diagnostic yield and limit missed acid-base disorder patterns.
How to Read Elevated, Average, and Reduced Anion Gap Findings
Interpretation depends on the trend, not just the value. A high anion gap typically points to extra unmeasured acids. A standard anion gap can still occur with metabolic acidosis, especially when bicarbonate loss is balanced by increased chloride. A decreased anion gap is less common but can be a useful clue or an artifact.
When using an anion gap calculator, start by asking whether the result fits the patient’s symptoms and other lab results. The same number may represent very different things depending on pH, bicarbonate, albumin, and whether there is a concurrent respiratory disorder. This is why acid-base interpretation is always a medical task, not a purely mathematical one.
A elevated anion gap usually suggests high anion gap metabolic acidosis. A typical anion gap with acidosis often points toward normal anion gap metabolic acidosis and may be associated with hyperchloremia. A decreased anion gap often brings up laboratory error, low albumin, or uncommon causes such as excess unmeasured cations.
Common Causes of Elevated Anion Gap
High results commonly suggest more acid being produced, reduced acid removal, or intake of compounds that introduce unmeasured anions. The most common diagnostic categories include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Recognizing these patterns helps make a number into a useful diagnostic clue.
Lactic acidosis develops when tissue hypoperfusion, sepsis, hypoxia, or mitochondrial dysfunction causes lactate accumulation. This is a typical cause of high anion gap metabolic acidosis. Ketoacidosis may develop in diabetes, alcohol use, or prolonged fasting, and the accumulating ketones widen the anion gap.
Renal failure can result in retained acids and reduced excretion of unmeasured anions. In advanced kidney dysfunction, the gap may rise gradually as acid handling worsens. This is why kidney function should be reviewed alongside the electrolyte panel, especially when the clinical interpretation indicates a steadily advancing metabolic problem.
Toxic ingestions are another key category. Toxic alcohol ingestion can create a substantial gap by generating acidic metabolites, and salicylate poisoning can lead to mixed acid-base patterns with an elevated gap. These cases often require a thorough diagnostic workflow because the acid-base picture may be multifaceted and time-sensitive.
In cases where the Anion Gap Is Normal
A result in the normal range does not eliminate acid-base disease. Indeed, normal anion gap metabolic acidosis is common and often associated with bicarbonate loss with compensatory chloride retention. This pattern is frequently called hyperchloremic metabolic acidosis because chloride rises as bicarbonate falls, keeping the gap in the reference interval.
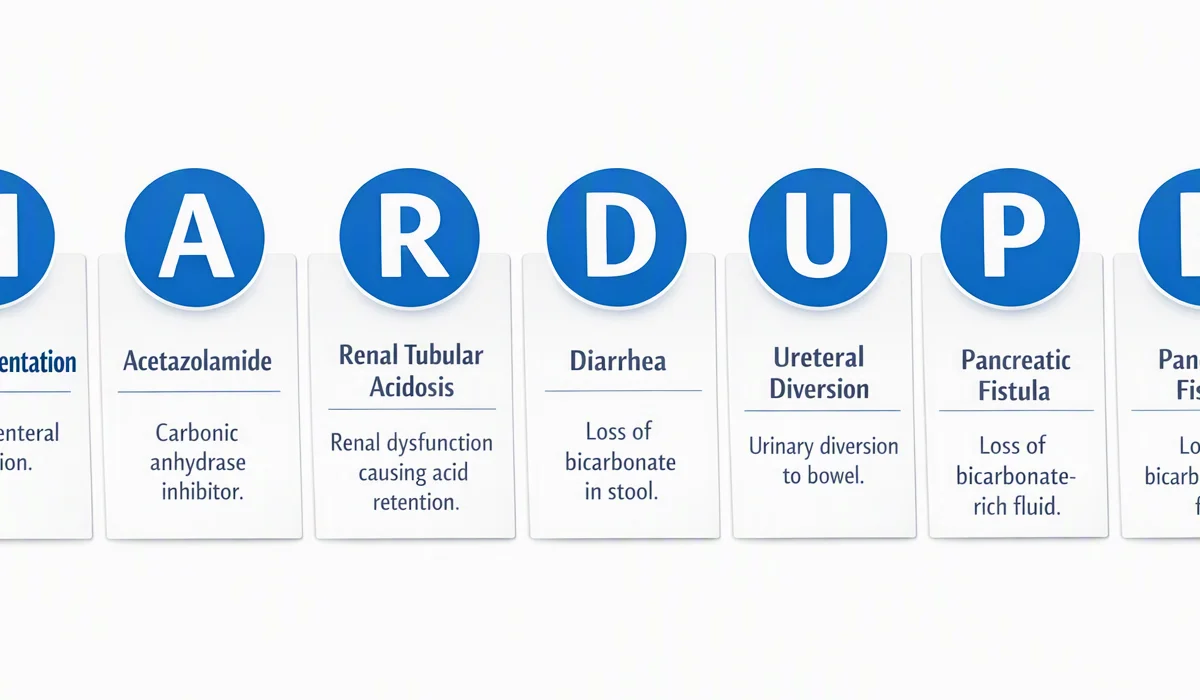
A normal gap can be seen in diarrhea, renal tubular acidosis, and other bicarbonate-losing states. It can also arise during recovery from a previously elevated gap, when unmeasured anions are being cleared and chloride has risen in compensation. Because of this, the change over time matters as much as the single result.
A low anion gap is uncommon but should not be dismissed. Laboratory error is one of the first things to consider, because small measurement issues can strongly affect the calculation. A low result can also occur with paraproteinemia, where abnormal proteins act as cations or alter the balance of measured ions. In other situations, lithium may function as an unmeasured cation and lower the gap.
When chloride is unexpectedly high, look for hyperchloremia, which may indicate a true normal-gap acidosis or a compensatory change. In each case, the finding should be interpreted in the context of the overall acid-base disorder, the patient’s symptoms, and the rest of the electrolyte panel.
Stepwise Process for Electrolyte Panel Interpretation
A structured approach improves electrolyte panel interpretation and decreases missed diagnoses. The goal is not only to compute the value, but to put it within a wider diagnostic workflow.
- Step 1: Review sodium, chloride, and bicarbonate on the electrolyte panel. Step 2: Determine the anion gap using the anion gap formula or an anion gap calculator. Step 3: Check the result with the lab’s reference range. Step 4: Review albumin and think about a corrected anion gap if hypoalbuminemia is present. Step 5: Review the ABG if available to assess pH, respiratory compensation, and mixed disorders. Step 6: If the gap is elevated, look for lactate, ketones, kidney function, and toxic exposures. Step 7: Calculate the delta gap when a mixed disorder may be present.
The ABG adds crucial context because it shows whether there is acidemia, alkalemia, or compensation that is masking the primary problem. The delta gap is important when an elevated anion gap does not fully explain the bicarbonate change, indicating a mixed acid-base disorder. This stepwise process refines acid-base interpretation and promotes more accurate clinical decisions.
Always interpret the numbers with the patient’s symptoms, medications, kidney function, and overall presentation. The best results come from combining calculator output with clinical context.
Drawbacks of the Anion Gap Calculator
An anion gap calculator is helpful, but it is not definitive. One major limitation is the albumin effect, which can hide clinically important acid accumulation when albumin is low. Without compensation, the calculated result may underestimate the severity of the disorder.
Another limitation is the presence of unmeasured cations such as lithium or other unusual positively charged substances. These can lower the gap and make interpretation more difficult. In addition, measurement variability between analyzers can shift the result enough to move it across the reference interval, especially when the number is borderline.
It is also important to remember that the gap is a clue, not a diagnosis. It does not tell you the exact cause of metabolic acidosis, and it does not replace broader assessment of blood gases, renal function, lactate, ketones, and medication or toxin exposure. Used well, it improves the diagnostic picture; used alone, it can mislead.
In other words, the calculator is most valuable as part of a full interpretation guide. It helps organize the problem, but the final answer comes from synthesis.
Common Questions
What is the normal range for the anion gap?
The anion gap normal range depends on the laboratory method and analyzer, so the best number to use is the lab-specific reference range. In many settings, the range is in the single digits to low teens. Always interpret the result in the context of the local serum chemistry method and the patient’s clinical picture.
How does albumin affect the anion gap?
Albumin is a major unmeasured anion, so low albumin can make the anion gap appear falsely low or normal. This is why hypoalbuminemia can hide important acid-base abnormalities. A corrected anion gap helps adjust for that effect and improves clinical interpretation.
What does a high anion gap mean on an electrolyte panel?
A high anion gap usually means there are additional unmeasured anions in the blood, often due to high anion gap metabolic acidosis. Frequent causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohol ingestion, and salicylate poisoning. The result is a helpful clue, not a final diagnosis.
Can a normal anion gap still indicate metabolic acidosis?
Yes. A normal result can still be indicative of normal anion gap metabolic acidosis, especially when bicarbonate loss is balanced by rising chloride. This pattern is often called hyperchloremic metabolic acidosis. That is why the full electrolyte panel, ABG, and clinical context remain essential.
Why might an anion gap calculator give a low result?
A low result may reflect laboratory error, low albumin, paraproteinemia, or the presence of lithium or other unmeasured cations. It can also occur because of normal measurement variability around the reference interval. If the number does not fit the clinical picture, rechecking the test and broader acid-base interpretation are important.