What Is the Anion Gap?
The anion gap is a derived value used to assess acid-base balance and recognize certain kinds of electrolyte imbalance. It comes from a standard serum chemistry panel and contrasts measured positive ions with measured negative ions in the blood. In practical terms, it helps clinicians identify a hidden metabolic derangement that may not be clear from symptoms alone.
The classic calculation uses serum sodium, serum chloride, and serum bicarbonate. These electrolytes are part of the body’s buffering system, which helps maintain stable pH. When the balance shifts, the anion gap can increase or stay normal depending on the underlying cause of the problem.
One reason the anion gap is useful is that it acts as a diagnostic clue during a medical evaluation. A changed gap can point toward a specific acid-base disorder, especially metabolic acidosis. It is not a diagnosis by itself, but it can refine the differential diagnosis and support follow-up testing.
The normal reference range varies somewhat by laboratory because of differences in measurement methods and reporting. That is why the lab’s own result range matters more than a single universal number. Still, the basic concept remains the same: the anion gap reflects the difference between measured ions and can reveal an anion deficit or an excess of unmeasured acids.
How the Anion Gap Calculator Works
An anion gap calculator is a fast clinical utility that follows the standard formula to values entered from a serum chemistry panel. Most calculators use sodium, chloride, and bicarbonate. Some also include potassium, depending on the formula being used and the institution’s preference.
The usual formula is:
Anion gap = sodium - (chloride + bicarbonate)
When potassium is included, the formula becomes:
Anion gap = sodium + potassium - (chloride + bicarbonate)
The calculator yields a calculated value that aids assess whether an acid load is present. In clinical use, this is more than just a math exercise. It is a screening tool that can indicate whether a patient may have metabolic acidosis and whether the pattern suggests a high-gap or normal-gap process.
Because the result is influenced by measurement technique and lab-specific calibration, the calculator should always be interpreted in context with the rest of the laboratory result. It works best as part of a broader clinical interpretation rather than as a single number.
For example, low bicarbonate with a high gap suggests accumulation of unmeasured acids. Low bicarbonate with a normal gap often suggests a loss of bicarbonate rather than acid accumulation. That distinction is key to understanding the test.
Anion Gap Metabolic Acidosis: What the Result Means
Metabolic acidosis indicates the blood has become more acidic because bicarbonate has fallen, acid has risen, or both. The anion gap helps sort the problem into high anion gap metabolic acidosis or normal anion gap metabolic acidosis. This classification provides an important diagnostic hint about the likely mechanism.
A high anion gap usually suggests the presence of unmeasured acids. These acids use up bicarbonate during buffering, which raises the gap. This pattern often points to problems such as lactic acid buildup, ketone production, kidney dysfunction, or ingestion of certain toxins.
A normal anion gap result does not mean the patient is normal. It usually means bicarbonate has been lost and chloride has risen to maintain electrical neutrality, producing a pattern often called hyperchloremic acidosis. This is a different type of acid-base disorder and requires a different thought process.
Knowing the pattern matters because the treatment depends on the cause. A patient with high-gap acidosis may need urgent assessment for sepsis, hypoperfusion, diabetes, or toxin exposure. A patient with normal-gap acidosis may need evaluation for gastrointestinal losses, renal tubular defects, or medication effects.
In short, the anion gap is a practical way to recognize the biochemical signature of acid-base balance disturbances. It helps clinicians move from a general finding of metabolic acidosis to a more targeted investigation of the underlying cause.
How to Determine the Anion Gap Step-by-Step
Determining the anion gap is straightforward when you have the main electrolyte values. The standard procedure use sodium, chloride, and bicarbonate, with optional inclusion of potassium.
- Step one: Obtain the serum electrolyte values from the lab report. Next step: Verify the values for serum sodium, serum chloride, and serum bicarbonate. Next: Add chloride and bicarbonate together. Last: Subtract that sum from sodium.
Applying the basic formula:
Anion gap = sodium - (chloride + bicarbonate)
If the calculator includes potassium, add it to the sodium value before subtracting the other electrolytes. Potassium is generally a lesser component of the formula, but it can slightly change the result.
For example, if sodium is 140, chloride is 102, and bicarbonate is 22, the calculation is 140 - (102 + 22) = 16. If potassium is included and is 4, the calculation becomes 140 + 4 - (102 + 22) = 20.
That number is then checked with the lab’s reference range. Some labs consider a higher range normal, while others use a reduced one. The key is to interpret the result using the specific reference range attached to the patient’s lab system.
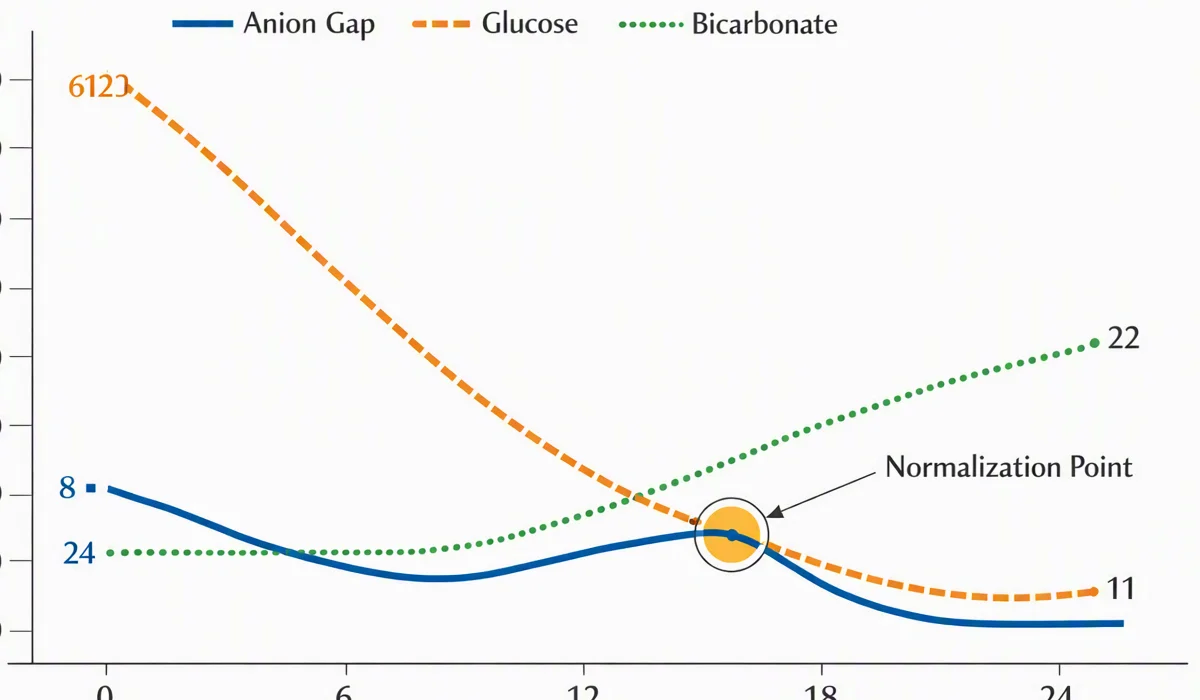
Even when the arithmetic is simple, the meaning is not. The calculated result should always be considered in the setting of the patient’s symptoms, other test results, and overall clinical interpretation.
Corrected Anion Gap and Albumin Correction
Albumin has a significant effect on the anion gap because it is one of the main unmeasured anions in blood. When albumin is low, the measured anion gap may look artificially normal even when a clinically significant acidosis is present. This is why the corrected anion gap matters.
Hypoalbuminemia reduces the baseline gap by lowering the amount of unmeasured negative charge in the plasma. In patients with low albumin, failing to adjust can mask a high-gap process. The correction helps yield a more accurate estimate of the true acid burden.
A commonly used corrected formula includes a small amount to the measured anion gap for every decrease in albumin below the normal range. The exact adjustment may vary by institution, but the principle is the same: low albumin means the observed value may minimize the actual disturbance.
This is why the corrected value is often more clinically meaningful than the raw number. A patient with an apparently normal laboratory result range may still have an elevated corrected gap if albumin is reduced. That can change the interpretation from normal to concerning for hidden high-gap metabolic acidosis.
Albumin adjustment is especially important when the clinical picture indicates serious illness but the uncorrected anion gap does not match. In that setting, the corrected anion gap can identify an important metabolic problem and strengthen the quality of the diagnostic workup.
Typical Causes of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis occurs when acids collect in the body at a faster rate than they can be cleared. The excess acids deplete bicarbonate and widen the gap. The main causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion.
Lactic acidosis develops when oxygen delivery or utilization is compromised, leading to lactate elevation. This can happen in shock, severe infection, hypoxia, seizures, or tissue ischemia. Lactate is an useful clue because it often signals a major underlying cause that needs urgent treatment.
Ketoacidosis is commonly related to uncontrolled diabetes, starvation, or alcohol use. In this situation, ketone accumulation increases the acid load. The resulting metabolic derangement may present with nausea, vomiting, abdominal pain, dehydration, or altered mental status.
Renal failure can also cause a high gap because the kidneys cannot remove acids effectively. As acid builds up, the anion gap rises and bicarbonate falls. This pattern may appear over time in chronic kidney disease or more abruptly in acute kidney injury.
Toxic alcohol ingestion is another important cause, especially when the presentation is severe or unexplained. Certain ingestions generate acids that widen the gap and can cause dangerous neurologic, metabolic, and visual complications. When the history is uncertain, the anion gap may become an initial warning sign.
These conditions are part of the key differential diagnosis for a high-gap result. The calculator does not identify which one is present, but it helps inform the next tests and the urgency of care.
Common Causes of Normal Anion Gap Metabolic Acidosis
Typical anion gap metabolic acidosis occurs when bicarbonate is removed and replaced by chloride, maintaining the overall gap within the reference range. This is often called hyperchloremic acidosis because chloride increases as bicarbonate drops.
A common cause is diarrhea, which results in direct gastrointestinal bicarbonate loss. The body reacts by retaining chloride, and the result is a low bicarbonate state with a normal gap. This pattern is often noted in volume depletion as well.
Renal tubular acidosis is another important cause. In this condition, the kidneys fail to acidify urine or conserve bicarbonate appropriately. The result is an acid-base disorder that can persist despite a seemingly ordinary anion gap.
Other causes of normal-gap acidosis may include medication effects, urinary diversion, or certain kidney disorders, but the major teaching point is simple: the presence of acidosis does not always mean the gap is elevated.
In normal-gap states, the chemistry often shows a chloride shift as bicarbonate falls and chloride rises. This compensation preserves electrical neutrality but indicates a real metabolic problem that still needs a cause-specific evaluation.
Clinical Interpretation and Next Steps
Interpreting the anion gap is especially useful when considered alongside the rest of the patient’s data. If the result suggests acid-base imbalance, the next step is usually a specific diagnostic evaluation. This evaluation may include an arterial gas analysis, lactate level, ketone testing, kidney function testing, and sometimes toxin screening.
An ABG blood helps determine the pH and respiratory compensation. Serum lactate is valuable when lactic acidosis is suspected. Ketone levels aid assess for diabetic or starvation-related ketoacidosis. Kidney studies aid identify whether reduced acid excretion is playing a role to the disorder.
This gap also aids in determining urgency. A markedly high result can suggest a potentially dangerous metabolism-related condition that needs immediate attention. A normal gap along with low bicarbonate may point to an alternative process, for example loss through the gastrointestinal tract or renal tubular dysfunction.
Medical assessment should also look at complaints such as breathlessness, confusion, low fluid levels, nausea and vomiting, abdominal pain, or evidence of infection. The laboratory result is only a single part of the full picture, but it can be a crucial diagnostic clue that directs the next step in treatment.
For this reason, the anion gap calculator is most appropriately seen as a preliminary tool that assists, rather than takes the place of, medical reasoning. It helps structure the differential diagnosis and focus the evaluation promptly.
Drawbacks of an Anion Gap Calculator
An anion gap calculator is helpful, but it has important restrictions. The first is laboratory variation. Different analyzers, measurement methods, and reference intervals can produce slightly different results. This means the same patient may fall into different result categories based on where the test was processed.
The second limitation is the albumin-related effect. Without correction, a reduced albumin level can hide a real raised gap. That is one reason the corrected anion gap is so vital in people with reduced albumin or severe illness.
Another issue is that the gap does not measure directly every relevant ion. Shifts in unmeasured cations, including ionized calcium, may alter interpretation in certain situations. The calculator also does not identify whether the acidosis is acute or chronic, nor does it reveal the exact underlying cause.
Most importantly, the number must be interpreted in clinical context. Symptoms, history, medications, kidney function, and other lab results all affect the meaning of the calculation. A normal value does not exclude disease, and an elevated value does not prove one specific diagnosis.
When used properly, the calculator is a helpful clue. Used alone, it can be misleading. That is why it should always inform broader medical evaluation rather than replace it.
Frequently Asked Questions
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the gap from serum electrolytes and help assess metabolic acidosis. It acts as a screening tool for an acid-base disorder and can point toward a high-gap or normal-gap pattern. Clinicians use it to guide clinical interpretation and guide the next diagnostic steps.
How do you calculate the anion gap in metabolic acidosis?
The usual formula is sodium - (chloride + bicarbonate). Some versions also include potassium. The calculation uses values from the serum chemistry panel and produces a calculated value that is compared with the lab’s reference range.
What does a high anion gap mean?
A high gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It impact of low albumin on AG suggests a high anion gap metabolic acidosis and usually warrants a focused diagnostic workup.
Why do you correct the anion gap for albumin?
You correct it because albumin strongly affects the measured gap. With hypoalbuminemia, the uncorrected result may look normal even when a true metabolic acid load is present. The corrected anion gap gives a more accurate picture of acid-base balance and helps avoid missed diagnoses.
What conditions cause a normal anion gap metabolic acidosis?
Typical causes are loose stools, RTA, and additional problems that result in loss of bicarbonate with a compensatory increase in chloride, also known as hyperchloremic acidosis. Even though the gap is normal, the patient still has a true metabolic acidosis that requires evaluation.