How this anion gap Reflects
The anion gap is a practical way to approximate hidden ions in the blood and to support acid-base balance during a clinical workup. This is most often derived from serum electrolytes, mainly serum sodium, serum chloride, and serum bicarbonate. As these values shift in expected ways, the anion gap can uncover a subtle metabolic disturbance that would otherwise be missed on a basic chemistry panel.
In routine care, clinicians use the anion gap as a diagnostic marker for acid accumulation. A elevated value suggests that unmeasured acids are present in excess, often indicating metabolic acidosis. This makes the calculation very useful as an interpretation guide when evaluating an ill patient, a lab screening result, or a suspected electrolyte imbalance.
The basic anion gap formula typically deducts chloride and bicarbonate from sodium. Some versions also include potassium, but the standard approach excludes it for simplicity and consistency. An anion gap calculator simplifies this step, helping clinicians quickly calculate anion gap values and consider the bigger question: what is causing the abnormality?
Because the calculation is based on measured ions, anion gap in chronic kidney disease it is not a complete picture of physiology. Instead, it is a fast and practical approximation that supports laboratory assessment and more detailed acid-base interpretation. When the result is elevated, it often signals an elevated anion gap state that requires a closer look at renal function, perfusion, toxin exposure, and inherited metabolic disease.
Why Methylmalonic Acidemia Increases the Anion Gap
Methylmalonic acidemia is an acid-related metabolic disorder and an hereditary metabolic disorder in which the body cannot properly break down certain metabolites, leading to the buildup of acidic compounds. That buildup produces acid buildup and commonly leads to a increased anion gap metabolic acidosis. In this setting, the anion gap becomes a clue to the underlying biochemical problem rather than just a number on a report.
The main problem is that methylmalonic acid along with related compounds build up in the bloodstream. These acids deplete buffering capacity, reduce bicarbonate levels, and add to an excess of unmeasured anions. Therefore, the anion gap often increases alongside the severity of the acid-base disorder. That is why a calculator can be helpful in detecting the pattern early, especially when the patient is critically ill and the presentation is not specific.
In methylmalonic acidemia, the overall picture may reflect a metabolic emergency. Patients can show vomiting, poor feeding, lethargy, dehydration, or encephalopathy, and the laboratory findings may show an elevated anion gap long before the full diagnosis is confirmed. The biochemical pattern usually reflects accumulation of toxic metabolites, decreased energy metabolism, and secondary systemic stress. That is why an anion gap calculator can be a useful starting point in interpretation, but not the final step in diagnosis.
The relationship between the measured gap and the disease process is most pronounced when the presentation includes acidosis plus further supportive signs. However, the anion gap alone does not anion gap with potassium included establish methylmalonic acidemia. It acts as a clinical correlation resource that guides clinicians identify a profile consistent with an organic acid accumulation and proceed to targeted workup.
How to Operate an Anion Gap Calculator
To operate an anion gap calculator, input the essential serum electrolytes: serum sodium, serum chloride, and serum bicarbonate. Many tools also support entry of potassium and albumin. The calculator applies the chosen formula and returns the observed gap, which can then be compared with the expected range for the lab.
If potassium is included, the formula may produce a slightly higher value. In many clinical settings, however, potassium is omitted because it contributes less to everyday decision-making and can vary between institutions. The more important step is to recognize whether the result suggests an elevated anion gap and whether that elevation aligns with the rest of the patient’s picture.
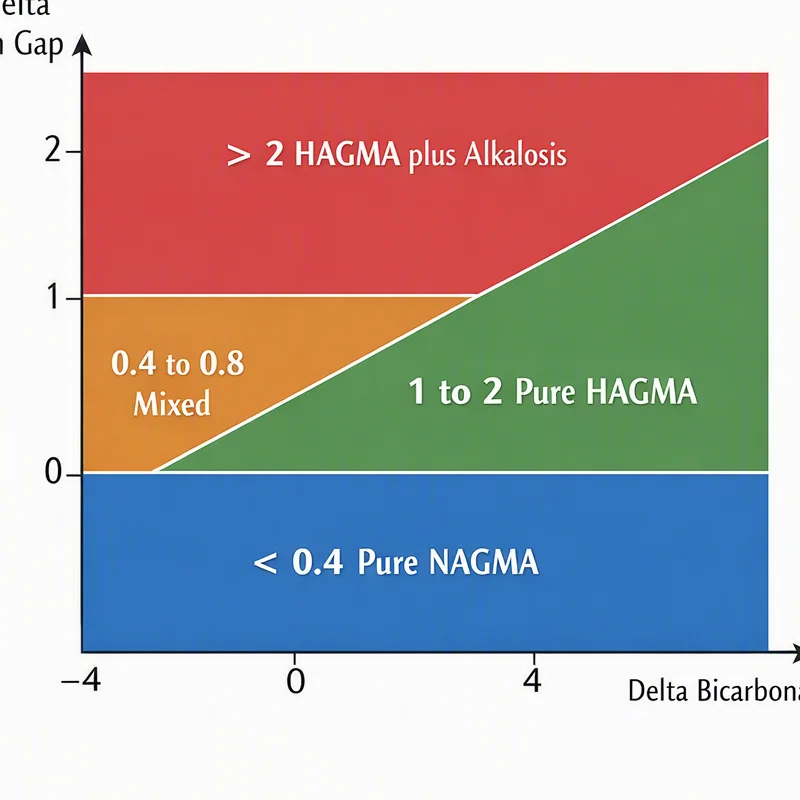
Albumin matters because it is a major unmeasured anion. Low albumin can make the anion gap appear falsely normal or only mildly elevated. That is why many clinicians apply albumin correction to estimate a corrected anion gap. This is especially important in patients with malnutrition, inflammation, liver disease, or prolonged illness, where hypoalbuminemia can mask the degree of acidosis.
A useful ordered approach looks like this:
- Add the available serum electrolytes into the calculator. Check whether the result indicates a high or normal gap. Check albumin and apply albumin correction if needed. Compare the result with the clinical setting and other labs. Consider the number as part of broader acid-base interpretation, not as a standalone answer.
When done correctly, the calculator helps organize the workup and supports a more accurate assessment of acid-base balance. It is most useful when paired with symptoms, kidney function, ketones, lactate, and a blood gas.
Interpreting Increased Anion Gap Findings
A elevated anion gap metabolic acidosis suggests that undetected acids are piling up. In the differential, the typical categories include lactic acidosis, ketoacidosis, and toxin exposure. These mechanisms can coexist with methylmalonic acidemia or obscure it, so interpretation should always be patient-based rather than formulaic.
Lactic acidosis may occur with reduced blood flow, shock, hypoxemia, seizures, or critical illness. It generates excess lactate, which raises the gap. Ketoacidosis occurs in diabetes, prolonged fasting, or starvation states, and the ketone bodies contribute to the elevated gap. Both can coexist with other metabolic abnormalities, making the final pattern more complex than a single diagnosis.
Toxin exposure should also be considered when the gap is high. Salicylates, toxic alcohols, and other poisons may produce a substantial acid burden. In suspected ingestion, the anion gap is a useful clue but not the endpoint. Osmolal gap testing, toxicology studies, and serial blood gas data may be needed for a full picture.
For methylmalonic acidemia, the key point is that a high anion gap can be a sign of organic acid buildup, but not every elevated gap is caused by an organic acidemia. A structured assessment helps separate the biochemical pattern from the underlying cause. The calculator can identify the abnormality, but interpretation requires the full context of illness severity, nutrition status, renal function, and timing of collection.
Adjusting the Anion Gap and Clinical Setting
Uncorrected anion gap results can be misleading unless the broader acid-base disorder is evaluated. This is where albumin correction becomes essential. Since albumin is negatively charged, low levels decrease the baseline gap. A patient with substantial acidosis and hypoalbuminemia may therefore show a deceptively normal result unless the value is corrected.
Accounting for albumin enhances the utility of the anion gap calculator and makes the number more indicative of true acid burden. This is particularly important in critically ill patients, where low albumin is common and physiologic compensation may somewhat offset pH changes. A normal pH does not rule out acidosis if compensation is present.
For this reason blood gas testing is such an important companion test. A blood gas can verify pH, bicarbonate status, and compensatory respiratory changes. When paired with the corrected gap, it helps define whether the patient has primary metabolic acidosis, a superimposed respiratory process, or a combined acid-base disorder.
In clinical practice, clinicians should avoid interpreting the anion gap in isolation. The best approach integrates albumin, serum chemistry, blood gas analysis, symptoms, and time course. That complete review can separate an acute metabolic emergency from a chronic compensated state and can prevent under-recognition of severe disease.
Laboratory Findings in methylmalonic acidemia
A number of laboratory findings point to the diagnosis of methylmalonic acidemia. The most immediate is elevated methylmalonic acid, which indicates the underlying enzymatic block and demonstrates the presence of excess abnormal metabolites. This finding often correlates with a high anion gap state, but the magnitude of the gap can fluctuate depending on hydration, nutrition, and concurrent illness.
Cobalamin deficiency is a key related consideration because vitamin B12 metabolism is tightly linked to methylmalonic acid handling. In some patients, low B12 or impaired cobalamin processing plays a role in the biochemical picture. This is why methylmalonic acidemia and cobalamin-related disorders are often assessed together during a laboratory assessment.
Ammonia may also be elevated, especially during decompensation. Hyperammonemia can worsen neurologic symptoms and increase the concern for a metabolic crisis. Likewise, ketones may be present as the body shifts toward alternative fuels during stress or inadequate intake. These findings increase the suspicion of a serious inherited metabolic disorder.
When all these results are viewed together, the pattern is easier to recognize: elevated methylmalonic acid, possible cobalamin involvement, increased ammonia, and ketosis can accompany a high anion gap. The result is a biochemical pattern that strongly suggests further metabolic testing and urgent clinical correlation.
Common Possible Diagnoses
A number of disorders can mimic methylmalonic acidemia on initial evaluation. Propionic acidemia is one of the major because it is another organic acidemia with shared features, including metabolic acidosis, ketosis, and an increased gap. Telling apart these conditions usually requires focused biochemical and genetic evaluation rather than a single electrolyte panel.
Renal failure is another common cause of high anion gap acidosis. When kidney function declines, acids accumulate and unmeasured anions rise. In this setting, the anion gap may be elevated for reasons unrelated to an inborn error of metabolism, so renal markers and the overall clinical context are important.
Sepsis can also create a high-gap picture through lactic acidosis, poor perfusion, and multiorgan stress. Because sepsis can present with nonspecific symptoms and rapid decompensation, it can overlap clinically with metabolic disease. A clinician evaluating a patient with suspected methylmalonic acidemia should always consider infection as a trigger or an other explanation.
More broadly, the category of inborn errors of metabolism includes many conditions that present with acidosis, hyperammonemia, and neurologic changes. Anion Gap Calculator is useful for interpreting the acid-base pattern, but the differential diagnosis must remain wide until confirmatory studies narrow it down.
When the Anion Gap May Be Unreliable
Although the anion gap is helpful, it is not infallible. A patient with serious disease may still show a normal anion gap if the disturbance is masked by low albumin, early sampling, or simultaneous alkalinizing processes. In methylmalonic acidemia, this can happen if the patient has had fluid therapy, is incompletely treated, or is in a less severe phase of illness.
Mixed acid-base disorders are some of the key pitfalls. For example, a patient may have metabolic acidosis from organic acid accumulation and a concurrent respiratory alkalosis from hyperventilation. The pH can look near normal even though the underlying disturbance is significant. Blood gas interpretation is therefore crucial.
Hypoalbuminemia can lower the apparent gap enough to hide the severity of the disorder. This is why albumin correction is so important. If albumin is low and the corrected result becomes clearly abnormal, the concern for an organic acid process rises significantly.
Laboratory variation can also affect the result. Small differences in analyzer method, specimen handling, or repeat sampling can change the number somewhat. For that reason, a single borderline value should not be overinterpreted. Trend data, the clinical picture, and repeat testing are often more useful than one isolated result.
In short, the anion gap is a useful clue, not a diagnosis. The best interpretation comes from integrating the calculator output with blood gas analysis, albumin status, symptoms, and the broader biochemical pattern.
Frequently Asked Questions
How does an anion gap calculator help in methylmalonic acidemia?
An anion gap calculator helps by quickly identifying whether the patient has an elevated gap consistent with metabolic acidosis. In methylmalonic acidemia, this supports recognition of organic acid buildup and helps guide further testing. It is a useful screening tool, but it does not take the place of clinical evaluation or confirm the diagnosis on its own.
Which anion gap formula should be used for serum electrolytes?
The most widely used anion gap formula uses serum sodium less the total of serum chloride and serum bicarbonate. Some formulas include potassium, but many clinical calculators omit it. The preferred choice is the one that matches the laboratory and the clinician’s review process for serum electrolytes.
Does methylmalonic acidemia cause a normal anion gap?
Yes. Methylmalonic acidemia can at times occur with a normal anion gap, especially if there is hypoalbuminemia, early disease, treatment effects, or a mixed acid-base disorder. For this reason the calculator should be paired with albumin correction and blood gas analysis.
How come is albumin correction important when interpreting the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap look falsely normal. Albumin correction helps estimate the true corrected anion gap and improves acid-base interpretation. This matters especially in illness, where hypoalbuminemia can mask a significant high anion gap metabolic acidosis.
What additional conditions can look like methylmalonic acidemia on an anion gap test?
Common mimics include propionic acidemia, renal failure, sepsis, lactic acidosis, ketosis, and other inborn errors of metabolism. Toxin exposure can also produce a similar pattern. The anion gap is helpful for recognizing the biochemical pattern, but the final diagnosis depends on the whole laboratory and clinical picture.