An Anion Gap Calculator assists practitioners, trainees, and curious readers compute and interpret the anion gap from common serum electrolytes. The value is a practical screening tool for acid-base imbalances, especially when evaluating metabolic acidosis. Because albumin is a primary contributor to unmeasured negative charge in the blood, the raw anion gap can be deceptive in hypoalbuminemia. That is why an albumin-corrected anion gap is often better for clinical use than the measured value alone.
This article explains what the anion gap measures, how the anion gap formula is applied, how to make the albumin adjustment, and how to use the result for clinical interpretation. The goal is to move from a measured number to a clearer picture of acid-base status and the underlying cause of an abnormal result.
What exactly the anion gap measures
The anion gap is a computed difference obtained from serum electrolytes. It measures the main measured positive ions and anions in the blood, usually sodium, chloride, and bicarbonate. The calculation captures the gap between measured positively charged particles and negatively charged particles that are measured, while also indirectly suggesting unmeasured ions.
In plain language, the anion gap may show whether there are excess acids or other unmeasured substances in the bloodstream. That makes the test especially useful when evaluating acid-base disorders and determining whether a patient has metabolic acidosis. A normal result does not always rule out pathology, but an abnormal result often indicates a specific diagnostic path.
The standard calculation is based on routine chemistry values from an electrolyte panel. Because sodium is typically the main measured cation and chloride plus bicarbonate are the main measured anions, the difference between them provides a clinically meaningful clue about the balance of electrolytes and the presence of unmeasured anions.
Commonly, the anion gap is used as a diagnostic aid rather than a stand-alone diagnosis. The number must be interpreted together with symptoms, blood gas data, and the broader laboratory picture.
Why albumin changes the anion gap
Albumin acts as the key unmeasured anion in plasma. Its protein charge has a strong effect on the normal anion gap. When albumin is low, reduced numbers of negatively charged proteins are present in the blood, so the measured anion gap can appear lower than expected even when acid-base pathology is present.
That matters because hypoalbuminemia can mask https://anion-gap-widget808.cloudhinter.com/posts/anion-gap-calculator-for-children-how-to-read-results a true increase in unmeasured acids. A patient may have substantial metabolic derangement, but the measured gap looks only a little increased or even normal. In that setting, albumin correction improves clinical significance and makes the result more accurate for clinical interpretation.
Albumin is also important for maintaining acid-base balance. Since it carries negative charge, changes in albumin concentration change the difference between measured cations and anions. If albumin drops, the expected range of the anion gap shifts downward. For this reason a raw value should not be considered in isolation when serum albumin is abnormal.
In practical terms, low albumin can hide a higher-than-expected acid burden. Correcting the anion gap helps clinicians identify an abnormal result that might otherwise be dismissed as normal.
How to compute the albumin-corrected anion gap
The anion gap formula commonly used is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Once the value is calculated, the corrected anion gap can be estimated by adjusting for albumin. A common albumin adjustment adds about 2.5 mEq/L to the measured anion gap for every 1 g/dL reduction in albumin below 4.0 g/dL. In other words, lower albumin means the corrected value rises to better show the true acid burden.
A practical correction can be expressed as follows:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - albumin in g/dL)
This adjustment gives a more realistic expected range for patients with low albumin. It is not a perfect law, but it is a well-accepted clinical estimate that improves interpretation. The goal is to match the measured value with a corrected value rather than rely on the raw number alone.
The concept of normal range can change by laboratory because of differences in analyzer methods and reference intervals. Even so, albumin correction helps guide evaluation when the albumin level is clearly below normal. That is especially useful in hospitalized patients, where the raw anion gap may underestimate the true degree of metabolic disturbance.
Remember that the albumin-corrected anion gap is a calculated estimate, not a direct measurement. It should support, not replace, the overall evaluation.
How to apply an Anion Gap Calculator
An Anion Gap Calculator is a useful way to calculate both the raw and adjusted gap from routine lab values. Most tools request sodium, chloride, bicarbonate, and albumin. Some tools also allow the user to add the local reference range so the result can be judged against the lab’s own standards.
A basic step-by-step calculation usually uses this sequence:
- Input the sodium value from the serum labs. Enter the chloride value. Add the bicarbonate value. Enter the albumin value if correction is needed. Calculate the measured anion gap. Make the albumin adjustment to find the corrected anion gap. Compare the result with the lab’s reference range and the clinical picture.
For example, if sodium is 140, chloride is 104, bicarbonate is 20, and albumin is 2.0 g/dL, the measured anion gap is 16. The albumin-corrected anion gap is greater than the measured value because hypoalbuminemia lowers the uncorrected result. In that case, the calculator helps reveal a greater acid-base abnormality than the raw number suggests.
This is why calculator use is more than a convenience. It serves as a screening tool that helps clinicians quickly identify whether the measured value matches the expected range. If not, the discrepancy can direct further evaluation.
The best use of the calculator is stepwise: calculate the gap, correct it when albumin is low, and then review the result within the full acid-base context. If needed, confirm the findings with blood gas analysis, lactate, ketones, renal studies, or toxicology testing.
Understanding high, normal, and low anion gap results
A elevated anion gap suggests an increase of undetected anions, often due to acids. This result is classically associated with high anion gap metabolic acidosis. When the gap is elevated, the clinician should consider whether the result reflects lactate accumulation, ketone accumulation, kidney dysfunction, or toxic ingestion.
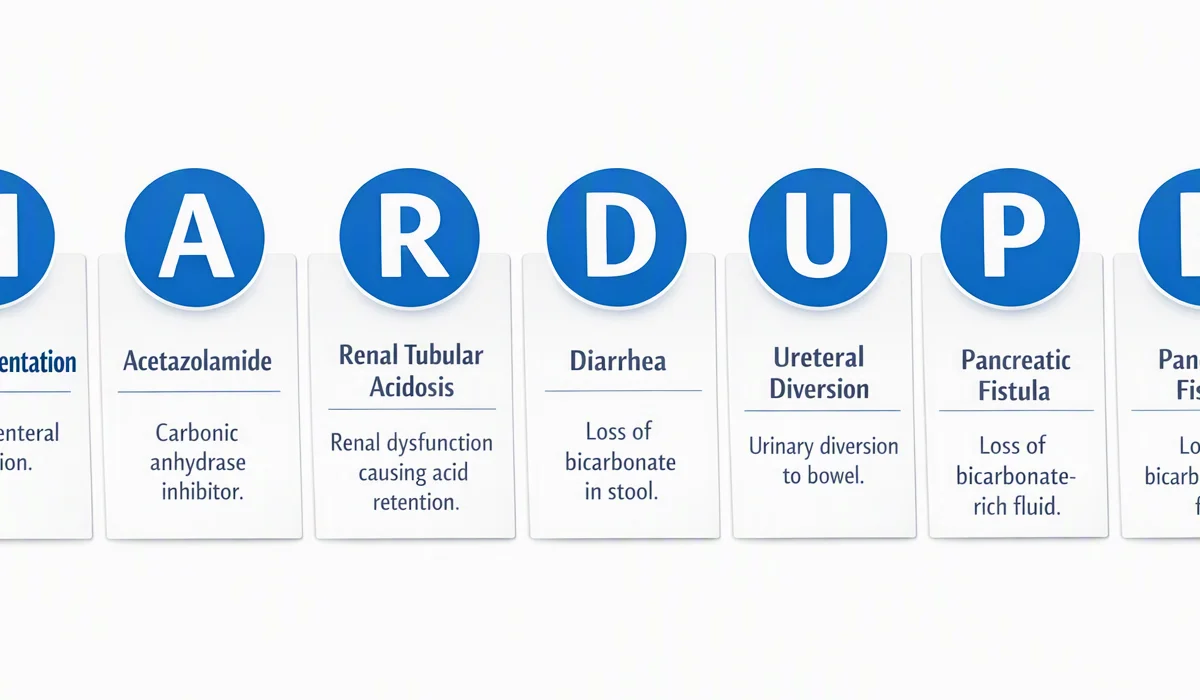
A normal anion gap does not always mean there is no metabolic issue. It can occur in normal anion gap metabolic acidosis, where bicarbonate is lost and chloride rises proportionally, keeping the difference comparatively unchanged. This pattern is often called hyperchloremic acidosis.
A low anion gap is rarer but can be important. It may result from reduced albumin, lab artifact, or unusual increases in positively charged proteins or other substances. Because low values are often overlooked, they deserve thorough evaluation, especially if the number does not fit the rest of the clinical picture.
When evaluating metabolic acidosis, the anion gap is one piece of the puzzle. It helps classify acid-base disorders into broad categories and points toward an underlying cause. However, the measured value alone cannot establish the diagnosis without clinical interpretation and related laboratory data.
Frequent causes of abnormal anion gap values
Many conditions often produce a high anion gap metabolic acidosis. Some of the key causes are lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each adds to unmeasured acids or acid precursors in the bloodstream.
Lactic acidosis occurs when lactate accumulates, often in settings of tissue hypoperfusion, severe infection, shock, seizures, or hypoxia. Since lactate is an unmeasured anion, the anion gap rises as bicarbonate is consumed buffering the acid load.
Ketoacidosis occurs when ketone bodies build up, as seen in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. Such ketones also increase the gap and lower bicarbonate.
Renal failure can increase the gap because impaired kidney function reduces acid excretion and allows sulfate, phosphate, and other acids to accumulate. This is a well-known and major cause of persistent metabolic acidosis.
Toxic alcohols such as methanol and ethylene glycol can also produce a high gap. They are dangerous because they may initially present with nonspecific symptoms, while acid-base testing reveals the metabolic disturbance. Sometimes, the anion gap may help trigger urgent evaluation even before the toxic substance is confirmed.
Additional causes of abnormal results include changes in serum proteins, shifts in measured electrolytes, and laboratory artifacts. That is why the anion gap should be viewed as a clue, not a final answer.
When albumin correction matters most
Albumin adjustment is most valuable when the patient has conditions associated with reduced albumin levels. This covers critical illness, malnutrition, cirrhosis, and nephrotic syndrome. In these situations, the raw anion gap may miss the true acid load.
In critical illness, inflammation, fluid shifts, and poor nutrition often reduce albumin. A patient may look like they have a modest anion gap when the corrected value would reveal a more significant abnormality. That makes adjustment particularly important for early detection of acid-base disorders.
Malnutrition can lower albumin over time, changing the interpretation of routine serum labs. The same is true in cirrhosis, where reduced hepatic synthetic function contributes to hypoalbuminemia. In nephrotic syndrome, albumin is lost through the kidneys, again lowering the measured baseline gap.
In these populations, the albumin-corrected anion gap is not optional trivia; it is a more accurate estimate of the actual acid-base status. That can change whether a result is interpreted as slightly abnormal or clearly abnormal.

Limitations of the anion gap calculation
Although the anion gap is valuable, it has important limitations. One issue is lab variation. Different instruments and assay methods can generate slightly different values, which affects the reference range. This means a result that is normal in one lab may seem borderline in another.
Measurement error is another concern. Small inaccuracies in sodium, chloride, or bicarbonate can change the calculated gap, since the formula depends on subtracting similar numbers. Even a modest analytic difference can shift the result enough to change interpretation.
Albumin correction itself is an estimate, not a direct test of acid burden. The correction factor is helpful, but it does not replace a full evaluation. Other factors, such as unusual proteins, unmeasured cations, or severe electrolyte disturbances, can complicate interpretation.
Most of all, the anion gap must always be interpreted in context. Signs and symptoms, vitals, patient history, drugs, kidney health, lactic acid, ketone levels, and blood gas results all count. A derived value without context can lead to error, especially if the measured result is mildly abnormal.
Because of this, the anion gap is best used as part of a more comprehensive review. It can indicate a likely cause, but the final clinical interpretation relies on the overall situation.

FAQs
What is anion gap calculator with albumin adjustment?
An anion gap estimator with adjustment for albumin is a calculator that derives the anion-gap result from sodium, chloride, and bicarbonate, then refines the result for low albumin. It assists improve clinical interpretation by giving a more accurate estimate of acid-base status when hypoalbuminemia is present.
Why does low albumin lower the anion gap?
Low albumin lowers the anion gap because albumin bears significant protein charge and serves as an unmeasured anion. When albumin falls, the measured gap decreases even if there is still an underlying acid-base disorder. For this reason albumin correction is important for precise assessment.
How do you determine the corrected anion gap?
Initially calculate the usual anion gap formula: sodium minus chloride plus bicarbonate. Next apply an albumin correction, typically adding approximately 2.5 mEq/L for every 1 g/dL albumin under 4.0 g/dL. This value is the albumin-corrected anion gap.
What is a normal anion gap after albumin correction?
The normal range depends on the laboratory’s expected range, since different assays yield slightly different values. Following albumin correction, the result should be compared with the lab’s normal range and the overall clinical picture. A “normal” value still needs interpretation if symptoms or other labs suggest metabolic disease.
When should anion gap results be interpreted with clinical context?
Anion gap results should routinely be interpreted with clinical context, especially when the patient has acidosis, reduced albumin, kidney dysfunction, shock, or possible toxin exposure. The number is a helpful screening tool, but diagnosis requires verification using the complete assessment, including serum labs, symptoms, and other tests.