An Anion Gap Calculator assists clinicians, students, and informed readers calculate and understand the anion gap from standard serum electrolytes. The value is a helpful screening tool for acid-base disorders, especially when evaluating metabolic acidosis. Because albumin is a primary contributor to unmeasured negative charge in the blood, the raw anion gap can be deceptive in hypoalbuminemia. That is why an albumin-corrected anion gap is often more clinically useful than the measured value alone.
This article outlines what the anion gap measures, how the anion gap formula functions, how to make the albumin adjustment, and how to use the result for clinical interpretation. The goal is to move from a measured number to a better understanding of acid-base status and the underlying cause of an abnormal result.
What exactly the anion gap shows
The anion gap is a derived difference derived from serum electrolytes. It evaluates the main observed positive ions and negative ions in the blood, most commonly sodium, chloride, and bicarbonate. The calculation shows the balance between positively charged particles that are measured and measured negatively charged particles, while also indirectly reflecting unmeasured ions.
In plain language, the anion gap may show whether there are extra acids or other unmeasured substances in the bloodstream. That makes the test especially useful when evaluating acid-base disorders and determining whether a patient has metabolic acidosis. A normal result does not always rule out pathology, but an abnormal result often suggests a specific diagnostic path.
The standard calculation is based on common chemistry values from an electrolyte panel. Because sodium is typically the main measured cation and chloride plus bicarbonate are the main measured anions, the difference between them provides a clinically meaningful clue about the balance of electrolytes and the presence of unmeasured anions.
Commonly, the anion gap is used as a diagnostic aid rather than a stand-alone diagnosis. The number must be interpreted alongside symptoms, blood gas data, and the broader laboratory picture.
How albumin affects the anion gap
Albumin serves as the primary unmeasured anion in plasma. Its protein charge plays a major role in the normal anion gap. When albumin is low, less negatively charged proteins are present in the blood, so the measured anion gap can appear lower than expected even when acid-base pathology is present.
That matters because hypoalbuminemia can conceal a true increase in unmeasured acids. A patient may have substantial metabolic derangement, but the measured gap looks only a little increased or even normal. In that setting, albumin correction improves clinical significance and makes the result more precise for clinical interpretation.
Albumin is also critical for maintaining acid-base balance. Since it carries negative charge, changes in albumin concentration alter the difference between measured cations and anions. If albumin drops, the expected range of the anion gap shifts downward. For this reason a raw value should not be considered in isolation when serum albumin is abnormal.
In practical terms, low albumin can obscure a higher-than-expected acid burden. Correcting the anion gap helps clinicians identify an abnormal result that might otherwise be dismissed as normal.
How to work out the albumin-corrected anion gap
The anion gap formula most often used is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Once the value is determined, the corrected anion gap can be worked out by accounting for albumin. A common albumin adjustment adds about 2.5 mEq/L to the measured anion gap for every 1 g/dL drop in albumin below 4.0 g/dL. In other words, lower albumin means the corrected value goes up to better show the true acid burden.
A practical correction is written as follows:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 - albumin in g/dL)
This adjustment gives a more realistic expected range for patients with low albumin. It is not a perfect law, but it is a commonly used clinical estimate that enhances interpretation. The goal is to compare the measured value with a corrected value rather than rely on the raw number alone.
The concept of normal range can differ by laboratory because of differences in analyzer methods and reference intervals. Even so, albumin correction helps guide evaluation when the albumin level is clearly below normal. That is especially useful in hospitalized patients, where the raw anion gap may downplay the true degree of metabolic disturbance.
Remember that the albumin-corrected anion gap is a calculated estimate, not a direct measurement. It should supplement, not replace, the overall evaluation.
How to apply an Anion Gap Calculator
An Anion Gap Calculator is a convenient way to calculate both the measured and adjusted gap from common lab values. Most calculators request sodium, chloride, bicarbonate, and albumin. Certain calculators also allow the user to input the local reference range so the result can be evaluated against the lab’s own standards.
A basic step-by-step calculation usually follows this sequence:
- Input the sodium value from the serum labs. Add the chloride value. Add the bicarbonate value. Enter the albumin value if correction is needed. Calculate the measured anion gap. Apply the albumin adjustment to find the corrected anion gap. Compare the result with the lab’s reference range and the clinical picture.
For example, if sodium is 140, chloride is 104, bicarbonate is 20, and albumin is 2.0 g/dL, the measured anion gap is 16. The albumin-corrected anion gap is higher than the measured value because hypoalbuminemia lowers the uncorrected result. In that case, the calculator helps reveal a more significant acid-base abnormality than the raw number suggests.
That is why calculator use is more than a convenience. It acts as a screening tool that helps clinicians quickly identify whether the measured value matches the expected range. If not, the discrepancy can direct further evaluation.
The best use of the calculator is stepwise: work out the gap, correct it when albumin is low, and then assess the result within the full acid-base context. If needed, confirm the findings with blood gas analysis, lactate, ketones, renal studies, or toxicology testing.
Interpreting high, normal, and low anion gap results
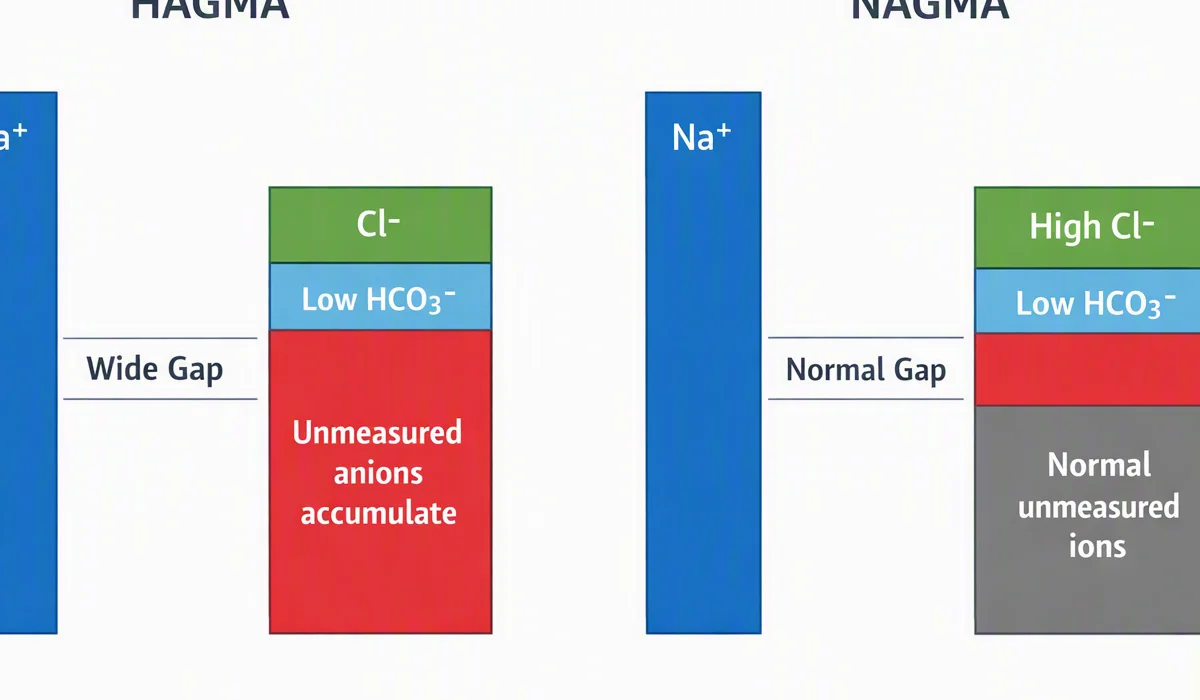
A high anion gap indicates an accumulation of unaccounted for anions, often due to acids. This result is classically associated with high anion gap metabolic acidosis. When the gap is elevated, the clinician should evaluate whether the result reflects elevated lactic acid, ketone build-up, kidney dysfunction, or toxin exposure.
A normal anion gap does not always mean there is no metabolic issue. It can occur in normal anion gap metabolic acidosis, where bicarbonate is lost and chloride rises proportionally, keeping the difference comparatively unchanged. This pattern is often called hyperchloremic acidosis.
A low anion gap is uncommon but can be important. It may result from low albumin, lab artifact, or unusual increases in positively charged proteins or other substances. Because low values are often overlooked, they deserve thorough evaluation, especially if the number does not fit the rest of the clinical picture.
When evaluating metabolic acidosis, the anion gap is one piece of the puzzle. It helps sort acid-base disorders into broad categories and points toward an underlying cause. However, the measured value alone cannot establish the diagnosis without clinical interpretation and related laboratory data.
Common causes of atypical anion gap values
Several conditions commonly produce a elevated anion gap metabolic acidosis. Among the most important are lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one raises unmeasured acids or acid precursors in the bloodstream.
Lactic acidosis occurs when lactate accumulates, commonly in settings of tissue hypoperfusion, severe infection, shock, seizures, or hypoxia. As lactate is an unmeasured anion, the anion gap rises as bicarbonate is consumed counteracting the acid load.
Ketoacidosis arises when ketone bodies build up, as seen in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation states. The ketones also increase the gap and lower bicarbonate.
Renal failure can increase the gap because impaired kidney function reduces acid excretion and allows sulfate, phosphate, and other acids to accumulate. That is a frequent and important cause of persistent metabolic acidosis.
Toxic alcohols such as methanol and ethylene glycol can also produce a high gap. They are especially hazardous because they may initially present with nonspecific symptoms, while acid-base testing reveals the metabolic disturbance. Sometimes, the anion gap may help trigger urgent evaluation even before the toxic substance is confirmed.
Additional causes of abnormal results include changes in serum proteins, shifts in measured electrolytes, and laboratory artifacts. This is why the anion gap should be viewed as a clue, not a final answer.
When albumin correction matters most
Albumin correction is most valuable when the patient has conditions associated with low serum albumin. This includes critical illness, malnutrition, cirrhosis, and nephrotic syndrome. In these settings, the raw anion gap may underestimate the true acid load.
In critical illness, inflammatory states, fluid shifts, and poor nutrition often decrease albumin. A patient may seem to have a modest anion gap when the corrected value would show a more significant abnormality. That makes adjustment particularly important for timely recognition of acid-base disorders.
Malnutrition can lower albumin over time, changing the interpretation of routine serum labs. The same is true in cirrhosis, where reduced hepatic synthetic function contributes to hypoalbuminemia. In nephrotic syndrome, albumin is removed through the kidneys, again lowering the measured baseline gap.
In these populations, the albumin-corrected anion gap is not mere extra detail; it is a truer reflection of the actual acid-base status. That can change whether a result is interpreted as marginal or clearly abnormal.
Limitations of the anion gap calculation
Although the anion gap is helpful, it has significant limitations. One issue is lab variation. Different instruments and assay methods can yield slightly different values, which affects the reference range. This means a result that is normal in one lab may appear borderline in another.
Measurement error is another concern. Small inaccuracies in sodium, chloride, or bicarbonate can alter the calculated gap, since the formula depends on subtracting similar numbers. Even a modest analytic difference can shift the result enough to influence interpretation.
Albumin correction itself is an approximation, not a direct test of acid burden. The correction factor is practical, but it does not replace a full evaluation. Other factors, such as unusual proteins, unmeasured cations, or severe electrolyte disturbances, can cloud interpretation.
Most of all, the anion gap must always be assessed in clinical context. Symptoms, vitals, medical history, medications, kidney health, lactate, ketone levels, and ABG results all are important. A calculated value without context can mislead, especially if the measured result is only slightly abnormal.
For that reason, the anion gap works best as part of a wider review. It can suggest a likely diagnosis, but the final clinical interpretation is based on the whole picture.
FAQs
What is anion gap calculator with albumin adjustment?
An anion gap tool with albumin adjustment is a tool that calculates the clinical significance of low anion gap anion gap value from sodium, chloride, and bicarbonate, then refines the result for low albumin. It helps improve clinical interpretation by showing a more accurate calculation of acid-base status when hypoalbuminemia is present.
Why does low albumin lower the anion gap?
Reduced albumin decreases the anion gap because albumin bears significant protein charge and serves as an unaccounted anion. When albumin decreases, the measured gap decreases even if there is still an underlying acid-base disorder. This is why albumin correction is crucial for reliable assessment.
How do you calculate the corrected anion gap?
First compute the usual anion gap formula: Na minus chloride plus bicarbonate. Next make an albumin adjustment, commonly increasing by 2.5 mEq/L for each 1 g/dL albumin below 4.0 g/dL. The outcome is the albumin-corrected anion gap.
What is a normal anion gap after albumin correction?
The normal range depends on the laboratory’s reference range, because different assays yield slightly different values. Following albumin correction, the result should be compared with the lab’s reference range and the overall medical picture. A “normal” value still needs context if symptoms or other labs suggest metabolic disease.
When should anion gap results be interpreted with clinical context?
Anion gap results should always be interpreted with clinical context, especially when the patient has metabolic acidosis, hypoalbuminemia, renal impairment, shock, or possible toxic exposure. The number is a practical preliminary test, but diagnosis requires verification using the full evaluation, including serum labs, patient symptoms, and other tests.