What Is the Anion Gap?
The anion gap is a calculated value from serum electrolytes that aids clinicians in assessing acid-base balance. It contrasts measured sodium with the measured anions chloride and bicarbonate to estimate the amount of unmeasured anions in the blood. In routine blood chemistry, this gives the anion gap a helpful marker in a metabolic acidosis workup and a practical part of patient assessment.
The basic idea is simple: the body keeps positive and negative charges in balance. When the gap is greater than expected, it can indicate excess acids or other unmeasured substances. That is why the anion gap is often relied on as a diagnostic tool in the evaluation of metabolic acidosis and other acid-base disorder patterns.
The most common anion gap equation is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation relies on values from an electrolyte panel and yields a lab result that must always be interpreted in context. Because different laboratories may use slightly different measurement methods and normal values, the expected reference range can vary.
How come Correct the Anion Gap for Albumin?
Albumin is the primary unmeasured anion in plasma, so it has a significant effect on the anion gap. When a patient has hypoalbuminemia, the raw anion gap can look falsely normal or only somewhat elevated even when important acids are present. This is why the anion gap is often corrected for albumin.
Low albumin lowers the baseline gap because there are less negatively charged proteins contributing to the measured balance. That can hide a meaningful metabolic acid load and decrease the sensitivity of the test for detecting metabolic acidosis. In other words, a patient with low albumin may have a “normal” gap on paper but still have an underlying high anion gap process.
Correcting the result enhances anion gap interpretation and supports better clinical significance. It helps distinguish true normal anion gap states from masked high-gap states in the setting of low albumin. This is especially important during critically ill patient assessment, where changes in albumin are common.
Modified Anion Gap Method and Calculation Steps
The corrected anion gap adjusts the observed gap for the patient’s serum albumin level. The exact albumin correction factor may vary by guideline, but a widely used approach is to add 2.5 mEq/L to the measured anion gap for every 1 g/dL albumin below 4.0 g/dL.
A commonly used formula is:
Adjusted anion gap = Measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
Example 1:
- Na = 140 Cl = 104 Bicarbonate = 20 Serum albumin = 2.0 g/dL
Begin with calculating the anion gap:
140 - (104 + 20) = 16
Then use the albumin correction:
2.5 × (4.0 - 2.0) = 5
Albumin-corrected anion gap = 16 + 5 = 21
That corrected value suggests a greater burden of unmeasured anions than the unadjusted result might imply.
Example 2:
- Sodium = 138 Cl = 109 HCO3 = 24 Serum albumin = 1.8 g/dL
138 - (109 + 24) = 5
2.5 × (4.0 - 1.8) = 5.5
Adjusted anion gap = 10.5
Even though the uncorrected value is near normal, the albumin-adjusted result falls within or around a standard reference range depending on the lab. This is why albumin correction matters so much in routine clinical testing.
To calculate anion gap accurately, follow these steps:
- Obtain sodium, chloride, and bicarbonate from the electrolyte panel. Determine the measured anion gap using the anion gap equation. Review the serum albumin level. Use the albumin correction factor if albumin is low. Evaluate the corrected result with the lab’s reference range.
Keep in mind that some institutions use slightly different formulas or cutoffs, so the final interpretation should always account for the local reference range and method used by the medical calculator or laboratory system.
How to Use an Anion Gap Calculator
An Anion Gap Calculator is a healthcare calculator that assists clinicians swiftly compute anion gap and perform albumin-adjusted interpretation. It is especially useful when evaluating a blood chemistry panel during a metabolic acid workup, because it lowers arithmetic errors and shortens decision-making.
To use a calculation tool correctly, input the relevant lab values exactly as reported:
- Sodium Chloride Bicarbonate Albumin
Some tools may request the serum bicarbonate directly, while others use total CO2 as a proxy depending on the lab format. Always make sure the values are taken from the same electrolyte panel and match the same sample to avoid inconsistency in the lab result.
When using an Anion Gap Calculator, the output usually shows:
- Measured anion gap Albumin-adjusted or corrected anion gap Reference range comparison
This aids clinical interpretation, especially when hypoalbuminemia is present. A calculator can also make it more convenient to compare repeated results over time and track trends in acid-base disorder management.
That said, the calculation tool does not take the place of judgment. The calculator provides a number, but the clinician must decide whether the result fits the patient’s overall picture, including symptoms, medications, and other laboratory findings.
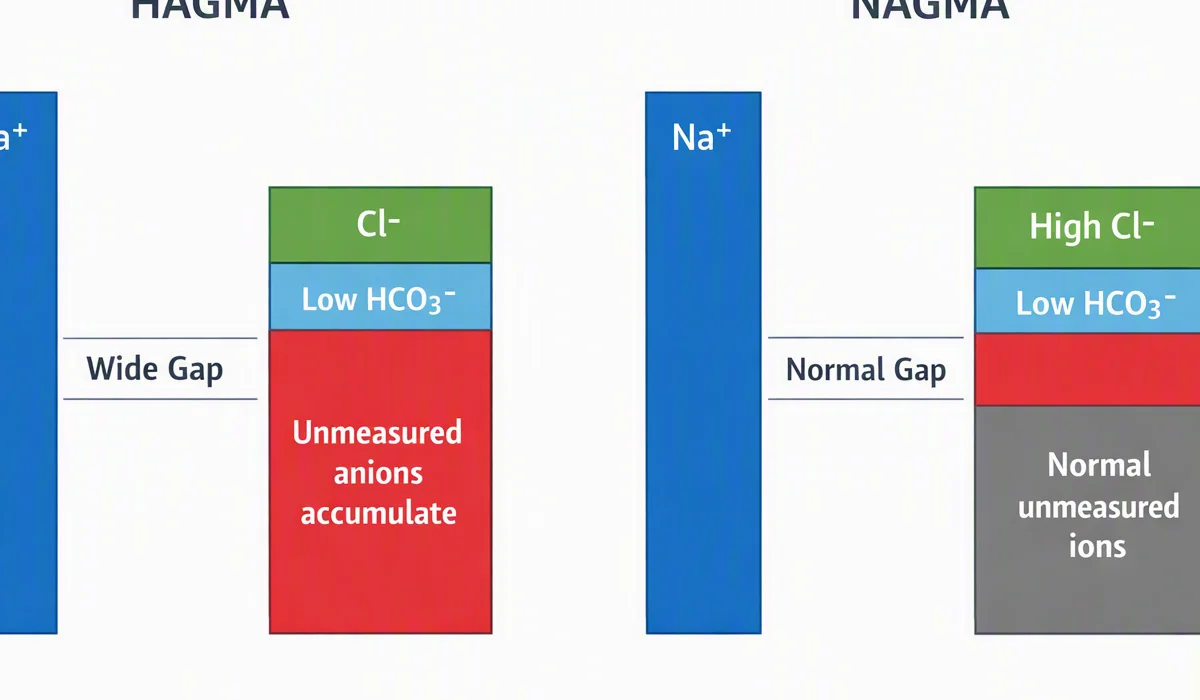
How to Analyze a High or Normal Corrected Anion Gap
A elevated anion gap metabolic acidosis suggests that unmeasured acids are accumulating in the circulation. If the corrected value is above normal, the next step is to determine the cause of the acid load. Common causes include lactic acidosis, ketoacidosis, renal dysfunction, and toxin exposure.
If the corrected anion gap is not elevated, the patient may have a normal anion gap pattern, often linked to bicarbonate loss or chloride gain rather than additional unmeasured acids. This is frequently seen in some forms of diarrhea, renal tubular disorders, or saline-related acid-base changes. Even then, the overall clinical context remains essential.
Here is a practical way to think about the result:
- High corrected gap: consider high anion gap metabolic acidosis and investigate unmeasured anions. Normal corrected gap: think about normal-gap processes and check chloride and bicarbonate shifts. Borderline result: examine albumin, repeat testing if needed, and assess for mixed disorders.
In clinical practice, lactic acidosis may occur with shock, hypoperfusion, or severe illness, while ketoacidosis is often linked to diabetes, starvation, or alcohol use. Both can elevate acid production and raise the corrected gap. hypoalbuminemia and low anion gap These patterns are a major part of anion gap interpretation because they inform urgent evaluation and treatment.
Typical Causes of an Elevated Corrected Anion Gap
An altered corrected anion gap can suggest several significant conditions. The differential diagnosis depends on whether the corrected value is increased, unchanged, or unexpectedly reduced. In the context of a metabolic acidosis evaluation, the most notable causes include renal failure, uremia, toxic alcohols, and salicylates.
Renal failure can raise the gap because the kidneys cannot excrete acids normally, allowing metabolic acids to accumulate. As kidney function declines, retained acids contribute to uremic patterns and a widening gap.
Uremia is a typical cause of high-gap acidosis due to retained organic acids and other unmeasured anions. In advanced kidney disease, this may be a prominent driver of abnormal blood chemistry values.
Toxic alcohols such as methanol or ethylene glycol can produce a dangerous high-gap state by generating acidic metabolites. When suspected, the clinical picture often includes neurologic changes, visual symptoms, or kidney injury, but the lab pattern may be the earliest clue.
Salicylates can create mixed acid-base patterns and may elevate the anion gap through increased organic acids. The resulting picture can be complicated, so correlation with history and additional testing is essential.
Other causes of elevated corrected values may include:
- Lactic acidosis from poor perfusion or severe illness Ketoacidosis from diabetes, fasting, or alcohol-related states Toxin-induced metabolic acidosis Severe kidney dysfunction with retained acids
Understanding these patterns improves diagnostic interpretation and supports appropriate next steps when the lab result is abnormal.
Limitations, Errors, and Medical Considerations
The adjusted anion gap is valuable, but it is not perfect. One major issue is lab error. Small inaccuracies in sodium, chloride, or bicarbonate can noticeably change the final result, especially when the gap is only mildly abnormal. Rechecking values may be appropriate when the pattern does not align with the clinical picture.
Another key concept is the delta gap, which compares the rise in the anion gap with the fall in bicarbonate. This can help detect mixed acid-base disorders. As an example, a high gap with a lower-than-expected bicarbonate drop may suggest an additional metabolic alkalosis, while the reverse can suggest a coexisting non-gap process.
Mixed acid-base disorders are often seen in sick patients, and the corrected anion gap should be used as part of a broader clinical interpretation rather than as a single answer. The result should be considered alongside pH, pCO2, lactate, ketones, kidney function, and medication history.
Additional pitfalls include:
- Working from outdated or mismatched lab values from different collection times Ignoring albumin when it is clearly low Choosing the wrong correction factor for the lab method Failing to notice a normal anion gap process masked by other abnormalities
Good clinical interpretation requires the full picture. The corrected anion gap is a tool, not a diagnosis. It should support the broader assessment of the patient, especially when symptoms, blood gas data, and biochemical markers point in opposing directions.
FAQ: Corrected Anion Gap Questions
How do you determine corrected anion gap?
First calculate the anion gap using sodium minus the sum of chloride and bicarbonate. Next correct it for albumin using an albumin correction factor, commonly 2.5 mEq/L for each 1 g/dL that albumin is below 4.0 g/dL. This results in an albumin-adjusted result that anion gap in chronic kidney disease is more accurate in patients with low albumin.
What is the albumin correction factor for anion gap?
A widely used albumin correction factor is 2.5 mEq/L per 1 g/dL decrease in albumin below 4.0 g/dL. Certain references or references may use slightly different values, so the exact method should match the reference range and the calculation tool being used.
Why can low albumin lower the anion gap?
Albumin is a major unmeasured anion in blood. With low albumin, fewer negative charges are present, so the measured anion gap decreases. This can make a high-gap disorder appear less obvious unless the result is corrected for albumin.
What may a high corrected anion gap mean?
A high corrected anion gap usually means there are excess unmeasured acids in the blood. Typical causes include high anion gap metabolic acidosis from lactic acidosis, ketoacidosis, renal failure, uremia, toxic alcohols, or salicylates. This is a clue that further diagnostic interpretation is needed.
When is best to use an anion gap calculator be used?
An Anion Gap Calculator should be used whenever you need to calculate anion gap quickly and accurately, especially if albumin is low or the acid-base disorder is not straightforward. It is especially helpful during metabolic acidosis workup, routine electrolyte panel review, and any situation where corrected interpretation may change the clinical significance of the lab result.