What Is the Anion Gap?
The anion gap is a computed value that helps clinicians assess acid-base issues on standard lab work. It is based on the connection between major electrolytes in the blood, particularly sodium and chloride, along with bicarbonate. Because some charged particles are not directly measured, the anion gap can act as a clue to hidden alterations in the body’s chemistry.
At its simplest, the anion gap reflects the difference between measured positively charged particles and measured negatively charged particles. When that gap is greater than expected, it can suggest that extra acids or other unmeasured anions are present. That makes it a valuable diagnostic clue in cases of metabolic acidosis and other acid-base disorder conditions.
In practice, the anion gap is interpreted alongside the rest of the serum electrolytes, the overall blood chemistry panel, and the patient’s symptoms. A single number is rarely enough on its own. The real value comes from clinical interpretation, especially when kidney dysfunction may be disrupting acid handling, chloride balance, and bicarbonate levels.
How an Anion Gap Calculator Functions
An anion gap calculator relies on values from a serum chemistry panel or another lab report to determine the gap rapidly. In most cases, the calculation uses serum sodium, serum chloride, and bicarbonate. Because these numbers are commonly reported in the same panel, the calculator can enable a clinician or patient calculate anion gap without working out the math manually.
The calculator typically evaluates the measured cations and anions to infer the amount of unmeasured anions. If bicarbonate is low and chloride is not proportionally high, the gap may increase. If chloride rises as bicarbonate falls, the gap may remain normal. That distinction matters because it helps separate different forms of acid-base disturbance.
Some calculators also factor in albumin, which is important because albumin is a major unmeasured anion in blood. If albumin is low, the measured anion gap may look incorrectly normal or only mildly elevated. In those cases, users may need to correct for albumin to reach a more accurate corrected anion gap.
A good calculator is not just a math tool; it supports clinical reasoning. It can reveal an elevated anion gap, a low bicarbonate pattern, or a possible acid-base mismatch. That makes it a practical step in reviewing blood test results from an electrolyte panel or a broader metabolic workup.
Can Kidney Failure Raise the Anion Gap?
Yes, kidney failure can raise the anion gap. This occurs because damaged kidneys do not remove acid and waste products effectively. As those substances accumulate, they can create an acid load that shows up as a higher gap on lab testing.
Both acute kidney injury and chronic kidney disease can produce this pattern. In acute kidney injury, the rise may be abrupt if kidney filtration drops suddenly and acid starts accumulating. In chronic kidney disease, the change may develop more gradually as renal function deteriorates over time.
Uremia is a major reason the anion gap can rise in kidney failure. When kidney filtration worsens, waste product accumulation leads to retention of acids and other compounds that are not directly measured on a standard lab panel. This is one reason kidney failure is closely linked to metabolic acidosis and sometimes to high anion gap metabolic acidosis.
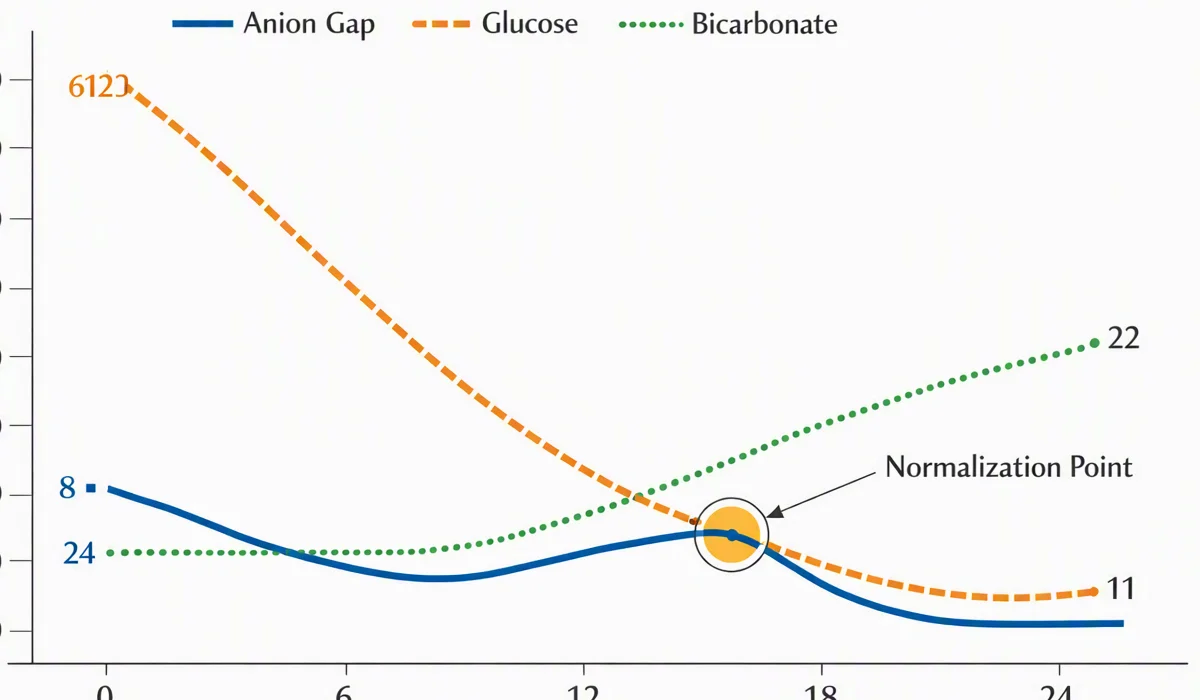
That said, kidney failure does not always produce a high gap. Some patients instead develop normal anion gap metabolic acidosis, especially earlier in the disease process or when specific tubular problems are present. So the calculator result should always be interpreted in context, not as a stand-alone diagnosis.
Reasons Kidney Failure Causes Metabolic Acidosis
Kidneys help maintain acid-base balance by eliminating acid and taking back bicarbonate. As kidney function declines, the body cannot as well to remove acid, which can lead to acid retention and build-up of metabolic acid. As this continues, that imbalance can lower bicarbonate and shift the blood toward acidosis.
Healthy kidneys continuously support renal excretion of fixed acids generated by metabolism. In kidney impairment, that excretion becomes less efficient. The result is a rising acid load, which can affect the electrolyte values and widen the anion gap depending on which acids accumulate.
In plain language, the kidneys are supposed to act like a cleanup system. When that system slows down, acid stays in the body longer. That can disrupt blood pH and produce an disorder of acid-base balance. A lower bicarbonate level on the blood chemistry panel is often one of the initial laboratory findings.
This is why the anion gap can be such a useful clue in kidney function assessment. It does not diagnose the cause by itself, but it helps show whether the body is dealing with hidden acids, whether the problem is primarily acid retention, and whether additional testing is needed.
Increased Anion Gap Versus Typical Anion Gap in Kidney Disease
Kidney disease can show either increased anion gap metabolic acidosis or normal anion gap metabolic acidosis. The variation depends on what is happening to chloride, bicarbonate, and the types of acids involved.
In elevated anion gap metabolic acidosis, unmeasured acids build up. This is more common in advanced kidney failure and uremia, where retained acids increase the gap. In this setting, the calculator may show a clear rise that reflects the presence of extra unmeasured anions.
In standard anion gap metabolic acidosis, bicarbonate falls but chloride rises to replace it. This is often called hyperchloremic acidosis. The anion gap stays within the expected range because the drop in bicarbonate is offset by an increase in chloride. This pattern is frequent in some forms of kidney disease, especially when the tubules cannot handle acid properly.
Renal tubular acidosis is an important example. It involves impaired acid handling in the kidney tubules and often produces a standard gap pattern rather than a high one. That means a normal calculator result does not exclude kidney-related acid-base problems.
Understanding this separation is useful because it changes the differential diagnosis. A high gap points more toward acid anion gap in chronic kidney disease accumulation from uremia or another cause of excess acids, while a normal gap may suggest tubular defects, gastrointestinal bicarbonate loss, or another chloride-driven process.
Additional Sources of an Raised Anion Gap
Renal failure is one cause of an raised result. When checking an anion gap calculator reading, clinicians also evaluate other frequent reasons of high anion gap metabolic acidosis.
Lactic acidosis is a major factor. When tissues do not get enough oxygen, or when metabolism is significantly stressed, lactate rises and adds to the pool of unmeasured acids. This can happen with sepsis, shock, severe illness, or poor tissue perfusion.
Ketoacidosis is a further frequent reason. It can occur in diabetes, starvation, or heavy alcohol use, and it leads to the accumulation of acidic ketone bodies. In those cases, the anion gap may be substantially elevated because the acids accumulate faster than the body can clear them.
Toxin ingestion can also raise the gap. Certain poisons alter metabolism or contribute directly to acid buildup. Because these situations can be critical, an elevated anion gap should always be assessed with the full clinical picture, not just the lab number alone.
These alternatives matter because not every elevated value is due to kidney disease. A person with kidney failure can also have another cause at the same time, such as lactic acidosis. That is why the calculator should be used as a starting point for clinical interpretation, not as a final answer.
How Serum Albumin Affects the Anion Gap
Albumin is a major unmeasured anions in blood, so low levels can change how the anion gap is interpreted. When a patient has hypoalbuminemia, the measured anion gap may look lower than expected even if hidden acids are present.
This is why many clinicians use albumin correction. A corrected value can offer a more realistic estimate of whether the body truly has excess unmeasured anions. Without that adjustment, a person with kidney failure and low albumin might have a misleadingly normal result.
The idea is simple: if albumin is reduced, the measured number may understate the degree of acid-base disturbance. A corrected anion gap helps reduce the risk of missing important osmolar gap anion gap correlation pathology. That is especially relevant in chronic illness, malnutrition, inflammation, and advanced kidney disease, where hypoalbuminemia is more common.
Whenever possible, it is wise to review the albumin level along with the rest of the serum electrolytes. That makes the calculator result more meaningful and improves overall interpretation of the blood chemistry panel.
When It Is Time for Medical Evaluation
If someone has a possible mineral balance or acid and base problem, medical evaluation is essential when symptoms are present or when blood tests show a clear problem. Symptoms of kidney failure can include edema, reduced urine output, fatigue, nausea, confusion, shortness of breath, and poor appetite.
An electrolyte imbalance can also cause weakness, heart rhythm problems, muscle cramps, or worsening mental status. These symptoms can overlap with acidosis and kidney dysfunction, so they should not be overlooked.
Lab follow-up usually includes repeat blood tests, review of the blood chemistry panel, kidney markers, and sometimes arterial or venous blood gas testing. A clinician may also check albumin, lactate, ketones, and other measurements to determine the cause of the acid-base imbalance.
If kidney disease is known or suspected, a nephrologist can help interpret the findings and direct treatment. This is especially important when the anion gap is rising, bicarbonate is low, or symptoms are getting worse. In some cases, urgent care may be needed, particularly if acidosis is severe or accompanied by serious symptoms.
FAQ About Kidney Failure and the Anion Gap
Can kidney failure increase the anion gap?
Yes. Kidney failure can increase the anion gap because reduced renal function leads to acid retention and accumulation of unmeasured anions. This is especially common in uremia and can contribute to high anion gap metabolic acidosis. However, some people with kidney disease instead have normal anion gap metabolic acidosis, so the pattern depends on the stage and cause.
Why does chronic kidney disease cause metabolic acidosis?
Chronic kidney disease can cause metabolic acidosis because damaged kidneys cannot excrete acid as effectively or regenerate bicarbonate as well. That leads to acid-base balance problems and may lower bicarbonate on the blood chemistry panel. In more advanced disease, acid buildup may also raise the anion gap.
Does a typical anion gap exclude kidney issues?
Not necessarily. A standard anion gap does not eliminate kidney disease. Some forms of kidney-related acidosis, including renal tubular acidosis, can appear as normal anion gap metabolic acidosis or hyperchloremic acidosis. Kidney disease can exist even when the calculator does not show an increased result.
Should albumin be corrected when using an anion gap calculator?
In many cases, yes. Since albumin is a key unmeasured anion, hypoalbuminemia can make the measured anion gap appear reduced than it actually is. Using albumin correction can produce a more accurate corrected anion gap, which improves interpretation of blood test results.
When is a high anion gap in kidney failure an emergency?
A high anion gap in kidney failure can be critical when it is paired with severe symptoms such as confusion, breathing difficulty, chest pain, marked weakness, fainting, or rapidly worsening illness. It may also be an emergency if there is severe metabolic acidosis, suspected lactic acidosis, ketoacidosis, or possible toxin ingestion. Prompt medical evaluation is important when the clinical picture points to a serious acid-base disorder.