What’s the Anion Gap?
The anion gap is a useful way to evaluate the equilibrium of electrically charged particles in the blood. It is a computed value that may reveal an acid-base imbalance, especially when there are unmeasured anions contributing to a metabolic derangement. In plain language, it relates the primary measured cations and anions in serum chemistry, usually using sodium, chloride, and bicarbonate.
A common formula is:
Anion gap = sodium - (chloride + bicarbonate)
This value is often derived from a basic metabolic panel. The result can help reveal underlying causes of acid-base imbalance, including high anion gap metabolic acidosis. When the anion gap is elevated, it often means there are extra acids in the bloodstream that are not directly measured in the standard lab panel.
The anion gap is not a diagnosis by itself. It is a helpful clue that must be interpreted in the context of symptoms, the clinical assessment, and other lab data. Factors such as albumin, electrolyte imbalance, and changes in chloride can all influence the result. Because albumin is one of the primary unmeasured anions, a low albumin level can make the anion gap appear reduced than it really is.
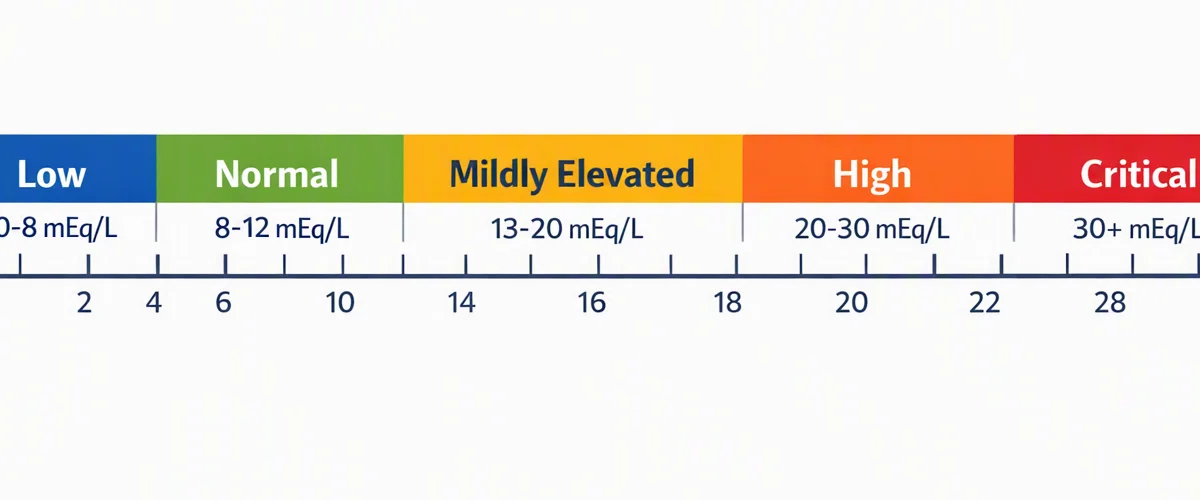
How to Operate an Anion Gap Calculator
An Anion Gap Calculator is a helpful tool for rapidly estimating the gap from everyday labs. You typically add the values for sodium, chloride, and serum bicarbonate from the basic metabolic panel. The calculator then follows the standard formula and gives you a number that can guide lab interpretation.
To use the result well, it helps to look past the single number. A normal anion gap does not always rule out a serious problem, and an elevated anion gap does not tell you the exact cause. The calculator is most helpful when paired with clinical context, a symptom pattern, and a broader toxicology workup if poisoning is possible.
Albumin correction is especially important. Because albumin affects the measured balance of electrolytes, a low albumin level can hide an elevated anion gap. Correcting for albumin may detect hidden acidosis and improve acid-base balance interpretation. In many cases, the corrected value provides a more precise picture of the underlying metabolic derangement.
Serum bicarbonate is a key input because it reflects the body’s buffering status. A low bicarbonate level often points toward metabolic acidosis, while a higher value may be seen in other settings. When the number is abnormal, it should trigger a search for the reason, not just the result.
Can Salicylates Increase the Anion Gap?
Absolutely. Salicylates can increase the anion gap, especially in salicylate toxicity. Aspirin is the most familiar salicylate, and overdose or repeated excess use can produce a classic toxicology picture. One major effect is high anion gap metabolic acidosis caused by the accumulation of unmeasured anions and organic acids.
Salicylates interfere with cellular metabolism, raise acid production, and disrupt normal respiratory and metabolic control. This creates a complex acid-base disorder rather than a simple one. A person can have both respiratory alkalosis and metabolic acidosis at the same time, which is why salicylate poisoning is a well-known mixed disorder.
The anion gap may rise because of several contributing factors, including lactate production and the presence of ketones. Salicylates can also reduce oxidative metabolism and lead to a metabolic state where acids accumulate faster than the body can compensate. That is why the elevated anion gap is an valuable diagnostic clue when aspirin exposure or salicylates are suspected.
However, salicylate toxicity does not always show up with the same lab pattern at every stage. Early on, the anion gap may be normal, especially before a major acid load builds up or before lab changes fully evolve. Later, as metabolic acidosis deepens, the gap is more likely to increase.
Why Salicylate Poisoning Can Cause Mixed Acid-Base Disorders
Salicylate poisoning can drive a mixed disorder because it affects both breathing and metabolism. Early in toxicity, respiratory alkalosis is common because salicylates activate the respiratory center, causing hyperventilation. This decreases carbon dioxide and can raise the blood pH initially.
At the same time, salicylates promote metabolic acid generation and interfere with normal energy use, leading to metabolic acidosis. That acidosis can be driven in part by lactate and ketones, especially when the body shifts into a strained, inefficient metabolic state. The result is a compensatory response that can look confusing on labs: an alkaline pH from hyperventilation, but a low bicarbonate level from acid accumulation.
This explains why salicylate toxicity is a classic example of a combined disturbance. Someone may seem to have one problem on the arterial blood gas, yet the blood chemistry indicates another. Thorough acid-base balance review is important, especially when the clinical picture includes toxin exposure or excess ingestion symptoms.
Common Test Results in Salicylate Toxicity
When salicylate poisoning is considered, the arterial blood gas is frequently one of the most helpful tests. It can show low carbon dioxide with alkalosis, acidic metabolic changes, or a mixed picture depending on the point of illness. The pH may be high, normal, or low, so looking only at pH can miss the diagnosis.
The bicarbonate level is usually decreased when metabolic acidosis is present. The serum salicylate level is also important for toxicology assessment, but it should be interpreted in conjunction with symptoms and acid-base findings rather than in isolation. A person with notable symptoms may need repeated testing because levels and clinical status do not always correspond perfectly at a single time point.
Other frequent findings may include electrolyte abnormalities, changes in chloride, and evidence of respiratory compensation. The basic metabolic panel can show a reduced bicarbonate level and an elevated anion gap, which strengthens the suspicion for salicylate poisoning. In severe cases, the lab pattern may point to widespread metabolic derangement rather than sample anion gap calculation a single isolated abnormality.
How the Anion Gap May Be Unchanged or Increased
In salicylate toxicity, the anion gap may be normal early and elevated later. That variation depends on when testing occurs, severity, and whether albumin is low enough to mask the true gap. Because albumin is an important unmeasured anion, hypoalbuminemia can make laboratory interpretation more difficult.
When albumin is low, an albumin correction should be considered so the anion gap is not falsely reassuring. This matters because the body may already be experiencing metabolic acidosis even if the uncorrected number looks near normal. In other words, the normal anion gap is not always truly normal when albumin is reduced.
The key is to interpret the result as part of the overall clinical assessment. The presence of unmeasured anions, changes in bicarbonate, and the symptom pattern can all support the diagnosis. A calculator result is only one piece of the toxicology puzzle.
Alternate Reasons of a Raised Anion Gap to Consider
Not all elevated anion gap is the result of salicylates. A thorough differential diagnosis is crucial because several dangerous conditions can produce a similar lab pattern. Common alternatives include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols.
Lactic acidosis can occur with reduced tissue perfusion, severe infection, or different metabolic stress. Ketoacidosis may be seen in diabetes, starvation, or prolonged vomiting, and it often produces ketones that anion gap in chronic kidney disease elevate the gap. Renal failure can cause acid retention because the kidneys cannot clear acids effectively. Toxic alcohols are another major concern because they can create significant acid-base abnormalities and require urgent treatment.
This is why lab interpretation must go beyond a single Anion Gap Calculator value. The result should be matched with the history, symptoms, serum chemistry, and, when needed, additional toxicology tests. The pattern of acid-base disorder can help narrow the cause, but it almost never tells the whole story by itself.
When to Pursue Urgent Clinical Evaluation
Immediate healthcare evaluation is important if salicylate toxicity is suspected, especially when overdose signs are present. Warning signs can include tinnitus, hyperventilation, vomiting, confusion, fever, or rapid worsening of the general condition. Tinnitus is a classic symptom and should not be ignored when aspirin or other salicylates are involved.
Because salicylate poisoning can advance fast, poison control should be contacted without delay if an overdose is suspected. This is especially important if the person is breathing rapidly, has an altered mental status, or shows signs of metabolic acidosis. Prompt treatment decisions depend on the clinical picture, not just the lab number.
If a person has taken an excessive amount of aspirin or another salicylate product, do not wait for the symptoms to worsen. Prompt evaluation can help confirm the diagnosis, measure the serum salicylate level, and evaluate acid-base balance before the situation becomes more severe.
FAQ
Can salicylates consistently increase the anion gap?
No. Salicylates do not necessarily increase the anion gap at first. During early salicylate toxicity, the gap may still be normal, particularly before significant metabolic acidosis develops or if albumin is low enough to mask the rise. As time passes, however, salicylates frequently lead to an elevated anion gap because of accumulating unmeasured anions and acid generation.
Can aspirin toxicity cause both respiratory alkalosis and metabolic acidosis?
Yes, it can. Aspirin toxicity is a classic cause of a mixed disorder with both respiratory alkalosis and metabolic acidosis. Salicylates stimulate breathing, which lowers carbon dioxide, while also driving acid accumulation that lowers bicarbonate. That combination can make the arterial blood gas and serum chemistry look conflicting unless they are interpreted together.
Which anion gap result is concerning for salicylate poisoning?
No single value definitively that proves salicylate poisoning, but an elevated anion gap with low bicarbonate and compatible symptoms should raise concern. The exact number matters less than the pattern and the clinical context. If the patient has hyperventilation, tinnitus, or other overdose symptoms, further toxicology evaluation is warranted even if the gap is only mildly abnormal.
Is it necessary to have albumin be corrected when interpreting the anion gap?
Definitely. Albumin correction is often important because low albumin can make the anion gap appear falsely normal or less abnormal than it really is. Since albumin is a major unmeasured anion, correcting for it improves clinical interpretation and helps identify hidden metabolic acidosis. This is especially useful when the basic metabolic panel seems inconsistent with the patient’s symptoms.
Which other conditions can look similar to salicylate toxicity on labs?
Several conditions can resemble salicylate toxicity on labs, including lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each can produce an elevated anion gap and metabolic acidosis, so the diagnosis depends on the overall symptom pattern, history, and additional testing. An arterial blood gas, serum salicylate level, and careful acid-base balance review help separate these possibilities.