What Is Hyperchloremic Acidosis?
Hyperchloremic acidosis is a form of metabolic acidosis in which the body has more acid than base, but the anion gap stays normal. It is also called normal anion gap metabolic acidosis or non-anion gap acidosis. The important test pattern is a decrease in bicarbonate paired with a rise in chloride, which helps preserve electroneutrality.
This is important because it points to the mechanism of the disorder. Instead of building up unmeasured acids, the body often sheds bicarbonate or replaces it with chloride. That shift changes serum bicarbonate and serum chloride while leaving the calculated gap relatively unchanged. For that reason, hyperchloremic acidosis is more of a indicator about the type of acid-base problem than a single disease.
In practice, hyperchloremic acidosis reflects an acid-base balance problem caused by an electrolyte imbalance. The blood chemistry may show reduced bicarbonate, elevated chloride, and a normal calculated gap, which is why careful clinical interpretation is essential. It is a common diagnostic clue when interpreting lab values and assessing systemic acidemia.
What Is the Anion Gap and How Do You Calculate It?
The anion gap is a formula used to estimate the difference between the major measured cations and negative ions in blood. In everyday practice, an anion gap calculator helps quickly handle this step and reduce arithmetic errors. The most common anion gap formula uses sodium, chloride, and bicarbonate values from the basic metabolic panel.
A simple version of the calculation is:
Anion gap = sodium - (chloride + bicarbonate)
Because sodium is the major measured cation and chloride and bicarbonate anion gap in chronic kidney disease are the main measured anions, the gap estimates the amount of unmeasured charged particles in serum. A normal result suggests that the acid-base disturbance may be due to bicarbonate loss or chloride gain rather than an increase in unmeasured acids.
An anion gap calculator is particularly useful when reviewing serum electrolytes alongside the remainder of the chemistry panel. It can support quick lab interpretation and identify whether the pattern fits a normal gap disorder or a gap metabolic acidosis. That distinction is central to clinical interpretation because it shifts the differential diagnosis.
In practice, the anion gap is influenced by several factors, including albumin, delta ratio calculation method which is a key unmeasured anion. Low albumin can make the gap appear falsely normal, so the raw number should never be interpreted in isolation.
Why Hyperchloremic Acidosis Often Has a Normal Anion Gap
Hyperchloremic acidosis often produces a unchanged anion gap because the decrease in bicarbonate is matched by a increase in chloride. This relationship preserves electroneutrality. When bicarbonate is lost, chloride commonly increases to maintain balance among the measured ions, so the calculated gap does not increase much.
This is the main distinction between hyperchloremic acidosis and high gap metabolic acidosis. In high-gap states, the body retains unmeasured acids, which widens the gap. In hyperchloremic states, the issue is often bicarbonate loss or chloride replacement, so the problem shows up as a variation in measured electrolytes rather than a buildup of hidden anions.
Put another way, the body may be discarding base, not adding a large amount of new acid. That is why the lab pattern is often called normal anion gap metabolic acidosis. The chemistry pattern is still a real metabolic acidosis, but the chloride rise balances the bicarbonate decline.
This pattern is useful when examining serum chloride, serum sodium, and serum bicarbonate. If the bicarbonate is reduced and chloride is high, the problem is likely a non-anion gap process. The pattern can also reflect metabolic compensation in some settings, but persistent bicarbonate loss generally indicates a primary disorder.
Typical Causes of Hyperchloremic Acidosis
Various disorders can lead to hyperchloremic acidosis, and they often share a similar pattern: bicarbonate loss, poor renal acid processing, or chloride loading. Pinpointing the cause helps with specific therapy and improves acid-base balance.
- Diarrhea: Loss of bicarbonate-rich digestive fluids can lead to a non-anion gap acidosis. Renal tubular acidosis: The kidneys cannot adequately remove acid or retain bicarbonate, leading to renal acid excretion problems. Normal saline: High-volume infusion can elevate chloride and decrease bicarbonate, causing a hyperchloremic pattern. Kidney disease: Declining kidney function can impair acid handling and contribute to electrolyte shifts.
Diarrhea is a well-known cause because gastrointestinal bicarbonate loss can be significant. The result is a low bicarbonate level with compensatory chloride increase. This is a classic example of bicarbonate loss driving a non-anion gap acidosis.
Renal tubular acidosis is another major cause. In this category of disorders, the kidneys fail to acidify urine as they should or preserve bicarbonate effectively. The disorder may be a key clue in a patient with chronic electrolyte imbalance, persistent low bicarbonate, and a normal anion gap.
Normal saline can also play a role, especially when given in large amounts. Because saline contains a elevated chloride content, it can cause a apparent increase in serum chloride and a fall in bicarbonate. This is a useful example of how treatment itself may affect blood chemistry and the acid-base picture.
Kidney disease may lead to hyperchloremic acidosis as renal function declines and acid handling becomes less efficient. In some cases, the pattern reflects impaired ammonium output, ongoing acid load, and impaired buffering. Reviewing the full clinical context and lab values is essential for correct diagnosis.
Interpreting the Anion Gap in Acid-Base Conditions
Assessing the anion gap requires more than looking at a single result. The result should be viewed alongside pH, bicarbonate, chloride, albumin, and the overall acid-base disorder. A normal gap does not always mean the problem is minor, and a high gap does not necessarily mean the cause is obvious.
Albumin matters because it is a major unmeasured anion. When albumin is low, the measured gap may underestimate the true burden of unmeasured acids. That is why a corrected anion gap is often required. Correction helps avoid missing a hidden high-gap process in a patient whose albumin is reduced.
The delta gap is another important tool. It helps identify whether more than one acid-base process is present by comparing the rise in anion gap with the fall in bicarbonate. If the numbers do not match expected patterns, a mixed acid-base disorder may be present.
For example, a patient can have a normal anion gap acidosis and a separate high-gap process at the same time. In such cases, the apparent pattern may be misleading unless corrected for albumin and evaluated with the delta gap. This is where careful lab interpretation becomes essential.
Useful interpretation steps include:
- Assess the raw anion gap and compare it with the expected range. Review albumin and calculate the corrected anion gap if needed. Look at the relationship between bicarbonate and chloride. Apply the delta gap to screen for a mixed disorder. Align the pattern with the clinical picture and underlying acid-base disorder.
This approach allows more accurate clinical interpretation and helps distinguish a pure hyperchloremic process from a more complex acid-base disturbance.
When a Increased Anion Gap and Chloride elevation Can Coexist
A high anion gap and hyperchloremia can coexist when multiple process is occurring at once. This is a classic mixed acid-base disorder. The patient may have a increased-gap process from one cause and a hyperchloremic component from another.
Common examples include lactic acidosis, ketoacidosis, and toxic ingestion. These conditions often increase unmeasured acids, creating a elevated anion gap. At the same time, chloride may increase or bicarbonate may drop further, producing a second pattern that can blur the overall picture.
For instance, a patient with ketoacidosis may receive large volumes of normal saline, which can introduce a hyperchloremic component to the already existing high-gap disorder. Similarly, lactic acidosis may coexist with chloride retention or bicarbonate loss, making the lab values more difficult to interpret.
Toxic ingestion can also produce mixed patterns depending on the substance and the timing of presentation. Some toxins cause high-gap acidosis directly, while treatment or fluid shifts may later introduce a hyperchloremic component. This is why looking only at the anion gap without the rest of the blood chemistry can miss important context.
The delta gap is especially useful here because it helps reveal whether the bicarbonate drop is larger or less severe than expected from the rise in anion gap alone. When the numbers do not fit a single disorder, mixed physiology should be strongly suspected.
How an Anion Gap Calculator Assists in Clinical Practice
An anion gap calculator is a useful tool for quick review of serum electrolytes. It aids bedside treatment decisions by helping clinicians compare sodium, chloride, and bicarbonate values efficiently. This makes it easier to recognize whether a patient has hyperchloremic acidosis, a high-gap disorder, or a mixed pattern.
In daily practice, the calculator helps with:
- Fast screening of electrolytes during evaluation of acidemia. Improved lab interpretation when bicarbonate is low. Monitoring serum bicarbonate changes over time. Helping interpret serum chemistry panels in complex cases. Noticing when chloride rise suggests a non-anion gap process.
The tool is especially helpful when paired with clinical context. If the patient has diarrhea, renal tubular acidosis, recent saline resuscitation, or kidney disease, the anion gap result may help support the likely mechanism. If the gap is unexpectedly high or normal in the setting of serious illness, that may be a signal to look for a hidden mixed disorder.
A calculator does not substitute for judgment, but it strengthens it. By combining the anion gap with albumin correction, bicarbonate review, and delta gap analysis, clinicians can interpret blood chemistry more clearly and identify the source of the acid-base imbalance.
Used well, the anion gap calculator becomes not merely a math tool. It becomes a diagnostic aid that supports better recognition of electrolyte patterns, faster clinical interpretation, and more targeted management of systemic acidemia.
Common Questions
In what way is hyperchloremic acidosis different than high anion gap acidosis?
Hyperchloremic acidosis often presents as a normal anion gap metabolic acidosis due to bicarbonate loss or chloride gain, whereas high anion gap acidosis involves the buildup of unmeasured acids. In hyperchloremic acidosis, chloride rises as bicarbonate falls, but in high anion gap states the gap increases because of acids such as lactate or ketones.
What causes hyperchloremic acidosis usually have a normal anion gap?
It often has a normal anion gap because bicarbonate falls while chloride rises, which maintains electroneutrality. As the measured ions shift in opposite directions, the calculated anion gap frequently stays within the normal range.
Does normal saline cause hyperchloremic acidosis?
Yes. Large amounts of normal saline can increase chloride and dilute bicarbonate, leading to hyperchloremic acidosis. This is a frequent cause of non-anion gap acidosis in patients who get significant fluid resuscitation.
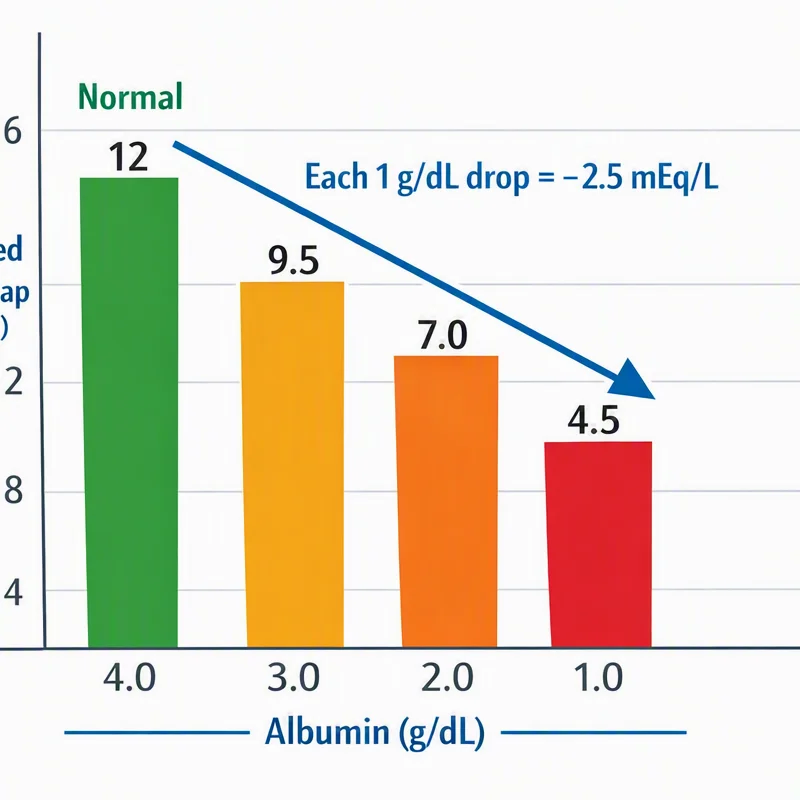
How is the anion gap with respect to albumin?
The anion gap is calculated by taking sodium minus the sum of chloride and bicarbonate. To adjust for albumin, you raise the result when albumin is low because low albumin can make the gap seem falsely normal. This albumin-corrected anion gap offers a better estimate of hidden unmeasured acids.
What are common causes of hyperchloremic acidosis?
Frequent causes include diarrhea, renal tubular acidosis, normal saline use, and kidney disease. These conditions commonly result in bicarbonate loss, impaired renal acid excretion, or chloride loading, all of which may produce a normal anion gap pattern.