What Is the Anion Gap?
The anion gap is a derived value used in acid-base balance to help identify hidden acids in the blood. It is derived from the serum electrolytes, especially sodium, chloride, and bicarbonate, and it serves as a useful laboratory interpretation tool during a biochemical evaluation.
In its standard form, the anion gap reflects the difference between measured cations and measured anions. Because some charged particles are not directly reported on a standard electrolyte panel, the more info gap helps clinicians determine the presence of unmeasured anions. That makes it a valuable diagnostic clue when evaluating an acidotic state.
Although the formula may vary slightly by institution, the core idea stays the same: if serum sodium is much higher than the combined measured anions, an accumulation of acids may be present. This is why the anion gap is central to identifying metabolic acidosis, especially high anion gap metabolic acidosis.
For example, when a patient has low serum bicarbonate with an elevated gap, the pattern suggests that acid has been brought to the system rather than simply lost through the gut or kidneys. In clinical assessment, that distinction matters because it focuses the differential diagnosis and informs treatment.
How Lactic Acidosis Raises the Anion Gap
Lactic acidosis elevates the anion gap because lactate is an unaccounted-for anion. When lactate accumulates, it leads to metabolic acidosis by using up bicarbonate and expanding the pool of negatively charged substances that are not included in a routine electrolyte panel.
This happens most often when oxygen delivery or utilization is impaired. Hypoperfusion and hypoxia shift cells toward anaerobic metabolism, creating more lactate. In critical illness, this process can indicate tissue stress, reduced clearance, or both.
From a practical standpoint, the elevated gap is not the cause of the acidosis; it is the sign that something like lactate, ketoacids, or toxins is accumulating. That is why a high gap is considered a severity marker rather than a diagnosis by itself. The biochemical evaluation should always be paired with the clinical picture.
In sepsis, for example, the anion gap may rise because of poor perfusion, inflammatory metabolic derangement, and rising serum lactate. But the same pattern can appear in many other conditions, so the gap should be interpreted as part of broader clinical assessment rather than used in isolation.
Using an Anion Gap Calculator
An Anion Gap Calculator is a practical utility that simplifies the calculation with the main lab values from the electrolyte panel. To use it correctly, input the available measurements for serum sodium, serum chloride, serum bicarbonate, and, when the calculator allows, potassium and serum albumin.
The most common calculation is:
Anion gap = sodium − (chloride + bicarbonate)
Some calculators include potassium, while others omit it. Both methods can be valid if you know which reference range the tool uses. What matters most is alignment with the method used by your institution or practice setting.
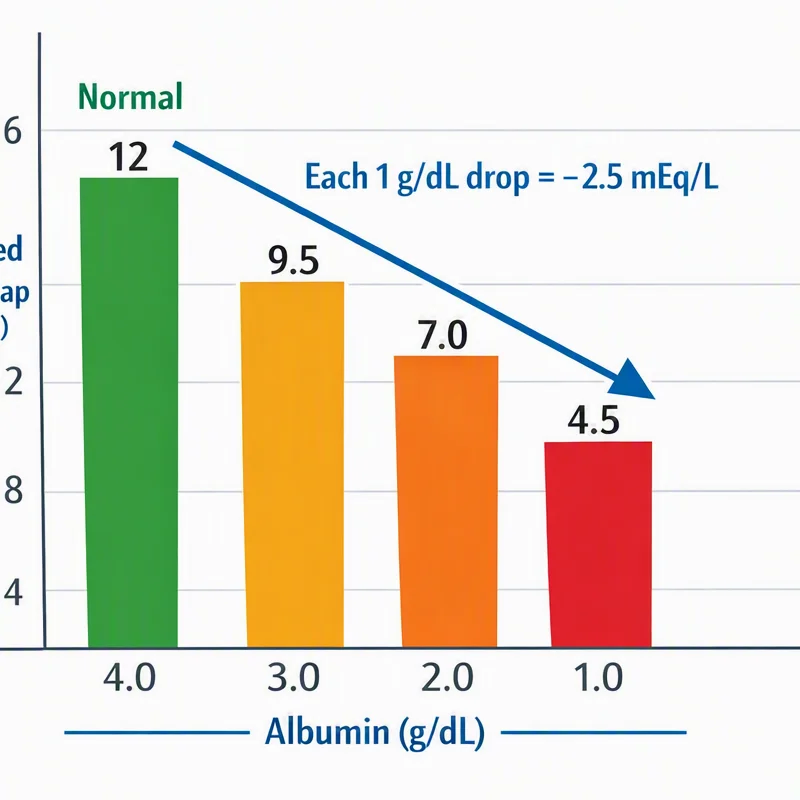
Albumin is especially important because low albumin can mask a real gap elevation. Since serum albumin is a major unmeasured anion, low levels can falsely lower the calculated result. A calculator that includes albumin correction can reveal the more accurate corrected anion gap.
When using the tool, think in steps:
- Confirm the electrolyte panel is complete and current. Check serum sodium, serum chloride, and serum bicarbonate. Enter potassium if the calculator requires it. Review serum albumin and apply albumin correction if needed. Assess the result with the appropriate reference range.
This approach makes the anion gap calculator more than a math shortcut. It becomes part of a organized clinical interpretation workflow that enables rapid decision-making in metabolic acidosis.
Typical, Elevated, and Modified Anion Gap Values
The normal range for anion gap depends on the testing method and whether potassium is included. So the same number may be normal in one setting and somewhat increased in another. Always interpret the value using the local lab reference range.
A high anion gap generally suggests accumulation of acids or other unmeasured anions. In practice, this is the pattern that points clinicians toward high anion gap metabolic acidosis. But the raw number alone is not enough; it must be interpreted alongside serum bicarbonate, pH if available, and the patient’s overall condition.
Albumin correction is essential when serum albumin is low. Because albumin contributes to the measured baseline gap, hypoalbuminemia can make the anion gap appear falsely normal. The adjusted anion gap helps avoid missing clinically important acid buildup.
For example, a patient with an apparently normal anion gap and low albumin may actually have a significantly abnormal corrected value. In that case, the apparent normal gap is misleading, and the biochemical evaluation should continue.
Key interpretation points:
- An increasing gap is more concerning than one isolated value. Low albumin may conceal a real increase. Interpret the reference range in light of the lab method. If albumin is abnormal, rely on the corrected anion gap.
Typical Causes of Elevated Anion Gap Acidosis
The major causes of elevated anion gap metabolic acidosis overlap with acute and severe illness settings. The most common include sepsis, renal failure, ketoacidosis, and toxic alcohol ingestion.
Sepsis can elevate lactate through reduced blood flow and metabolic stress. Renal failure causes accumulation of acids that are normally cleared, increasing the burden of unmeasured anions. Ketoacidosis, including diabetic ketoacidosis and starvation-related ketosis, introduces ketone bodies that expand the gap. Toxic alcohol ingestion can cause a high gap through toxic metabolites.
These possibilities are important because not every high gap is explained by lactate. The differential diagnosis should stay broad, especially when the clinical assessment does not fit isolated lactic acidosis. A patient with severe vomiting, altered mental status, or unexplained electrolyte abnormalities may have more than one process occurring at once.
In practice, the anion gap is a starting point. It reveals a metabolic derangement, but the next step is to determine whether the source is lactate, ketones, kidney dysfunction, toxins, or a mixed process.
Understanding Lactate In Relation to the Anion Gap
Interpreting the lactate level alongside the anion gap enhances clinical interpretation. A raised gap with elevated lactate is consistent with lactic acidosis, but the relationship is not always exact. Lactate may increase before the gap becomes obviously abnormal, and the size of the gap may not match the lactate level perfectly.
That is why perfusion and hypoxia must be considered. Lactate is a reflection of tissue oxygen delivery, mitochondrial stress, and clearance. In some patients, lactate is a dynamic marker of change in illness severity rather than a single static result.
Clinically, a elevated serum lactate in the setting of acid-base abnormalities may suggest worsening tissue hypoxia or poor perfusion. But interpretation should include blood pressure, oxygenation, renal function, and the patient’s overall trajectory. The anion gap becomes a useful severity marker when viewed as part of the full clinical assessment.
A practical way to think about it:
- Elevated lactate plus increased anion gap: strongly supports lactic acidosis. Raised lactate plus normal gap: still possible, especially early or with masking factors. Normal lactate plus high gap: look for other acids or a mixed disorder.
This type of stepwise reasoning is what makes the anion gap calculator useful in real-world laboratory interpretation.
When a Normal Anion Gap Does Not Rule Out Lactic Acidosis
A normal anion gap fails to fully exclude lactic acidosis. This is especially true in early lactic acidosis, where lactate has begun to rise but not enough to shift the gap beyond the reference range. It is also true when competing processes create a mixed acid-base disorder.
For example, a patient may have lactic acidosis along with a metabolic alkalosis from vomiting, or a hyperchloremic process that offsets the widened gap. In these situations, the measured values can look deceptively within range even though the patient remains in an acidotic state.
The delta gap can help identify these situations. By comparing the change in the anion gap to the change in serum bicarbonate, clinicians can look for evidence of additional acid-base processes. A discordant delta gap can point toward a mixed acid-base disorder rather than a simple isolated lactic acidosis.
Albumin also matters here. Low serum albumin can make the gap appear normal even when organic acids are accumulating. That is why albumin correction is crucial before concluding that lactic acidosis is absent.
Bottom line: a normal value does not always mean a normal process. If the clinical picture suggests hypoperfusion, hypoxia, or severe illness, lactic acidosis can still be present and the diagnostic workup should continue.
Common Questions Clinicians Frequently Ask
When using an anion gap calculator in practice, doctors often ask the same main concerns about identification, monitoring, and treatment response. Such questions count because the gap is especially valuable when it guides decision-making over time, not just at a single point.
For diagnosis, the anion gap helps determine whether metabolic acidosis is attributable to unmeasured acids. For serial assessment, serial measurements can show whether the underlying cause is improving. For treatment response, a falling gap may suggest that lactate is declining or that another driver of acidosis is improving. For acid-base balance, the gap helps distinguish high anion gap metabolic acidosis from other patterns such as non-gap acidosis or combined disorders.
Several practical questions include:
- Is the value actually abnormal for this lab’s reference range? Is albumin low enough to adjust for? Are lactate trends matching the patient’s perfusion status? Might renal failure, ketoacidosis, or toxic alcohol ingestion account for the result? Is there a suggestion of a mixed acid-base disorder that changes the interpretation?
These questions highlight why the anion gap should be used as part of ongoing clinical assessment rather than as a lone measurement. It is a helpful clue, a marker of anion gap in chronic kidney disease severity, and a way to track metabolic derangement over time.
Common Questions
What does a high anion gap mean in lactic acidosis?
A high anion gap means there are more unmeasured anions in the blood, and in lactic acidosis that often reflects increasing lactate. It supports the diagnosis of high anion gap metabolic acidosis, especially when serum bicarbonate is low and the clinical picture suggests hypoperfusion, hypoxia, or critical illness.
Can lactic acidosis present with a normal anion gap?
Yes. Early lactic acidosis, low albumin, or a mixed acid-base disorder can produce a normal anion gap even when lactate is elevated. That is why the anion gap should be interpreted together with serum lactate, serum bicarbonate, and the overall clinical assessment.
How do you adjust the anion gap for reduced albumin?
Albumin correction adjusts the calculated gap higher when serum albumin is low, because albumin is a key unmeasured anion. The exact formula can vary by institution, but the goal is the same: avoid missing a true elevated corrected anion gap when hypoalbuminemia is present.
Is lactate always elevated when the anion gap is high?
No, it is not. A high anion gap can be caused by lactic acidosis, but also by ketoacidosis, renal failure, and toxic alcohol ingestion. In addition, lactate may not rise enough to fully explain the gap in every case, so serum lactate should be checked as part of the evaluation.
What other conditions can cause a high anion gap besides lactic acidosis?
Common causes include sepsis, renal failure, ketoacidosis, and toxic alcohol ingestion. These conditions increase unmeasured anions or limit acid clearance, leading to high anion gap metabolic acidosis. Clinicians should consider the full biochemical evaluation before assuming lactate is the only cause.