Delta gap interpretation is a hands-on way to extend the value of an Anion Gap Calculator outside a single result. Instead of just using the anion gap, clinicians contrast the shift in the anion gap with the change in bicarbonate to identify combined patterns, concealed abnormalities, and expected compensation. This makes the delta gap especially valuable in acid-base balance analysis, where a single disturbance may mask another.
In a straightforward case, metabolic acidosis may show a clearly elevated anion gap. But if the bicarbonate drop is more pronounced or lesser than expected, the pattern may suggest a mixed acid-base disorder. The delta gap improves this interpretation by turning lab values into a diagnostic approach that encourages pattern recognition, correction, and clinical significance.
To use it well, you need more than a formula. You need to interpret what the numbers mean in the context of serum sodium, serum chloride, serum albumin, and the overall electrolyte panel. You also need to know when the result points to high anion gap metabolic acidosis, when it suggests non-anion gap metabolic acidosis, and when a secondary process such as metabolic alkalosis is present in the background.
What Is the Delta Gap?
The anion gap is a calculated measure used to gauge unmeasured ions in the blood. It is commonly used in metabolic acidosis assessments because it helps show whether the acidosis is caused by acid buildup or by direct bicarbonate loss. The delta gap goes one step further by comparing the rise in anion gap to the fall in bicarbonate.
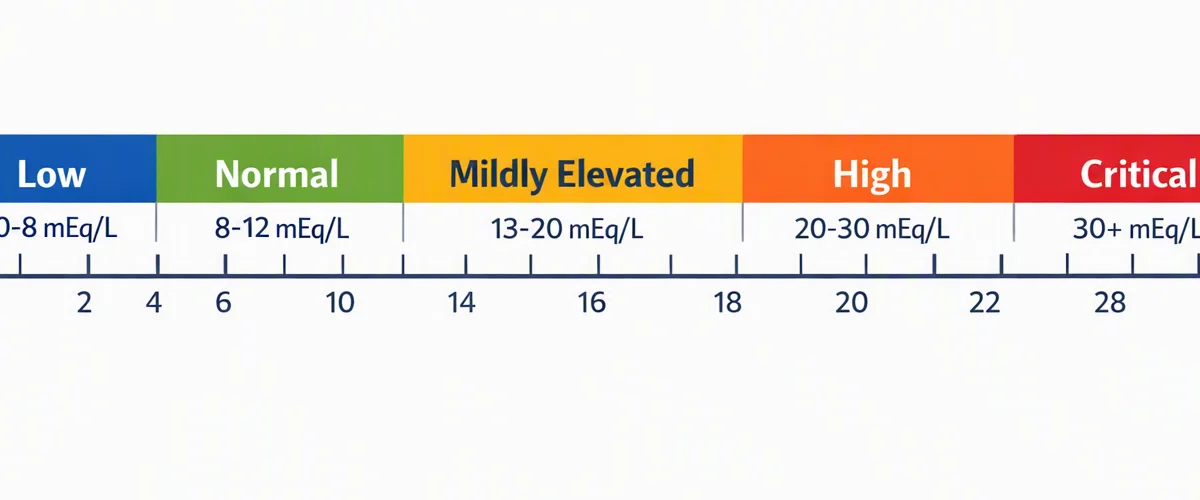
In practical terms, the delta gap asks: if the anion gap has increased, has bicarbonate fallen by the amount we would expect? If not, there may be a different acid-base disorder present. This is why delta gap analysis is part of a larger acid-base evaluation rather than a standalone diagnosis.
The concept is especially helpful in detecting overlap. For example, a patient with high anion gap metabolic acidosis may also have a simultaneous non-anion gap metabolic acidosis from diarrhea or renal tubular dysfunction. Alternatively, a patient may have a high anion gap process plus metabolic alkalosis, which can reduce the expected bicarbonate decrease. The delta gap adds structure to that assessment.
One reason the delta gap matters is that the anion gap alone can miss important context. A apparently normal gap does not always mean the patient has a normal acid-base state, especially if serum albumin is low or if compensation is present. The delta gap adds a further layer of interpretation that increases diagnostic accuracy.
Calculating Delta Gap Step-by-Step
An Anion Gap Calculator is the quickest way to complete the initial calculation, but following the steps is crucial for interpretation. The process usually begins with the standard anion gap formula:
Anion gap = serum sodium − (serum chloride + bicarbonate)
Once the anion gap is calculated, compare it with the expected normal anion gap for that lab, then compare the change in gap with the change in bicarbonate. This is where the delta ratio comes in. In many clinical settings, the delta ratio is calculated as:
Delta ratio = (measured anion gap − normal anion gap) / (normal bicarbonate − measured bicarbonate)
This is a useful ordered framework for assessment:
- Check the basic electrolytes, including serum sodium, serum chloride, and bicarbonate. Apply the anion gap calculator or the formula to determine the anion gap. Determine whether the anion gap is elevated relative to the lab’s normal range. Estimate how much bicarbonate has fallen. Compare the two changes to assess whether the pattern fits a pure disorder or a mixed process.
The idea is not only calculation but also interpretation. If the gap is elevated more than expected for the bicarbonate drop, another process may be raising bicarbonate, such as metabolic alkalosis. If the bicarbonate falls more than expected, another process such as non-anion gap metabolic acidosis may be present.
It is also important to consider serum albumin. Because albumin is a major unmeasured anion, hypoalbuminemia can lower the apparent anion gap. That means the corrected anion gap may be more accurate than the raw value, especially in critically ill patients or those with chronic disease.
What exactly a Typical Delta Gap Indicates
A expected delta gap often implies that the change in anion gap is proportional to the change in bicarbonate. In a straightforward case, this supports a single acid-base disturbance, most commonly a uncomplicated high anion gap metabolic acidosis. Yet, “normal” does not always mean simple; it means the numbers are responding in a methanol anion gap elevation way that matches expectation.
For instance, if a patient has metabolic acidosis with elevated anion gap and the bicarbonate decrease aligns with the rise in gap, the pattern may be suggestive of a single primary process. In that situation, respiratory compensation should still be evaluated with blood gas analysis, because the lungs may be lowering carbon dioxide properly in response to the acid load.
A normal delta gap can also aid in distinguishing a pure high-gap disorder from a mixed one. If the ratio is roughly expected, you are less likely to have a simultaneous metabolic alkalosis or an added non-anion gap metabolic acidosis. That makes the pattern easier to interpret and can simplify the diagnostic approach.
Still, a normal delta gap does not exclude all complexity. A patient with kidney disease, volume depletion, or abnormal albumin may still have multiple overlapping processes. The delta gap should be used as part of a more complete assessment, not as a replacement for clinical assessment.
How to Understand an High Delta Gap
An elevated delta gap, often reflected by a raised delta ratio, implies that the elevation in anion gap is larger than the drop in bicarbonate. In practice, this often means there is a separate process increasing bicarbonate or offsetting the expected acidemia. One common explanation is simultaneous metabolic alkalosis.
This pattern is important in clinical practice because it can obscure the true severity of the primary disorder. A patient may seem to have only mild metabolic acidosis on paper, but the elevated delta gap reveals an additional alkalinizing process. That overlap changes the interpretation and may affect treatment decisions.
Common causes of a high delta ratio include:
- Metabolic alkalosis coexisting with a high-gap acidosis Lactic acidosis with concurrent vomiting or diuretic effect Ketoacidosis with a coexisting contraction alkalosis
In lactic acidosis, tissue hypoperfusion or impaired oxygen delivery promotes acid generation. If the patient is also volume depleted, the bicarbonate reduction may be smaller than expected because of a separate alkalinizing process. The same can happen in ketoacidosis, where vomiting, poor intake, or prior treatment can create a mixed picture.
The practical message is that an elevated delta gap suggests overlap. It is a clue that the acid-base picture is not due to a single disorder. The best interpretation comes from combining the delta ratio with blood gas analysis, clinical context, and the rest of the electrolyte panel.
Interpreting a Reduced Delta Gap
A low delta gap indicates bicarbonate has fallen more than expected for the extent of anion gap increase. This pattern suggests that the patient may have both a high-gap process and an additional non-anion gap metabolic acidosis. One of the leading causes is hyperchloremic acidosis.
Hyperchloremic acidosis often appears when bicarbonate is lost and chloride goes up to maintain electroneutrality. This can happen with diarrhea, certain renal disorders, or after treatment of another metabolic disorder. The result is a decreased bicarbonate than the high-gap condition alone would predict.
Renal tubular acidosis is another significant cause. In this setting, the kidneys fail to handle acid and bicarbonate properly, producing a non-gap component that can coexist with another acid-base disorder. The delta gap helps reveal that overlap.
Before deciding that the patient has a true mixed disorder, consider laboratory error. Pre-analytic issues, specimen contamination, or transcription mistakes can skew serum sodium, serum chloride, or bicarbonate values. If the result does not fit the clinical picture, repeating the labs is often the appropriate assessment.
Serum albumin also matters here. Low albumin can make the measured anion gap appear reduced than it truly is. If hypoalbuminemia is present, you should consider correction for albumin before interpreting the delta gap. Without that step, a low or borderline result may be inaccurate.
Typical Clinical Presentations and Errors
Various typical disorders can complicate delta gap analysis. One important issue is toxic alcohol ingestion. Methanol, ethylene glycol, and similar compounds can lead to a severe high anion gap metabolic acidosis, but the first pattern may be difficult to recognize without careful analysis. The delta gap can support suspicion of an extra process, but it should not take the place of targeted toxicology testing.
Salicylate toxicity is another classic pitfall. It can cause a mixed acid-base disorder, often blending respiratory alkalosis with metabolic acidosis. Because the acid-base pattern is complicated, delta gap review should be combined with blood gas analysis and clinical context rather than used in isolation.
Chronic kidney disease can also influence results. Reduced renal acid excretion can cause metabolic acidosis, while retained unmeasured anions may raise the anion gap. Depending on stage and comorbidities, the patient may show high-gap acidosis, non-gap acidosis, or a mixture of both. That overlap makes pattern recognition particularly important.
Another recurrent pitfall is ignoring correction for hypoalbuminemia. Since albumin is a major unmeasured anion, a low albumin level can hide an elevated anion gap. If the albumin is reduced, the anion gap should be adjusted before using it for delta gap interpretation. Otherwise, you may downplay the presence of a hidden high-gap process.
Finally, remember that electrolyte shifts are dynamic. Treatment, fluids, vomiting, renal losses, and ventilation changes can alter the acid-base picture over time. A single measurement gives only a snapshot, so repeat assessment may be needed when the clinical state changes.
When to Use an Anion Gap Calculator in Practice
An anion gap calculator is particularly valuable when the overall findings suggests a metabolic disorder and you need quick, accurate analysis. It is especially helpful when reviewing blood gas analysis alongside the chemistry panel. The blend of pH, carbon dioxide, bicarbonate, and electrolytes gives a more complete assessment than either test alone.
Use the calculator when you have the core data from the chemistry panel, especially serum sodium, serum chloride, and bicarbonate. These values are the foundation of the anion gap formula and the delta gap calculation. If the result is unexpected, recheck whether the lab values are current and whether the specimen is reliable.
It is also important in patients with significant acid-base disturbance where rapid interpretation matters. The calculator can help determine whether the patient likely has:
- High anion gap metabolic acidosis Non-anion gap metabolic acidosis A mixed acid-base disorder Concurrent metabolic alkalosis
Using the tool well requires attention to the overall context of the electrolytes. If serum chloride is elevated, the patient may have a non-gap component. If bicarbonate is unexpectedly preserved, an alkalinizing process may be present. If albumin is low, the apparent gap may be artificially low.
In other words, the calculator gives you the number, but interpretation gives you the diagnosis. That distinction is key to good acid-base evaluation and stronger clinical decision-making.
FAQ: Delta Gap Interpretation
What does a delta gap tell you in acid-base interpretation?
Delta gap interpretation shows whether the rise in anion gap matches the fall in bicarbonate. It helps identify whether the patient has a simple disorder or a mixed acid-base disorder. This makes it a important part of acid-base evaluation and clinical decision-making.
How can you calculate delta gap from anion gap and bicarbonate?
Start by finding the anion gap using the anion gap formula: serum sodium minus serum chloride and bicarbonate. Then assess the change in anion gap with the change in bicarbonate to derive the delta ratio. An Anion Gap Calculator can speed up the calculation, but the interpretation still depends on the clinical context.
What can a normal delta gap suggest clinically?
A normal delta gap usually suggests the increase in anion gap is proportionate to the fall in bicarbonate. Clinically, that often suggests a single primary process such as high anion gap metabolic acidosis, with expected respiratory compensation. It does not rule out other problems, but it makes a mixed disorder less likely.
What does an elevated delta gap suggest?
An elevated delta gap suggests that the anion gap has increased more than bicarbonate has fallen. This often points to a concurrent metabolic alkalosis or another process that is masking the expected acid load. Conditions such as lactic acidosis and ketoacidosis can show this pattern when overlap is present.
Can hypoalbuminemia affect how you interpret the anion gap?
Yes. Hypoalbuminemia can lower the measured anion gap because albumin is a major unmeasured anion. That is why correction for hypoalbuminemia is important before interpretation. If albumin is low, the corrected anion gap may better reflect the true acid-base disorder and improve diagnostic accuracy.