What Are the Anion Gap and Why It Matters
The anion-gap value is a calculated value that helps clinicians assess acid base balance by contrasting common blood electrolytes measured on standard blood testing. It is especially important when reviewing alkalosis or other forms of acid-base disturbance because it can show whether there are hidden acids or other shifts that are not obvious from the basic lab numbers alone.
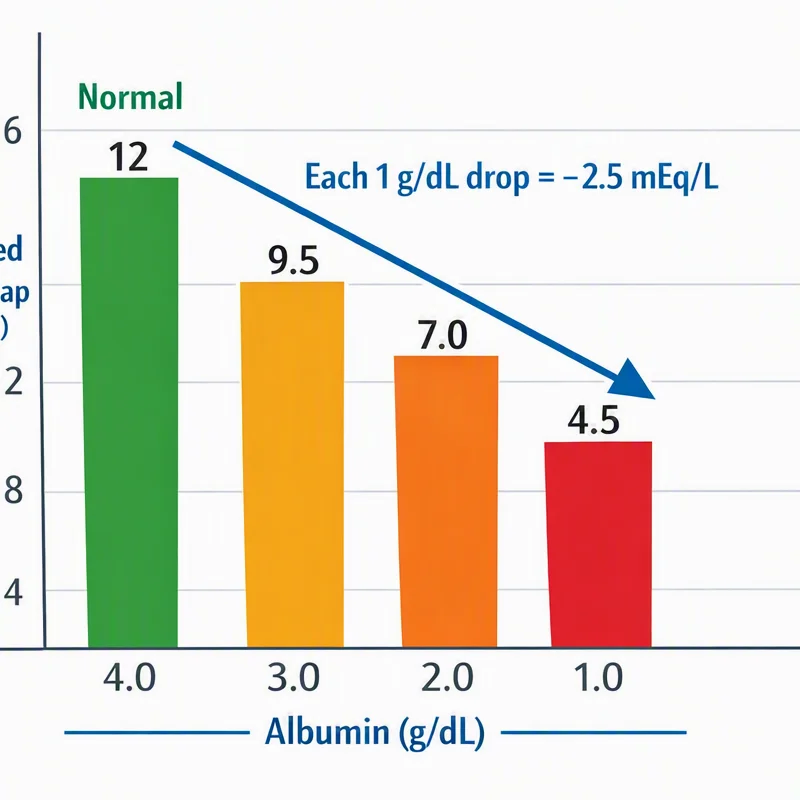
In practical terms, the anion gap helps explain the relationship between positively charged ions and negatively charged ions in the bloodstream. Most often, the main measured values are sodium, chloride, and bicarbonate, while other contributors such as albumin and unmeasured anions may affect the result. That is why the anion gap is more than a number; it is a clue that supports clinical interpretation of a patient’s status.
Although the anion gap is commonly discussed in acidosis, it also matters in metabolic alkalosis because the surrounding clinical context can change how the result is read. A normal, corrected, or elevated value may suggest different underlying processes, especially when paired with other blood electrolytes and lab values from a blood chemistry panel.
How an Anion Gap Calculator Operates
An anion gap calculator is a medical calculator that automates the anion gap formula so you can quickly review blood test results. The standard calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation uses serum sodium, serum chloride, and serum bicarbonate because they are the core values available on a standard electrolyte panel. Sodium is the main measured cation, while chloride and bicarbonate are the primary measured anions used in the calculation. The result is then compared with a reference interval or reference range to determine whether the value is within range or outside range.
Many calculators also offer an optional albumin adjustment. Since albumin is a important unmeasured anion, a low albumin level can make the anion gap appear apparently normal. A thoughtfully made calculator therefore acts as both a diagnostic tool https://anion-gap-results932.timeforchangecounselling.com/anion-gap-calculator-with-guided-results and an interpretation guide, helping with clinical decision making when the numbers do not match the expected pattern.
Anion Gap in Metabolic Alkalosis: Interpretation Basics
In alkalotic metabolic state, the body has a main rise in bicarbonate or loss of acid, and the anion gap may appear normal, slightly changed, or elevated depending on the cause and the patient’s adaptive response. Understanding the anion gap in this setting requires more than simply reading the number; it requires attention to physiologic compensation and the full pattern of lab findings.
A normal anion gap in metabolic alkalosis often suggests that the alkalosis is due to chloride depletion, volume changes, or other processes that do not add excess acids to the bloodstream. An elevated result may suggest a combined disorder, such as concurrent metabolic acidosis, or hidden contributions from unmeasured acids. This is where albumin becomes important, because low albumin can mask a truly increased gap.
For that reason, many clinicians rely on the adjusted anion gap rather than the unadjusted value. The corrected value gives a more accurate picture of lab interpretation, especially when metabolic alkalosis coexists with other changes in acid-base equilibrium. In short, the calculator does not replace judgment; it improves the quality of that judgment.
Inputs Needed for the Calculator
A trustworthy calculator generally needs four inputs: serum sodium, serum chloride, serum bicarbonate, and serum albumin. These values come from a standard blood chemistry panel or electrolyte panel, and each helps refine the final interpretation.
- Serum sodium: the key cation in the calculation. Serum chloride: a significant measured anion that helps determine the gap. Serum bicarbonate: shows buffering status and is central to acid-base evaluation. Serum albumin: used for albumin correction when needed.
These values also support more general lab result analysis. For example, a low bicarbonate may suggest metabolic acidosis, while an elevated bicarbonate is more suggestive of metabolic alkalosis. Chloride trends can help identify chloride-responsive patterns, and albumin helps prevent underestimating the anion gap in patients with hypoalbuminemia.
If any of these values are missing, interpretation becomes less precise. The calculator may still generate a number, but without the full dataset, the result may not reflect the true clinical context.
Step-by-Step Calculation Illustration
Below is a simple sample calculation using standard lab values:
- Sodium level: 140 Serum chloride: 100 Serum bicarbonate: 30
Using the equation:
Anion gap = 140 - (100 + 30) = 10
When the local normal range is around 8 to 12, this result would be interpreted as a normal anion gap. In the setting of metabolic alkalosis, that may point to a chloride-associated or volume-associated cause rather than a hidden acid load.
Consider a second example:
- Na: 140 Serum chloride: 94 Serum bicarbonate: 30
Anion gap = 140 - (94 + 30) = 16
This finding may fall into an elevated anion gap pattern depending on the lab’s reference interval. In a patient with metabolic alkalosis, that brings up the possibility of a complex acid-base disorder or another process such as elevated lactate that is changing the overall interpretation.
Drivers of Metabolic Alkalosis with Typical or Elevated Anion Gap
Several issues can result in metabolic alkalosis while the anion gap stays typical or turns unexpectedly increased. The primary practical causes include vomiting, diuretic use, and volume depletion. These can reduce chloride, change renal processing of bicarbonate, and produce a pattern that suggests alkalosis even when another issue is present.
Vomiting can result in loss of gastric acid, which elevates bicarbonate relative to chloride. Diuretic use often causes sodium and chloride loss, leading to contraction alkalosis and a distinctive electrolyte pattern. Volume depletion can even more intensify renal bicarbonate retention and create a strong compensatory response.
An elevated gap in a patient who seems alkalotic should require careful review for overlapping disorders. One important example is lactic acidosis, which can coexist with alkalosis and raise the combined gap. This is why the calculator should always be used as part of a larger clinical interpretation rather than as a standalone answer.
How to Adjust the Anion Gap for Albumin
Correction for albumin is crucial because albumin is a negatively charged protein that has a substantial effect to the unmeasured anion pool. When albumin is low, the measured anion gap may look misleadingly normal. This is especially important in patients with hypoalbuminemia, where the uncorrected number can miss the true acid burden.
Many clinicians use a corrected anion gap to improve laboratory interpretation. A common approach is to apply a specific amount for each gram per deciliter that albumin falls below normal, though the exact correction used can change by institution. The key point is that a corrected anion gap gives a more precise picture of the patient’s acid-base status.
For example, a patient with a borderline-normal value may actually have an elevated corrected result after adjustment for albumin. That corrected value can change the overall reading from simple metabolic alkalosis to a mixed acid-base disorder. This is why albumin should be reviewed alongside serum sodium, serum chloride, and serum bicarbonate whenever possible.
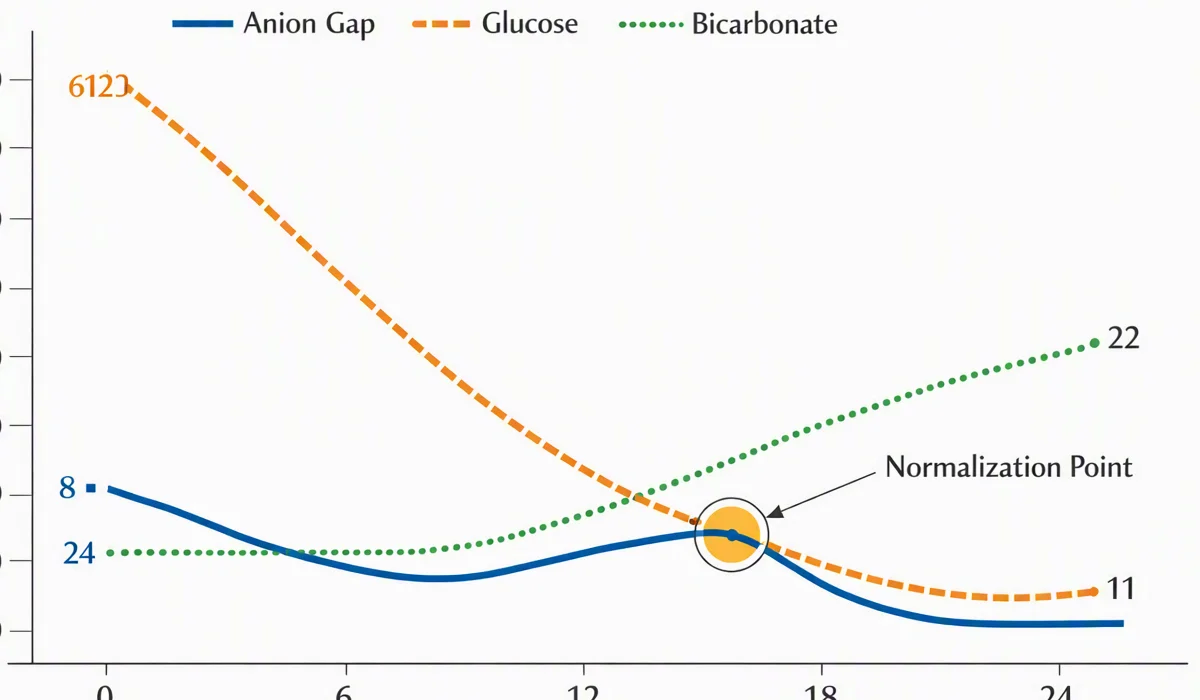
When an Anion Gap Calculator Is Most Useful
An anion gap calculator is most useful when a clinician requires rapid, structured clinical decision support from a blood chemistry panel. It is especially helpful when the lab pattern does not immediately make sense or when multiple processes may be occurring simultaneously.
Common scenarios include:
- Assessing an electrolyte panel in a patient with unclear bicarbonate changes Looking for hidden acid-base disorders in apparent metabolic alkalosis Tracking serial laboratory values during treatment Evaluating whether a corrected anion gap changes the interpretation Informing diagnosis when symptoms and labs do not match neatly
The tool is also valuable for documentation and communication. When the calculation is done in a consistent way, it provides a clear structure for discussing acid-base patterns with other clinicians. That consistency improves clinical interpretation and helps avoid overlooking a mixed disorder.
Limitations and Common Calculation Errors
Even a well-designed calculator has restrictions. Lab variability between instruments or facilities can shift the result slightly, and measurement error can affect sodium, chloride, or bicarbonate values enough to alter the final gap. Because the formula depends on small differences between numbers, even modest inconsistencies can matter.
Another major limitation is that the anion gap only estimates a portion of the body’s charged particles. It does not directly measure all acids or bases, and unmeasured anions may be present even when the value seems normal. That is why the result must always be considered in clinical context, not on its own.
Common calculation errors include entering the wrong units, using outdated values, or forgetting to apply albumin correction when indicated. Misreading the reference range is another recurring problem because different laboratories may use different reference intervals. A result that is normal in one setting may be slightly abnormal in another.
Finally, keep in mind that an anion gap is hardly a substitute for a full acid-base evaluation. It is one part of the larger puzzle that includes signs, medications, hydration status, and the overall pattern of serum electrolytes. If used well, it strengthens lab result analysis; when relied on alone, it can be misleading.
FAQ About Anion Gap and Metabolic Alkalosis
What does an anion gap calculator used for?
An anion gap calculator is meant to rapidly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. It helps with clinical interpretation of acid-base balance, detects possible electrolyte imbalance, and aids evaluation of metabolic alkalosis or metabolic acidosis. When albumin is included, it can also give a corrected anion gap for improved laboratory interpretation.
Can metabolic alkalosis affect the anion gap?
Yes. Metabolic alkalosis can be linked to a normal anion gap, and in some cases it may occur alongside an elevated anion gap if another disorder is present. The final reading depends on the clinical setting, albumin level, volume status, and whether there are unmeasured anions contributing to the result. That is why the anion gap calculator should be used as part of a broader acid-base disorder assessment.
How do you calculate the anion gap from lab values?
The most common anion gap formula is serum sodium minus the sum of serum chloride and serum bicarbonate. That is, sodium - (chloride + bicarbonate). This calculation uses values from an electrolyte panel or blood chemistry panel and is then compared with the reference range to determine whether the result is normal or elevated.
Why should albumin be used to correct the anion gap?
Albumin should be used because it is a key unmeasured anion. When albumin is low, especially in hypoalbuminemia, the uncorrected anion gap may look falsely normal. Albumin correction helps reveal the corrected anion gap, which provides better clinical interpretation and clearer lab result analysis.
What is the meaning of a normal or high anion gap mean in alkalosis?
A normal anion gap in metabolic alkalosis often suggests chloride loss, vomiting, diuretic use, or volume depletion. A raised anion gap may indicate that another process may also be present, such as lactic acidosis or another acid-base disorder. The key is to read the value with the patient’s clinical context, albumin level, and full blood test results rather than considering the number alone.