What Is the Anion Gap?
The anion gap is a computed value that helps healthcare providers gauge the acid-base balance using a routine electrolyte panel. It contrasts the main measured cations and negative ions in blood chemistry, especially sodium, chloride, and bicarbonate. Because not every ion is directly measured, the result provides a practical snapshot of the body’s overall acid-base balance.
In basic terms, the anion gap can be thought of as a laboratory clue. A unexpectedly high result may imply that acids are building up in the body, which can happen during critical illness. That is why clinicians often consider it as part of a larger laboratory assessment rather than as a isolated answer.
Albumin also is important because it is one of the major unmeasured anions in the blood. When albumin is low, the anion gap can appear decreased than expected, which may obscure a real problem. This is one reason clinical interpretation should always review the full serum chemistry picture instead of a single number.
How the Anion Gap Calculator Works
An Anion Gap Calculator uses common laboratory values to calculate the gap. In a simplest form, it usually uses Na, chloride, and bicarbonate. Some versions also include potassium, although many clinicians calculate it without potassium because the difference is usually small. The exact formula may differ a bit, but the goal is the same: to identify an abnormal calculated value that may suggest a metabolic derangement.
The calculator is only as accurate as the lab values entered. If the blood sample is old, incomplete, or affected by another condition, the output may be less useful. Still, as a screening tool, it can give a fast diagnostic clue when evaluating a patient with suspected acidosis.
A higher anion gap often suggests a drop in bicarbonate because acids are being buffered and bicarbonate is consumed. This can reflect a problem in acid-base balance, but the reason behind that change matters even more than the number itself. The calculator helps identify anion gap elevation, while the clinician decides what underlying cause best matches.
Common inputs used by the calculator include:
- Sodium measurement Chloride level Bicarbonate level Potassium level in some formulas Albumin for adjusted interpretation when needed
Can sepsis Increase the Anion Gap?
Yes. Sepsis can raise the anion gap, particularly when it leads to increased lactate and more general metabolic acidosis. The elevation often happens because profound infection can limit oxygen delivery at the tissue level, causing cells to shift toward abnormal metabolism and produce more acid. This is often tied to poor tissue perfusion, which means tissues are not getting enough blood flow to meet their metabolic needs.
Not each person with sepsis has a high anion gap, and not each high anion gap means sepsis. But in the right setting, an elevated gap can be an important severity marker. It may point toward a declining infection response, poor perfusion, or evolving critical illness that needs prompt attention.
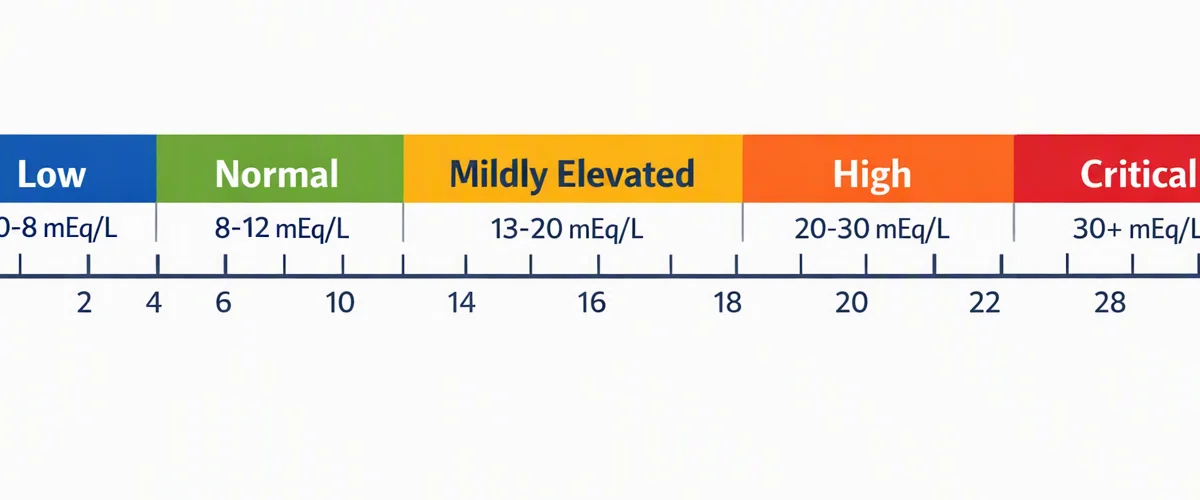
sepsis can also develop to shock and anion gap in chronic kidney disease organ failure, both of which can intensify metabolic problems. That is why the anion gap is best viewed as part of a wider clinical picture rather than a binary test for infection.
Why Sepsis May Lead To a High Anion Gap
One important cause is lactate. When oxygen delivery is reduced, cells rely more on anaerobic metabolism, which produces lactate as a byproduct. As lactate accumulates, it drives a high anion gap and a worsening acid-base state.
This process is especially common in shock, where poor circulation limits oxygen delivery. In sepsis, shock may develop because blood vessels dilate, fluid shifts out of the circulation, and the heart and organs struggle to maintain perfusion. The result is greater lactate accumulation and a stronger signal of metabolic stress.
Another key factor is organ dysfunction. The liver helps clear lactate, and the kidneys help manage acid-base balance. If either system is impaired during sepsis, the body may not remove acids efficiently, which can further increase the anion gap. This is why a rising gap can sometimes reflect both increased acid production and decreased clearance.
From a practical standpoint, the anion gap often changes because sepsis creates a chain reaction: infection leads to poor perfusion, poor perfusion leads to anaerobic metabolism, and anaerobic metabolism leads to acid buildup. That sequence is one reason clinicians track the anion gap along with lactate and other markers.
Other Reasons of a High Anion Gap
Sepsis is only a single cause of a high anion gap. A number of other issues can produce comparable laboratory findings, and each one has a different root cause and therapy strategy.
Ketoacidosis is a common reason, most notably diabetic ketoacidosis. In this condition, the body metabolizes fat for fuel and produces ketone acids. This can markedly decrease bicarbonate and raise the anion gap.
Renal failure is another important cause. When the kidneys cannot eliminate acids efficiently, waste products and unmeasured acids collect in the blood. Related to this is uremia, where retained metabolic waste results in a raised anion gap and metabolic acidosis.
Toxin exposures can also cause a significant rise in the gap. Substances such as methanol, ethylene glycol, or salicylates may alter acid-base balance and produce dangerous metabolic abnormalities. In these cases, the anion gap is a helpful clue, but it must be matched with history, symptoms, and specific anion gap methanol case testing.
Because the same lab pattern can come from several different problems, a high anion gap should never be interpreted in isolation. The clinical context determines whether the result points toward infection, kidney failure, ketoacidosis, poisoning, or another cause.
When a Normal Anion Gap Does Doesn't Eliminate Sepsis
A standard anion gap does not eliminate sepsis. This is particularly true in beginning sepsis, when the infection process has started but tissue injury and acid build-up are still not severe enough to change the calculated value. A patient may still be critically unwell even if the gap appears normal on the first set of labs.
Albumin can also influence interpretation. Low albumin may artificially lower the measured gap, masking a real acid-base problem. If albumin is reduced, the apparent result may underestimate the true severity of the metabolic disorder.
In addition, sepsis can involve overlapping acid-base disturbances. For example, a person may have metabolic acidosis from lactate and also have vomiting or respiratory changes that offset the expected pattern. In those situations, the anion gap alone may look normal or only mildly elevated even when serious illness is present.
That is why a normal result should be read as “not clearly abnormal,” not “sepsis is excluded.” The patient’s symptoms, exam findings, and other tests are much more important than a single number.
How Providers Interpret Anion Gap in Sepsis
Doctors interpret the anion gap in sepsis as part of a larger assessment. They frequently compare it with the arterial blood gas, serum lactate, and base deficit to understand how severe the acidosis is and whether the body is compensating adequately.
The arterial blood gas shows the pH, carbon dioxide level, and bicarbonate level. Serum lactate gives a direct measure of lactate burden, which can support the suspicion of poor perfusion. Base deficit offers another way to estimate the degree of metabolic acidosis and can be useful in tracking changes over time.
Clinical interpretation depends on the full picture: blood pressure, mental status, urine output, breathing pattern, infection source, and response to treatment. A single high anion gap may suggest the idea of sepsis-related lactic acidosis, but it does not confirm the diagnosis by itself.
In practice, a rising gap along with rising lactate, worsening hypotension, and other signs of instability may indicate that treatment needs to be escalated quickly. The number becomes most useful when it tracks with the patient’s condition rather than standing alone as an isolated lab result.
When to Seek Urgent Medical Care
Seek immediate medical attention if a fever is paired with symptoms that suggest serious infection or worsening illness. Warning signs include confusion, rapid breathing, and low blood pressure, especially if they appear suddenly or are getting worse. These can be signs of sepsis or shock and need immediate evaluation.
Other concerning symptoms can include severe weakness, a fast heartbeat, decreased urination, or trouble staying awake. If an infection seems to be spreading and the person looks sicker rather than better, the situation should be treated as urgent.
A high anion gap on its own is not always an emergency, but if it appears alongside symptoms of critical illness, it should be taken seriously. Prompt care can help identify the underlying cause, whether that is sepsis, ketoacidosis, renal failure, or toxic ingestion.
Common Questions
Can sepsis result in a high anion gap?
Yes. Sepsis can cause a high anion gap, most often through lactic acidosis from tissue hypoperfusion and anaerobic metabolism. The result may reflect worsening metabolic acidosis and can act as a clue to serious illness.
Can a normal anion gap exclude sepsis?
No. A normal anion gap does not rule out sepsis. Early sepsis, low albumin, or mixed acid-base disorders can make the value look normal even when the patient is quite ill.
Why does lactate increase in sepsis?
Lactate increases in sepsis because poor perfusion and shock can push cells toward anaerobic metabolism. When oxygen delivery is limited, lactate accumulates and may contribute to a high anion gap and metabolic acidosis.
Is the anion gap identical to lactate?
No. The anion gap is a calculated value from electrolytes, while lactate is a measured substance in the blood. High lactate can raise the anion gap, but the two tests are not identical and should be interpreted separately.
When is a high anion gap an emergency?
A high anion gap should be treated as an emergency when it occurs with fever, confusion, rapid breathing, low blood pressure, or other signs of critical illness. Those findings may suggest sepsis, shock, or another dangerous cause of metabolic acidosis that needs immediate care.