What Is Alcoholic Ketoacidosis?
Alcoholic ketoacidosis represents a form of ketoacidosis that typically develops after heavy alcohol use combined with reduced food intake, vomiting, and dehydration. It acts as a metabolic emergency because it can produce a significant metabolic acidosis with a high anion gap, meaning there is an excess of unmeasured acids in the blood.
The condition often develops after a period of binge drinking followed by poor oral intake. During that time, the body’s carbohydrate stores drop, stress hormones surge, and ketone production rises. As ethanol metabolism affects liver chemistry and energy use, the body shifts toward using fat as fuel. This leads to accumulation of ketone bodies, especially beta-hydroxybutyrate and acetoacetate, which drive an acidotic state.
Vomiting, reduced intake, and ongoing alcohol use can also result in dehydration and volume depletion. Those factors aggravate the acid-base imbalance by reducing kidney perfusion and limiting the body’s ability to clear acids. The result is often a mixed metabolic derangement that needs careful diagnostic evaluation using lab values rather than symptoms alone.
Although the term may sound similar to diabetic emergencies, alcoholic ketoacidosis has its own pattern. It commonly involves low or normal glucose, marked ketosis, and a high anion gap. In practice, the condition is recognized through serum chemistry, an electrolyte panel, and a blood gas that together show the severity of the acid-base disturbance.
Why Is the Anion Gap Increased in Alcoholic Ketoacidosis?
The anion gap goes up because alcoholic ketoacidosis elevates the concentration of uncounted acids in the blood. The classic formula evaluates measured cations and anions in routine chemistry: sodium minus chloride and bicarbonate. When acids accumulate, especially organic acids, the bicarbonate level drops as it buffers the acid load. That drop contributes to metabolic acidosis and causes of low anion gap a higher gap.
In alcoholic ketoacidosis, the main drivers are ketone bodies and often lactate. Beta-hydroxybutyrate and acetoacetate are organic acids. As they build up, they generate hydrogen ions, which consume bicarbonate. The body responds with compensatory respiration, often causing rapid or accelerated breathing as it tries to reduce carbon dioxide and partially correct the acid-base balance.
Several mechanisms can drive the gap higher:
- Enhanced ketone production from low carbohydrate availability Higher lactate from poor tissue perfusion and altered metabolism Reduced renal clearance of acids during dehydration Ongoing volume depletion that intensifies the metabolic derangement
It is important to remember that the anion gap is not just a number; it is a indicator to the underlying cause. In this setting, it reflects an increase in unmeasured acids, not a direct measurement of ketones. That is why the anion gap helps identify high anion gap metabolic acidosis but does not by itself prove alcoholic ketoacidosis.
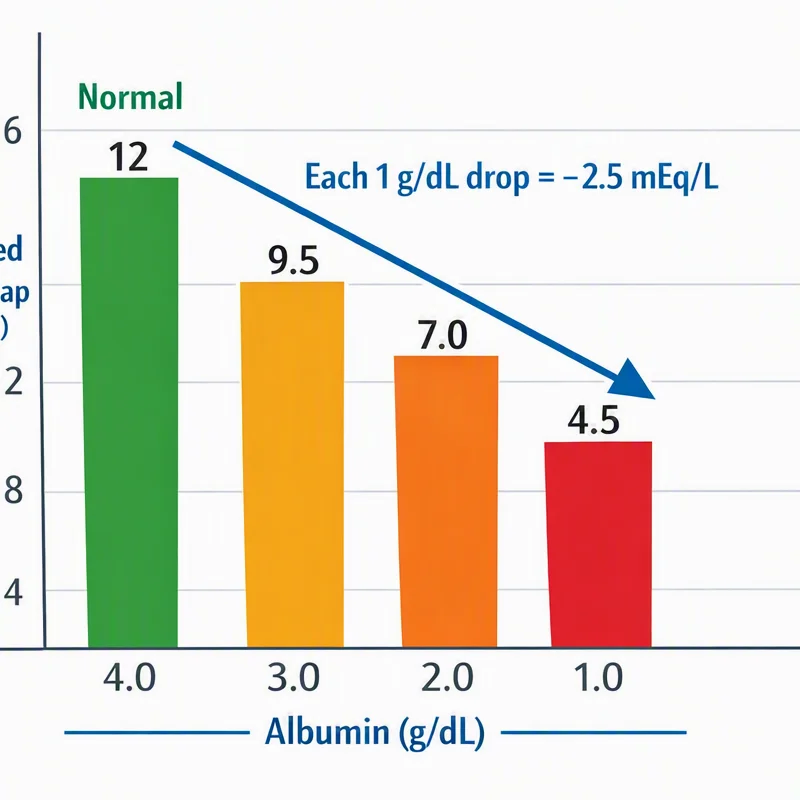
Serum albumin also matters. Because serum albumin is a major unmeasured anion, low albumin can make the gap look less increased than it truly is. In clinical interpretation, an albumin-corrected gap can improve accuracy. This is especially useful when the presentation is complex or when multiple causes of acidosis may be present at once.
How to Interpret an Anion Gap Calculator Result
An Anion Gap Calculator is a practical tool for quick anion gap calculation using core chemistry values. Most calculators use serum sodium, serum chloride, and serum bicarbonate. Some versions also allow modification for serum albumin, which improves clinical interpretation when albumin is low.
The basic idea is clear: if sodium is measured and chloride plus bicarbonate are relatively high compared with it, the gap is smaller. If chloride and bicarbonate are not enough to account for sodium, the gap increases. In alcoholic ketoacidosis, the gap is usually elevated because bicarbonate is consumed by acids from ketone bodies and lactate.
When reading calculator results, look at three questions:
- Is the gap elevated enough to suggest high anion gap physiology? Do the accompanying lab values support metabolic acidosis? Does the overall pattern fit an alcohol-related acidotic state or another differential diagnosis?
The Anion Gap Calculator is most useful when paired with other lab values. A high result should prompt review of the full electrolyte panel, kidney function, glucose, and acid-base status. If bicarbonate is low and the blood gas confirms acidemia, the finding supports a true metabolic acidosis rather than a laboratory artifact.
For practical use, a calculator can also help with severity assessment. A larger gap generally suggests a bigger burden of unmeasured acids, though the number alone does not reveal the exact cause. In alcoholic ketoacidosis, the result should be interpreted alongside symptoms such as vomiting, poor intake, tremor, tachypnea, and dehydration.
What Lab Values Typically Accompany Alcoholic Ketoacidosis?
Alcoholic ketoacidosis infrequently presents as an isolated lab abnormality. It typically comes with a recognizable cluster of shifts in electrolytes, acid-base markers, and metabolic readings. The most helpful indicators include elevated beta-hydroxybutyrate, variable glucose, low bicarbonate, and a blood gas showing acidemia or partial compensation.
Beta-hydroxybutyrate is commonly the dominant ketone body in this condition, occasionally more prominent than acetoacetate. Since standard urine ketone tests may miss beta-hydroxybutyrate, a patient can have significant ketosis even when bedside ketone testing seems modest. That is a major reason serum measurement is so helpful in a thoughtful diagnostic evaluation.
Glucose is often normal or low, though it can vary. This differs from many cases of diabetic emergencies, where hyperglycemia is more typical. A low or normal glucose with a high anion gap and ketosis should raise suspicion for alcoholic ketoacidosis, especially in the setting of vomiting and poor oral intake.
Typical laboratory features include:
- Low serum bicarbonate High beta-hydroxybutyrate Altered electrolytes, particularly potassium, magnesium, and phosphate Variable glucose, often normal or low Blood gas signs of metabolic acidosis Increased anion gap
The blood gas is used determine whether the patient is acidemic and whether respiratory compensation is appropriate. At the same time, a chemistry panel shows the acid-base balance at the metabolic level. When these are interpreted together, the full picture often reveals a clear metabolic derangement driven by ketosis, poor intake, and alcohol-related physiology.
It is also common to see mixed abnormalities from vomiting and dehydration. A patient may have low chloride from vomiting and a high gap from organic acids. This mixture can complicate interpretation, which is why a broad serum chemistry review is essential.
How Is Alcoholic Ketoacidosis Different Than Diabetic Ketoacidosis?
Alcohol-related ketoacidosis and DKA share several features: both cause ketosis, both can produce a elevated anion gap metabolic acidosis, and both involve accumulation of acid from ketone bodies. Still, the underlying physiology differs in several important ways.
In diabetic ketoacidosis, the main problem is insulin deficiency. Without enough insulin, the body cannot use glucose effectively, so fat breakdown accelerates and ketones rise. This often leads to marked hyperglycemia. In alcoholic ketoacidosis, by contrast, glucose is frequently normal or low, and the trigger is usually poor intake, vomiting, and recent heavy ethanol use rather than classic insulin deficiency.
That said, some overlap exists. Stress hormones, dehydration, and starvation-like physiology can all promote ketone production. The key difference is that alcoholic ketoacidosis tends to occur after a period of alcohol intake followed by reduced nutrition, while diabetic ketoacidosis is primarily tied to inadequate insulin action.
Typical distinctions include:
- Diabetic ketoacidosis: usually marked hyperglycemia, clear insulin deficiency, and ketosis Alcoholic ketoacidosis: often normal or low glucose, poor oral intake, vomiting, and recent ethanol exposure Both: elevated anion gap, low bicarbonate, and ketone-related metabolic acidosis
Because the treatments differ, distinguishing the two matters. Giving insulin to a patient with alcoholic ketoacidosis and normal glucose may worsen hypoglycemia. Conversely, missing diabetic ketoacidosis delays needed insulin and fluid therapy. Careful review of glucose, ketones, acid-base status, and the clinical history is essential.
When Is a High Anion Gap Serious?
A high anion gap becomes critical when it reflects a serious or rapidly worsening acid-base disturbance. The number itself is a signal, but the real concern is the root cause. In alcoholic ketoacidosis, a high gap can worsen quickly if dehydration, vomiting, or continued alcohol use continues. If the cause is something more serious, such as toxic alcohols, uremia, sepsis, or shock, urgent intervention is vital.
Toxic alcohols such as methanol or ethylene glycol can create severe high anion gap metabolic acidosis and require prompt recognition. Uremia from kidney failure can also raise the gap by allowing acids to accumulate. In sepsis and shock, poor tissue perfusion increases lactate, leading to lactic acidosis and deepening acid-base imbalance.
Warning signs that a high gap may be dangerous include altered mental status, severe tachypnea, hemodynamic instability, persistent vomiting, refractory electrolyte abnormalities, and very low bicarbonate. A blood gas and full serum chemistry profile are useful for determining how severe the metabolic acidosis is and whether the patient is compensating correctly.
When evaluating a patient, do not assume alcoholic ketoacidosis is the only explanation. A high anion gap should trigger a wide differential diagnosis. The goal is to identify the underlying cause while assessing for severity and complications.
Frequent Causes of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis has many etiologies, and alcoholic ketoacidosis is only one of them. A classic mnemonic is MUDPILES, which is commonly used to structure the diagnostic list. While mnemonics are inexact, they remain helpful for reviewing common sources.
Major causes include:
- MUDPILES items such as poisonings, lactic acid accumulation, and ketosis Renal failure, which leads to retention of acids and reduced elimination Salicylates, which can cause a mixed acid-base disorder Starvation ketosis, which occurs with sustained insufficient intake Toxic alcohols, including methanol and ethylene glycol Lactate-related acidosis from sepsis or shock
Starvation ketosis can look similar to alcoholic ketoacidosis because both involve limited intake and ketone formation. The difference is that alcoholic ketoacidosis usually follows heavy ethanol use and often produces a more pronounced metabolic disturbance. Still, the similarity is real, and the clinical picture is essential.
Renal failure and salicylates can confound the picture by introducing additional acids or mixed respiratory effects. This is why a close review of the electrolyte panel, blood gas, kidney function, and medication history is part of every good acid-base workup. The anion gap should lead the clinician toward the next diagnostic step, not substitute for it.
Frequently Asked Questions About the Anion Gap in Alcoholic Ketoacidosis
What’s a normal anion gap in alcoholic ketoacidosis?
During alcoholic ketoacidosis, the anion gap typically rises rather than normal because ketone bodies and sometimes lactate accumulate and cause metabolic acidosis. A truly normal gap would be less typical and should prompt review of the diagnosis, review of serum albumin, and evaluation for mixed disorders or other causes of acidosis. The exact reference range can differ by laboratory and by whether albumin correction is used.
Why does alcoholic ketoacidosis cause a high anion gap?
It causes a high anion gap because the body accumulates extra organic acids, especially ketone bodies such as beta-hydroxybutyrate and acetoacetate, along with possible lactate. These acids consume bicarbonate, lowering serum bicarbonate and creating high anion gap metabolic acidosis. Dehydration, vomiting, and poor oral intake often magnify the process.
Can alcoholic ketoacidosis happen with normal glucose?
Yes. Glucose in alcoholic ketoacidosis is often normal or low, unlike the typical picture of diabetic ketoacidosis. That is why normal glucose does not rule out serious ketosis or metabolic acidosis. If the history includes ethanol use, vomiting, and poor oral intake, a normal glucose level can still fit alcoholic ketoacidosis.
In what way does an Anion Gap Calculator help identify metabolic acidosis?
An Anion Gap Calculator helps by using routine serum chemistry values into a fast estimate of the gap using serum sodium, serum chloride, and serum bicarbonate. A high result supports anion gap calculation findings consistent with metabolic acidosis. It is most useful when paired with a blood gas, electrolytes, glucose, and clinical context for accurate clinical interpretation.
What additional conditions may cause a high anion gap besides alcoholic ketoacidosis?
Additional causes include toxic spirits, renal failure, aspirin-related compounds, systemic infection, circulatory shock, lactic acid accumulation, and fasting ketosis. They may also lead to a raised anion gap by increasing unmeasured acids or reducing acid clearance. Due to this extensive range of diagnoses, a high gap should trigger a careful search for the root cause.