What the Anion Gap Shows
The anion gap is a computed value from routine electrolytes that helps clinicians interpret acid-base balance. It is commonly derived from serum sodium, serum chloride, and serum bicarbonate, and it provides a practical clue to hidden acids in the blood. In simple terms, the anion gap calculation balances measured positively charged and negatively charged ions in serum chemistry to estimate whether unmeasured anions are accumulating.
This is where an anion gap calculator becomes useful. By efficiently organizing the laboratory values, it can aid faster recognition of a metabolic derangement. The result does not diagnose a condition by itself, but it can function as a diagnostic marker that points toward an acidotic state and helps narrow the differential diagnosis.
The anion gap is especially Helpful site important because many serious illnesses alter acid-base balance before the full clinical picture is obvious. In critical care, a shifting anion gap may reflect worsening perfusion, evolving organ dysfunction, or a response to resuscitation. The number should always be interpreted in clinical context, not as an isolated lab result.
Why the Anion Gap Matters in Shock
Shock is a situation of poor perfusion and limited oxygen delivery to tissues. When tissues do not get enough oxygen, they turn toward anaerobic metabolism, which promotes lactate accumulation and can result in lactic acidosis. This process often causes metabolic acidosis with an elevated anion gap.
The connection between shock and the anion gap is clinically important because shock is not one single disease. Hypovolemic shock, cardiogenic shock, obstructive shock, and distributive shock can all lead to hemodynamic instability, but through different mechanisms. Despite those differences, they may each cause tissue hypoperfusion and elevated lactate if oxygen delivery is inadequate.
In sepsis, the problem may include both impaired perfusion and abnormal cellular metabolism. In ischemia, tissues are directly deprived of blood flow. In either case, the anion gap can act as a bedside clue that the body is under metabolic stress. A rising gap often indicates that the acid-base problem is more than simple dehydration or isolated electrolyte loss.
That said, the anion gap is not a perfect severity score. It is part of the broader picture that includes blood pressure, mental status, urine output, lactate, and response to resuscitation. Used well, it aids identify the biochemical footprint of shock and supports ongoing reassessment.
How to Determine the Anion Gap
Many clinicians determine the anion gap from serum sodium, serum chloride, and serum bicarbonate. An anion gap calculator can simplify the math and limit transcription errors during urgent decision-making. The usual formula is:
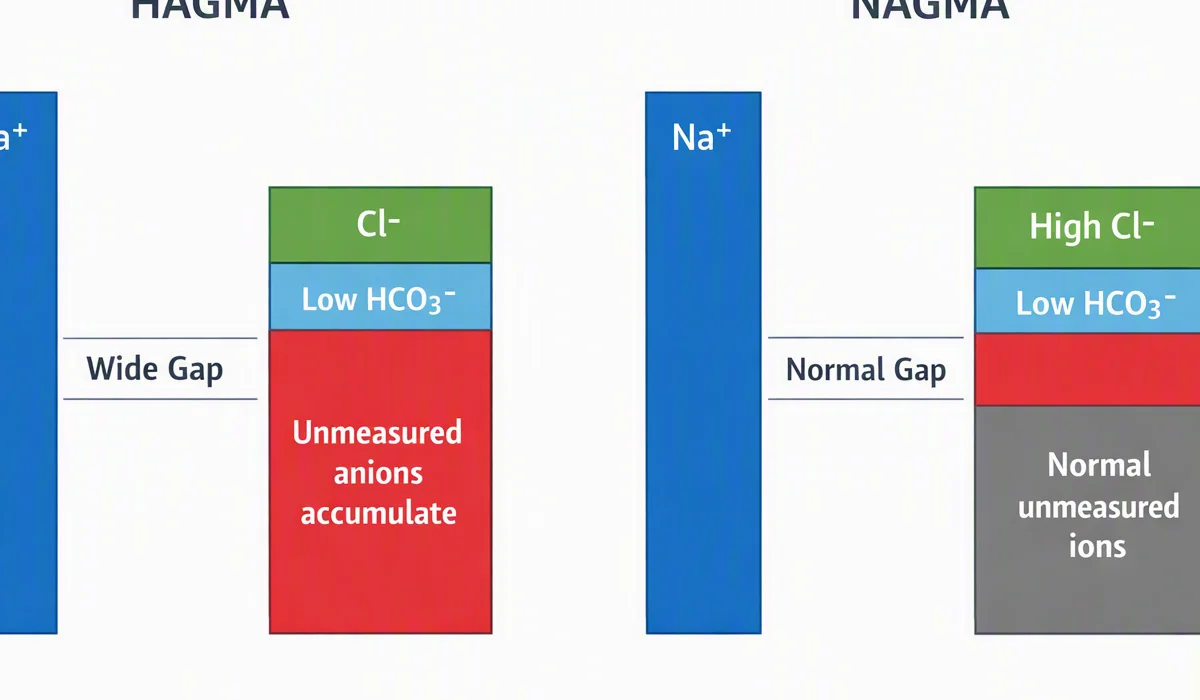
anion gap = sodium − (chloride + bicarbonate)Because albumin is a key unmeasured anion, low albumin can make the gap appear spuriously normal or only mildly elevated. That is why albumin correction is important. A low measured gap may mask a true acid burden unless the corrected anion gap is calculated.
For many clinicians, the corrected value is more useful than the raw number in critically ill patients. If albumin is low, the correction can reveal a more accurate picture of acid-base status and support faster recognition of high anion gap metabolic acidosis. This is especially useful in patients with critical illness, fluid shifts, inflammation, or prolonged hospitalization.
The anion gap should also be interpreted with serum bicarbonate. A low bicarbonate level supports metabolic acidosis, but the gap determines whether the acidosis is likely due to unmeasured acids such as lactate, ketones, or toxins. In other words, the calculator is not just a simple calculator; it is a way to connect serum chemistry to the pathophysiology of illness.
Reasons of a High Anion Gap in Circulatory failure
A high anion gap in shock usually means hidden acids are accumulating. The most common cause is lactate. When perfusion is poor, cells generate energy through anaerobic pathways, and lactate rises. This is the characteristic pattern in lactic acidosis, especially when shock is ongoing or advanced.
Sepsis is a common setting for raised lactate and a elevated anion gap. In septic shock, inflammatory mediators, microcirculatory dysfunction, and mitochondrial abnormalities may drive lactate elevation even when blood pressure is being stabilized. The anion gap can help confirm that the patient is experiencing metabolic stress, not just hypotension.
Ischemia from bowel compromise, limb ischemia, or other low-flow states can also raise the gap. In these cases, the source of acid generation may be localized tissue injury, but the systemic laboratory pattern can still signal a critical process. The combination of increasing gap and progressive symptoms should prompt urgent evaluation.
Toxic ingestions are another important consideration. Toxic alcohols such as methanol and ethylene glycol can lead to high anion gap metabolic acidosis and may coexist with shock-like physiology or organ dysfunction. They should remain on the differential diagnosis, especially when the clinical story does not fully fit perfusion failure alone.
Other contributors may include renal dysfunction, ketoacidosis, or mixed acid-base disorders, but in a patient with shock the first concern is often whether rising lactate reflects inadequate resuscitation anion gap in chronic kidney disease or ongoing tissue hypoperfusion. The pattern should always be paired with hemodynamic data and repeat laboratory values.
Typical Anion Gap Doesn't Rule Out Shock
A normal anion gap does not exclude shock. At the start of illness, the acid-base picture may still seem deceptively mild. This is particularly true in early shock, as tissue hypoperfusion develops but lactate has not yet climbed significantly or has not yet been checked at the right time.
Shock can likewise appear with normal anion gap metabolic acidosis. For example, giving chloride-rich fluids may lead to hyperchloremia and a non-anion-gap acidosis. In that situation, the patient can stay critically ill even though the anion gap is not elevated. The acid-base pattern can change as treatment progresses, so trend analysis matters.
An arterial blood gas can provide extra context by revealing pH, bicarbonate estimate, and respiratory compensation. However, a normal or near-normal pH on blood gas does not rule out a serious process if compensation is masking the underlying disorder. The anion gap and the arterial blood gas should be interpreted together rather than in isolation.
For this reason, a normal gap should not reassure clinicians when the bedside picture points to low perfusion, altered mental status, oliguria, or increasing vasopressor needs. Shock is fundamentally a problem of oxygen delivery and organ dysfunction, and the laboratory pattern may lag behind the physiology.
Interpreting the Result in Context
The anion gap is most valuable when it is interpreted with the full bedside picture: blood gas, vital signs, urine output, mental status, and overall clinical assessment. A single number cannot distinguish every cause of metabolic acidosis, but it can raise concern for a specific process when the clinical pattern fits.
Base deficit is another useful marker here. A more negative base deficit often suggests a greater metabolic acid load and can support concern for shock-related hypoperfusion. When combined with lactate, base deficit may help characterize the severity of the metabolic abnormality and the patient’s response to resuscitation.
Albumin correction is especially important in critical illness because low albumin can mask a clinically meaningful gap. In a patient with low albumin and borderline results, the corrected anion gap may reclassify the acid-base disorder and reveal an occult high anion gap metabolic acidosis. This matters for both diagnosis and treatment planning.
It is also helpful to think in terms of pattern recognition. A rising gap with worsening lactate suggests ongoing anaerobic metabolism or a new source of acid. A stable gap with normal lactate but persistent acidosis may indicate another mechanism, such as renal dysfunction or hyperchloremia. This type of interpretive flexibility is part of good critical care practice.
Ultimately, the anion gap should support, not replace, clinical judgment. It is best viewed as a dynamic marker that tracks changing physiology during resuscitation, especially when paired with serial laboratory values and hemodynamic monitoring.
When to Recheck Labs and Escalate Care
When shock is present, repeat testing should be based on the patient’s condition and the treatment response. If there is continued hemodynamic instability, worsening acidosis, or concern for inadequate perfusion, repeat labs are indicated. Rechecking the anion gap, bicarbonate, lactate, and related electrolytes helps determine whether resuscitation is effective.
Lactate trend is particularly useful. A decreasing lactate generally suggests improving perfusion and improved oxygen delivery, while a continuously high or rising lactate can signal unresolved shock, ongoing ischemia, or a unrecognized condition. The anion gap often moves in parallel, though not perfectly, so trend analysis should include both.
Escalation to critical care is recommended when the clinical picture shows progressive organ dysfunction, increasing vasopressor requirements, refractory acidosis, or concern for toxic alcohols, sepsis, or ischemia. The combination of high anion gap metabolic acidosis, rising lactate, and worsening hemodynamics should prompt urgent reassessment of source control, perfusion, and underlying cause.
Close monitoring often includes serial serum chemistry panels, repeat blood gas testing, and careful bedside reassessment after fluids, vasopressors, or other interventions. The goal is not to target a single value, but to verify that resuscitation is restoring perfusion and reversing the metabolic consequences of shock.
Common Questions
What is the anion gap in shock?
The anion gap in shock is a calculated laboratory value that helps identify metabolic acidosis caused by unmeasured acids, most often lactate. When shock is present, it can be a helpful sign that tissue hypoperfusion is limiting oxygen delivery and promoting anaerobic metabolism. It should be interpreted alongside blood pressure, lactate, blood gas results, and the overall clinical picture.
Why can shock lead to a high anion gap?
Shock can result in a high anion gap because reduced perfusion leads to lactate build-up and lactic acidosis. When tissues do not receive adequate oxygen, they produce more acid through anaerobic metabolism. Sepsis, ischemia, and severe hemodynamic instability can all result in this pattern.
Can shock occur with a normal anion gap?
Yes. Shock can present with a regular anion gap, especially in early shock or when the patient has hyperchloremic metabolic acidosis from hyperchloremia or fluid administration. A regular gap does not rule out serious hypoperfusion, so arterial blood gas results, lactate, and clinical assessment remain essential.
How does albumin affect the anion gap?
Albumin level is a major unspecified anion, so reduced albumin can depress the observed anion gap and cause a true acid-base disorder look less obvious. Because of this albumin correction is essential. The corrected anion gap may uncover a hidden high anion gap metabolic acidosis in severely ill patients.
How often should the anion gap and lactate be rechecked in shock?
The schedule depends on the severity of the condition and the response to emergency treatment. When patients are unstable, repeat laboratory tests are often necessary after treatment changes and at routine intervals to follow the lactate trend and electrolyte changes. In intensive care, the goal is serial assessment until perfusion gets better and the metabolic abnormalities begin to resolve.