What Is a Anion Gap Test?
An anion gap test is a straightforward way to assist to evaluate acid-base disorders by examining the relationship among common electrolytes in a lab sample. The calculation usually uses sodium, chloride, and bicarbonate, which are part of a standard blood chemistry panel. Clinicians use it to identify whether there may be hidden acids in the blood that are not obvious from the basic electrolyte values alone.
The anion gap is not a diagnosis by itself. It is a diagnostic clue that helps guide a metabolic evaluation when the patient may have metabolic acidosis or another unexplained abnormality in acid-base balance. Because the test is derived from routine lab values, it is often available quickly and can be paired with other studies such as serum electrolytes, renal function testing, and blood gas analysis.
In practical terms, the anion gap helps answer a focused question: is there an accumulation of unmeasured acids, or is the problem better explained by a different pattern of electrolyte change? That distinction can shape the next step in the diagnostic workup.
How Does the Anion Gap Calculator Operate?
An anion gap calculator performs the calculation rapidly and decreases the chance of arithmetic mistakes during laboratory interpretation. It typically uses the measured bicarbonate and other serum electrolytes to estimate the gap between positively charged and negatively charged ions in the blood. In everyday use, the calculator helps clinicians determine whether the result falls within the expected reference range or points to anion gap elevation.
Many calculators also include albumin, because low albumin can lead to the gap appear lower than it truly is. This is where the albumin-corrected anion gap becomes important. Albumin is a major unmeasured anion, so when it is reduced, the uncorrected number may miss the degree of acid retention. Correcting for albumin improves accuracy, especially in hospitalized patients or those with critical illness.
The calculator is most helpful when the result is interpreted alongside the clinical picture. A mildly abnormal number may not matter much in a stable patient, but it can be a major clue in someone with unexplained acidosis, altered mental status, or signs of shock. In that setting, the anion gap calculator is less of a standalone tool and more of a decision aid that helps with faster recognition of serious illness.
It is also helpful to remember that the anion gap reflects the difference between measured ions, not a direct count of acids. As a result, changes in bicarbonate, chloride, or sodium can affect the number. That is why careful interpretation matters more than simply reading the result as high or normal.
When Should You Need an Anion Gap Test?
The main reason to obtain an anion gap test is to check metabolic acidosis. If a patient has low bicarbonate on a chemistry panel, the next question is whether the cause is a elevated anion gap process or a standard gap process. That distinction can help narrow the differential diagnosis promptly and can shape urgent treatment.
Requesting the test is especially useful when the cause of acidosis is not obvious from the initial blood chemistry panel. If there is unexplained acidosis, the anion gap can show whether the body is building up acids such as lactate, ketones, or toxins. In other words, the test is not only about confirming that acidosis exists; it is about identifying the probable category of the disorder.
It is also recommended when a patient has symptoms or lab findings that suggest a wider metabolic or systemic problem. For example, confusion, dehydration, rapid breathing, hypotension, or worsening renal function may all point toward an acid-base disturbance. In those situations, the anion gap helps prioritize the diagnostic workup and can prompt faster evaluation for severe causes.
Clinicians may order it in suspected acid-base disorders whenever the clinical context raises concern for hidden acids or for bicarbonate loss. That means it can be useful in the emergency setting, inpatient care, and some outpatient evaluations when the presentation suggests a serious metabolic problem.
Red Flags That Prompt Testing
Several situations should raise concern for a serious metabolic problem and prompt immediate testing. Lactic acidosis is one of the most important examples. It can occur when tissues are underperfused or when oxygen delivery is impaired, and it often appears in severe infection, shock, or respiratory compromise. A high anion CKD high anion gap metabolic acidosis gap can be a important clue that lactate is building up even before the exact cause is confirmed.
Ketoacidosis is another major indication. This may be seen with diabetic illness, prolonged fasting, alcohol use, or other states of severe carbohydrate deficiency. In these cases, the anion gap helps reveal the accumulation of ketoacids and supports urgent treatment decisions.
Sepsis is also a classic trigger for ordering the test because it can cause both lactic acidosis and multi-organ stress. In critical illness, the anion gap may provide an early warning that the metabolic state is deteriorating. Similarly, kidney failure can reduce acid excretion and lead to worsening acidosis, making the test useful when renal dysfunction is part of the presentation.
Other red flags include rapid breathing, vomiting, altered mental status, toxic exposure, or a sudden decline in overall condition. In those circumstances, the anion gap is part of a focused evaluation for life-threatening metabolic disturbance rather than a routine screening value.
Routine vs. Targeted Ordering
Some clinicians review the anion gap automatically whenever they review serum electrolytes, while others use a more targeted method. A routine approach can be helpful because it may identify early abnormalities that would otherwise be missed. However, overuse without context can create noise, especially when small changes fall within normal variation or reflect shifts in albumin rather than true pathology.
A targeted strategy is often more efficient. If the patient has clinical suspicion for metabolic derangement, then ordering the test as part of the diagnostic workup makes sense. This is especially true when a venous blood gas or arterial blood gas shows low bicarbonate or acidemia. Those gas results can confirm the acid-base disturbance, while the anion gap helps classify it.
In practice, the best use of the test is often selective rather than automatic. It is most valuable when it will change interpretation, sharpen the differential, or support a more urgent response. That means the anion gap is best viewed as a problem-solving tool, not a universal screening test for every patient.
What Is a Increased Anion Gap Indicate?
A raised result points to high anion gap metabolic acidosis, which often means that unmeasured acids have accumulated in the blood. These acids may include lactate, ketones, or other organic substances that are not directly captured in the basic lab panel. The increase shows that the body’s acid load has risen or that acid clearance has dropped.
Common causes include organic acids from lactic acidosis or ketoacidosis, impaired acid elimination in kidney disease, and toxin exposure. A high reading can be especially important in patients with sudden changes in mental status or unexplained hemodynamic instability because it may point toward an urgent underlying process.
Toxic alcohol use is among the classic concerns when the anion gap is high. Methanol, ethylene glycol, and related substances can generate acid metabolites that produce severe metabolic derangement. Under these circumstances, the anion gap may be one of the first available clues before confirmatory testing returns.
Salicylate overdose can also produce complex acid-base findings, sometimes with a mixed pattern. The anion gap may be elevated, but the overall interpretation should be integrated with symptoms, blood gas results, and exposure history. A raised value does not establish poisoning, but it should increase clinical suspicion when the story fits.
Since high anion gap disorders can progress quickly, the result should trigger a search for the cause rather than reassurance. The question becomes: what acid is accumulating, why is it happening, and how urgently does it need treatment?
What Does a Normal Anion Gap Mean?
A within-range result does not rule out acidosis. It may point to normal anion gap metabolic acidosis, which usually shows bicarbonate depletion with a adaptive increase in chloride. This pattern is often called hyperchloremic acidosis because the chloride level rises as bicarbonate falls, keeping the gap from widening dramatically.
Renal tubular acidosis is an important cause of this pattern. In such cases, the kidneys have problems handling acid or bicarbonate normally, and the anion gap in chronic kidney disease patient may have a persistent acid-base problem despite a normal gap. The diagnosis often needs a more comprehensive metabolic evaluation and attention to renal function, urinary findings, and overall electrolyte pattern.
Because chloride shifts are crucial here, the result can seem deceptively reassuring if only the total gap is considered. The patient may still have clinically important acidosis even when the number is not elevated. That is why the anion gap must be interpreted together with bicarbonate, chloride, and the clinical picture.
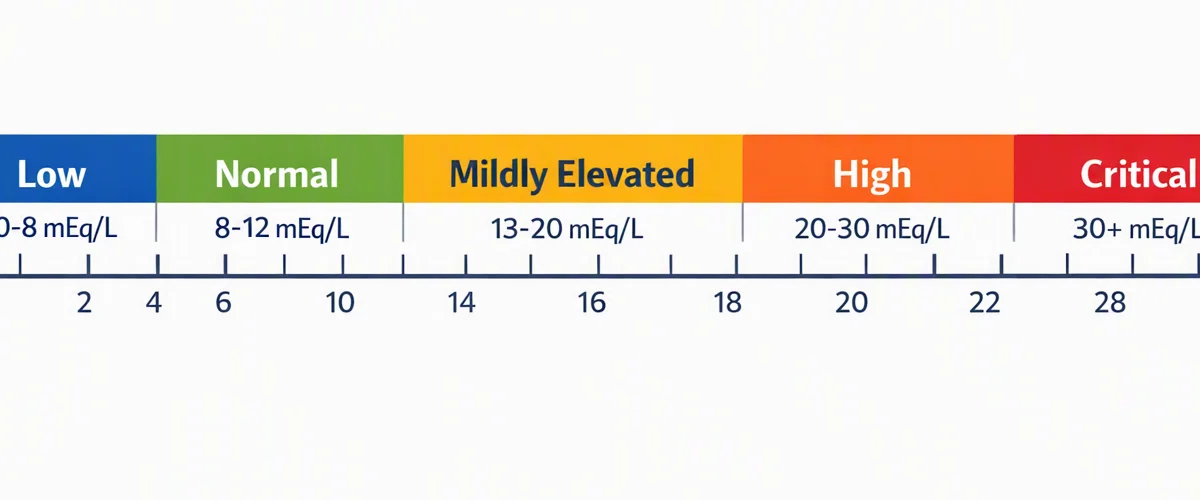
A normal gap can also be due to an electrolyte imbalance from gastrointestinal losses, certain kidney disorders, or treatment effects. The key point is that a normal value does not end the workup if symptoms or blood gas data still suggest acid-base disturbance.
In What Way Albumin Changes the Result
Albumin has a major effect on the anion gap because it contributes negatively charged particles that are not directly measured. When albumin is low, the gap can be falsely low or appear normal even if there is underlying acidosis. This is especially relevant in hospitalized patients and those with hypoalbuminemia, malnutrition, inflammation, or critical illness.
That is why clinicians frequently use the albumin-corrected anion gap. Correcting for albumin can reveal a hidden gap that would otherwise be missed. In other words, the correction helps preserve the diagnostic clue when the raw number is misleading.
The reference range also warrants consideration. Different laboratories may use different ranges or formulas, and the cutoff for abnormality is not universal. A value that looks borderline in one lab may be interpreted differently in another. When albumin is low, the corrected value is often more telling than the unadjusted result alone.
For this reason, the anion gap should never be interpreted in isolation. If the clinical picture suggests acidosis but the result seems normal, checking albumin and considering correction can prevent missed diagnosis.
Common Causes to Review Prior to and Following Testing
Before ordering or reading the test, it helps to reflect on the broader clinical context. The state of renal function is a major consideration because reduced kidney clearance can lead to acid retention and abnormal electrolyte patterns. If renal function is worsening, the anion gap may help distinguish progressive uremic acid buildup from other causes.
Poisoning should always be on the differential when the presentation is severe or unexplained. Exposure history, medication use, and possible access to toxins matter, especially if the patient has altered mental status, high osmolar concern, or sudden acid-base changes. The anion gap can be an first clue sign, but it must be followed by a careful toxicology-oriented diagnostic workup when indicated.
Critical illness can produce numerous overlapping acid-base abnormalities. Sepsis, shock, respiratory failure, tissue hypoxia, and organ dysfunction may all influence the result at once. In that setting, the anion gap is useful because it helps tell apart simple bicarbonate loss from accumulation of unmeasured acids.
After testing, the number should be treated as a diagnostic clue rather than the final answer. A high gap may point to lactate, ketones, toxins, or renal failure; a normal gap may suggest renal tubular acidosis or bicarbonate loss. The next steps depend on the full picture, including the patient’s symptoms, blood gas findings, medication history, and repeat serum electrolytes if needed.
Ultimately, the value of the test lies in how it guides action. It can support urgent therapy, prompt specialized testing, or reassure the clinician that the pattern fits a different acid-base problem. Used well, the anion gap makes the evaluation more efficient and more precise.
FAQ Regarding Requesting an Anion Gap Test
At what point should anion gap testing be ordered for metabolic acidosis?
Anion gap testing should be performed when metabolic acidosis is thought to be present, especially if the cause is not clear from the initial chemistry results. It is most useful when bicarbonate is decreased, the patient has unexplained acidosis, or there is concern for a hidden acid load. The test helps identify the disorder and informs the next step in the diagnostic workup.
What clues suggest a high anion gap disorder?
Signs may involve rapid breathing, nausea, retching, mental confusion, weakness, lack of fluids, or shock symptoms. These findings can appear with lactic acidosis, ketoacidosis, severe infection, kidney failure, or poisoning. As the symptoms can overlap, the anion gap becomes a valuable clinical clue when medical suspicion is strong.
Can low albumin make the anion gap look normal?
Absolutely. Low albumin can lower the calculated gap and make a true abnormality look less significant or even within normal limits. For this reason the albumin-corrected anion gap is essential in patients with hypoalbuminemia or critical illness. Correcting for albumin can uncover a hidden acid-base disorder.
Should the anion gap be calculated from every chemistry panel?
It does not have to be calculated automatically in every situation, but reviewing it is often appropriate whenever serum electrolytes are ordered. A specific approach is especially helpful when there is clinical suspicion for acid-base problems, renal dysfunction, or toxin exposure. Its best use depends on the situation and whether the result will affect interpretation.
How does the anion gap calculator help with acid-base interpretation?
The anion gap calculator speeds up lab interpretation by rapidly determining the gap from serum electrolytes, including sodium, chloride, and bicarbonate, and occasionally correcting for albumin. It aids in detecting anion gap elevation, helps recognize acid-base disorders, and lowers the risk of arithmetic errors. In practice, it is a helpful tool for deciding whether acidosis is likely from organic acids, chloride loss, or another cause impacting acid-base balance.