Which a high anion gap signifies
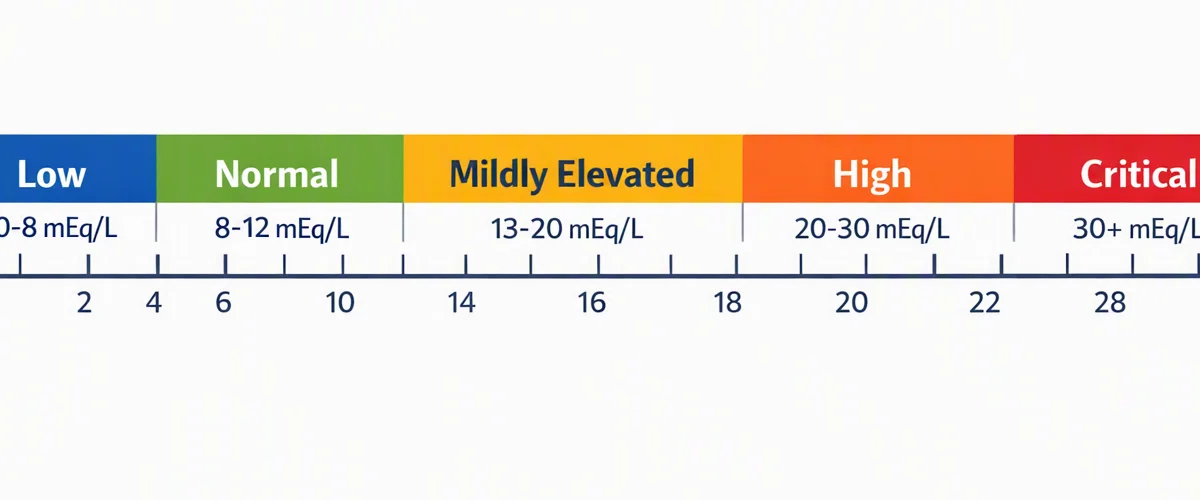
The anion gap is a helpful way to evaluate serum chemistry and identify an acid-base disorder. A high anion gap usually points to anion gap metabolic acidosis, which develops when acid builds up in the body or when normal base is lost. In practical terms, the gap rises because of extra unmeasured anions in the blood.
This pattern matters because it focuses the differential diagnosis. Rather than looking only at pH, clinicians use the gap as a biochemical marker of acid buildup and possible acid accumulation. A high result can reflect metabolic acidosis from benign causes, but it can also be the first sign of poisoning or another serious metabolic derangement.
The concept is closely tied to acid-base balance. When the body produces or accumulates acids faster than it can clear them, bicarbonate is consumed and the gap often rises. This is why a high result is not a diagnosis by itself; it is a clue that guides the next step in the diagnostic workup.
How an Anion Gap Calculator is utilized
An Anion Gap Calculator is a simple way to calculate the gap from standard lab values. It uses serum sodium, serum chloride, and serum bicarbonate to work out the anion gap formula. In its usual form, it assists clinicians identify a lab abnormality that may not be apparent from symptoms alone.
This tool supports laboratory interpretation during immediate assessment. If the gap is elevated, the result can indicate a hidden acid load and trigger a broader search for the cause. That search often includes checking for toxic ingestion, reviewing medications, and assessing for other conditions that lead to acid buildup.
The calculator is especially useful when the clinical presentation is vague. A patient may have nausea, confusion, shortness of breath, or appear generally ill. The calculator can turn a vague concern into a more focused plan by identifying whether the issue matches a high-gap acid-base disorder.
Although the number is significant, it should always be interpreted in combination with the rest of the evaluation. A normal or abnormal result does not stand alone. It must be paired with the history, exam, and related tests such as blood gas analysis and toxin screening when indicated.
Toxins that lead to a high anion gap
Many toxins can lead to a increased anion gap by triggering widespread acid buildup. The classic concerns are ethylene glycol, methanol, salicylates, and propylene glycol. These exposures are important because they may worsen rapidly and because early treatment can prevent major injury.
These substances are often discussed under the category of toxic alcohols, though not all of them are alcohols in the everyday sense. A few are solvents, some are medications, and some are breakdown products that create an acid load after they are metabolized by the body. The common result is anion gap metabolic acidosis from accumulating acids.
Ethylene glycol is typically linked to antifreeze exposure. It is metabolized into acidic compounds that increase the anion gap and can damage the kidneys. Methanol is another major toxic alcohol; it is dangerous because its metabolites can damage the optic system and create significant acidosis. Both are medical emergencies.
Salicylates, including aspirin overdose, can also increase the gap. They often create a mixed picture with more than one acid-base abnormality, which can make interpretation more difficult. Propylene glycol can be seen as a vehicle in some medications and infusions, and in high amounts it may also contribute to acidosis and a higher gap.
Alcohol-associated poisonings
Alcohol-associated poisonings are among the most significant causes to consider when the osmolar gap and anion gap are both abnormal. Methanol and ethylene glycol are the classic examples. Early after exposure, the osmolar gap may be high because the parent compound is still present. Later, as metabolism proceeds, the anion gap may rise as acidic metabolites collect.
This timing is important. A patient may present with a unchanged or only mildly elevated gap early on, then develop a dramatic increase later. That is why clinicians rely on repeated assessment, not a single value. The pattern can help distinguish a toxic alcohol exposure from other forms of metabolic acidosis.
Methanol poisoning often causes visual disturbances, while ethylene glycol more often causes kidney injury and crystals in the urine. In either case, the acid-base pattern reveals the same underlying problem: the body is converting a poison into acids more quickly than it can remove them.
Drug and chemical causes
A toxin-related high gap does not always come from ingesting a toxic alcohol. Salicylates are a major medication cause and can lead to an elevated gap through several mechanisms, including increased acid production and altered metabolism. A person with salicylate toxicity may also show respiratory findings that cloud the clinical picture.
Propylene glycol is another important chemical cause. It may be found in some IV medications or preparations, and large exposures can cause a clinically significant acid-base disturbance. Although less familiar than methanol or ethylene glycol, it belongs in the workup when an unexplained gap is identified in a hospitalized patient.
Isoniazid is also clinically relevant. Overdose can produce severe neurologic toxicity and metabolic complications, sometimes including acidosis. Because the presentation may evolve quickly, it should remain on the list when the history suggests possible medication ingestion.
Additional important sources of elevated anion gap acidosis
Toxins are only just one element of the clinical differential. Several non-injury-related illnesses also cause high anion gap conditions, and they can look similar on first assessment. Most significant include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis develops when tissues are poorly perfused, oxygen delivery is reduced, or metabolism is altered. It is a frequent cause of metabolic acidosis and can be seen in shock, severe infection, seizures, or other conditions that produce widespread physiologic stress. Because lactate is an unmeasured anion, it adds directly to the gap.
Ketoacidosis is an additional common cause. It can arise in diabetes, alcohol use, or prolonged fasting. Ketone bodies act as unmeasured anions, generating the same pattern of anion gap metabolic acidosis. The history often gives away the diagnosis, but the lab pattern supports the concern.
Renal failure leads to the kidneys to accumulate acids and be unable to clear normal metabolic byproducts. Over time, this causes accumulation of unmeasured acids and a progressively increasing gap. In a patient with chronic kidney disease or acute kidney injury, this can mimic toxin-related illness and should be evaluated carefully.
How clinicians separate toxic exposure from different causes
Differentiating toxic ingestion from other possibilities demands a systematic diagnostic workup. Early clues often include the osmolar gap, an arterial blood gas, and the lactate level. Taken together, these help determine whether the problem is a toxic alcohol, lactic acidosis, ketoacidosis, or another source of acid-base disturbance.
The osmolar gap is especially useful early in toxic alcohol exposure. A high osmolar gap suggests extra low-molecular-weight substances in the blood, such as methanol or ethylene glycol. As metabolism proceeds, the osmolar gap may fall while the anion gap rises. This evolving pattern is a classic clue in laboratory interpretation.
An arterial blood gas helps assess the severity of the acidosis and shows whether respiratory compensation is present. A patient may hyperventilate to compensate for metabolic acidosis, lowering carbon dioxide and partially balancing the pH. If compensation is inadequate or the patient is tiring, the risk increases.
Lactate testing helps differentiate lactic acidosis from toxin-related causes. A very high lactate may explain the gap, but a normal or only mildly elevated lactate should lead clinicians to consider more strongly toxic alcohols, salicylates, ketoacidosis, or renal failure. The full pattern matters more than any single result.
Symptoms that may suggest a toxic ingestion
The clinical picture of acidosis related to toxins can be varied and nonspecific, but certain symptoms are concerning. Changes in mental status is a major warning sign, especially if it appears with a high anion gap and no clear alternative explanation. Mental confusion, sluggishness, agitation, or decreased responsiveness may all occur.
Ocular symptoms are particularly concerning in methanol exposure. Patients may describe blurred vision, decreased acuity, or even the feeling that they are “going blind.” This finding should prompt immediate evaluation for toxic alcohol exposure, even before confirmatory testing returns.
Increased respiratory rate is another important clue. It often reflects respiratory compensation for metabolic acidosis, as the body tries to blow off carbon dioxide. A fast breathing rate may be one of the earliest visible signs that an acid-base disorder is becoming severe.
Other findings can include queasiness, emesis, abdominal pain, prostration, or collapse. Because these symptoms Click here! overlap with many illnesses, the lab pattern is essential. When symptoms and labs align, the suspicion for a dangerous ingestion rises sharply.
When a raised anion gap is a critical emergency
An elevated gap is a medical emergency when it suggests poisoning, severe metabolic acidosis, or quickly deteriorating systemic illness. This is especially true when toxic alcohol exposure is possible, because delays in emergency treatment can lead to blindness, kidney injury, neurologic damage, or death.
Prompt assessment is also warranted if the patient has altered mental status, severe tachypnea, a rapidly rising gap, or evidence of end-organ injury. In this setting, clinicians may call poison control, consult toxicology, and begin treatment before all confirmatory studies are back.
Management depends on the cause, but early action can be lifesaving. That may include antidotal therapy, correction of acid-base abnormalities, and sometimes dialysis for severe toxic alcohol exposure or profound acidosis. The key point is that a high gap is not just a lab abnormality; it may be a sign of ongoing systemic toxicity.
Any patient with suspected ingestion, especially of toxic alcohols, should be treated as needing urgent evaluation. The combination of a high anion gap, an abnormal osmolar gap, and concerning symptoms should trigger immediate escalation.
Frequently asked questions on toxins and an elevated anion gap
What toxic substances commonly lead to a high anion gap?
The leading toxin-related causes are methanol, ethylene glycol, salicylates, and propylene glycol. These exposures can create anion gap metabolic acidosis by generating acidic metabolites or altering metabolic pathways. In real-world evaluation, toxic alcohols are among the highest-priority causes to rule out.
How can an Anion Gap Calculator help identify toxic ingestions?
An Anion Gap Calculator rapidly calculates the gap from serum sodium, serum chloride, and serum bicarbonate. If the result is high, it alerts clinicians to possible hidden acid accumulation and supports narrowing the differential diagnosis. That makes it helpful when evaluating a possible toxic ingestion or other acid-base disorder.
How does one describe the difference between a high anion gap and an osmolar gap?
The anion gap indicates unmeasured acids in the blood, while the osmolar gap indicates extra dissolved particles that are not accounted for in routine calculations. Toxic alcohols can raise both, but often at different times during metabolism. A high osmolar gap can indicate recent exposure, while a high anion gap shows acid-forming metabolites have accumulated.
Can aspirin or salicylates cause a high anion gap?
Yes. Salicylates can cause a high anion gap and may also produce a mixed acid-base picture. They are an significant cause of metabolic acidosis and should be considered when the history suggests medication overdose or when the clinical presentation includes ringing in the ears, hyperventilation, or confusion.
At what point should a high anion gap be treated as a medical emergency?
A high anion gap should be treated as an emergency when there is concern for poisoning, severe symptoms, or rapidly worsening acidosis. Signs such as altered mental status, visual disturbances, tachypnea, or a markedly abnormal arterial blood gas warrant urgent evaluation. If toxic alcohol exposure is possible, immediate toxicology-guided treatment may be needed.